Related Experiment Video
Updated: Jul 18, 2026
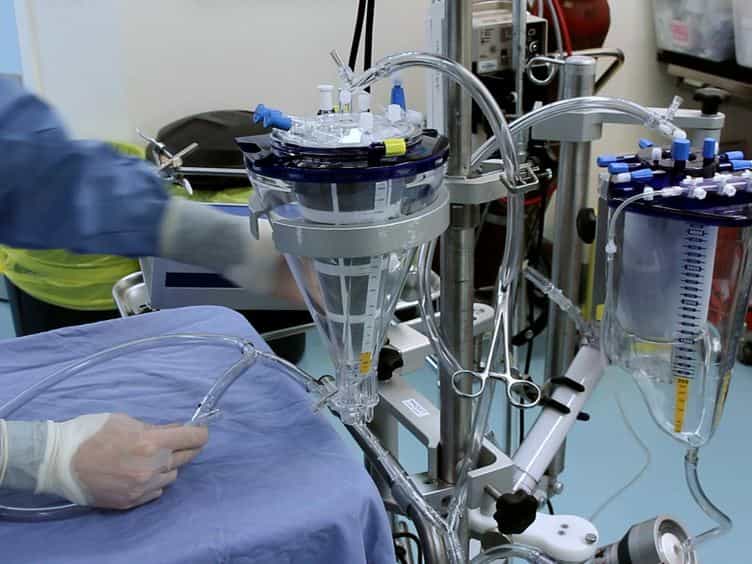

Technique of Subnormothermic Ex Vivo Liver Perfusion for the Storage, Assessment, and Repair of Marginal Liver Grafts
Published on: August 13, 2014
Full-left/Full-right Liver Splitting With Middle Hepatic Vein and Caval Partition During Dual Hypothermic Oxygenated
Umberto Cillo1, Andrea Lauterio2, Alessandro Furlanetto1
1Hepato-Biliary-Pancreatic Surgery and Liver Transplantation Unit, Padua University Hospital, Padua, Italy.

Background:
Split liver transplantation is a valuable means of mitigating organ scarcity but requires significant surgical and logistical effort. Ex vivo splitting is associated with prolonged cold ischemia, with potentially negative effects on organ viability. Machine perfusion can mitigate the effects of ischemia-reperfusion injury by restoring cellular energy and improving outcomes.
Methods:
We describe a novel technique of full-left/full-right liver splitting, with splitting and reconstruction of the vena cava and middle hepatic vein, with dual arterial and portal hypothermic oxygenated machine perfusion. The accompanying video depicts the main surgical passages, notably the splitting of the vena cava and middle hepatic vein, the parenchymal transection, and the venous reconstruction.
Results:
The left graft was allocated to a pediatric patient having methylmalonic aciduria, whereas the right graft was allocated to an adult patient affected by hepatocellular carcinoma and cirrhosis.
Conclusions:
This technique allows ex situ splitting, counterbalancing prolonged ischemia with the positive effects of hypothermic oxygenated machine perfusion on graft viability. The venous outflow is preserved, safeguarding both grafts from venous congestion; all reconstructions can be performed ex situ, minimizing warm ischemia. Moreover, there is no need for highly skilled surgeons to reach the donor hospital, thereby simplifying logistical aspects.


