Related Experiment Video
Updated: Jun 25, 2025

Using Visual and Narrative Methods to Achieve Fair Process in Clinical Care
Published on: February 16, 2011
Monetary value of health-a practical decision-making framework combining equity considerations and WTP
Elizabeta Ribarić1, Ismar Velić1, Ana Bobinac2
1University of Rijeka, Faculty of Economics and Business, Center for Health Economics and Pharmacoeconomics (CHEP), Ivana Filipovića 4, 51000, Rijeka, Croatia.

Objective:
We estimate the first monetary value of a health gain in Croatia to inform the debate about the appropriate "demand-side" cost-effectiveness thresholds in Croatia but also Central and Eastern Europe, where such debates are still uncommon. We test the empirical support for two equity considerations: age and severity operationalized as proportional shortfall (PS), and propose a pragmatic framework for combining equity considerations with the monetary value of health into a single threshold.
Methods:
We used the contingent valuation method to elicit the willingness to pay per Quality-Adjusted Life Year (QALY) in Croatia, using a representative sample of the population (N = 1,500, online survey). 29 EQ-5D health states were valued using payment scales and open-ended question as payment vehicles. To test the hypotheses, we used both parametric tests and non-parametric tests. Multilinear regression was employed to test the theoretical validity of the results.
Results:
The monetary value of a health gain in Croatia is equivalent to 1.15 of GDP per capita (equaling €17,000). Age of patients seems to be an important equity-related characteristic. The WTP per QALY in the age-neutral risk group (€11,900) was nearly equivalent to the WTP per QALY in the adult (neutral) risk group (€11,700) but lower by 16% compared to the WTP per QALY estimated in children (€14,200; p = 0.00). WTP estimates are theoretically valid and to, a small degree, scale sensitive. There is a positive association between the level of proportional shortfall and willingness to pay. To increase the usefulness of our results for the policy-makers, we combine the elicited preferences into a single decision-making framework and construct several cost-effectiveness thresholds based on willingness to pay and equity-related preferences. Based on empirical results, cost-effectiveness thresholds could range up to €20,308 for the most severe health conditions in children or could be lowered to €16,777 for less severe health conditions.
Discussion:
In Central and Eastern Europe, in spite of a growing understanding of the importance of further developing value-based assessment frameworks there has been very little empirical research to guide, inform and promote this development. Countries in this region use mainly GDP-based thresholds without empirical evidence to support such important decisions. This may lead to thresholds that are too high, with detrimental consequence for the pricing and reimbursement systems.
More Related Videos

Related Concept Videos
 01:29
Concepts of Health and Illness
 01:25
Models of Health Promotion and Illness Prevention I
The health belief model (HBM) attempts to predict health-related behavior in specific belief patterns. According to the HBM, a person's...
 01:09
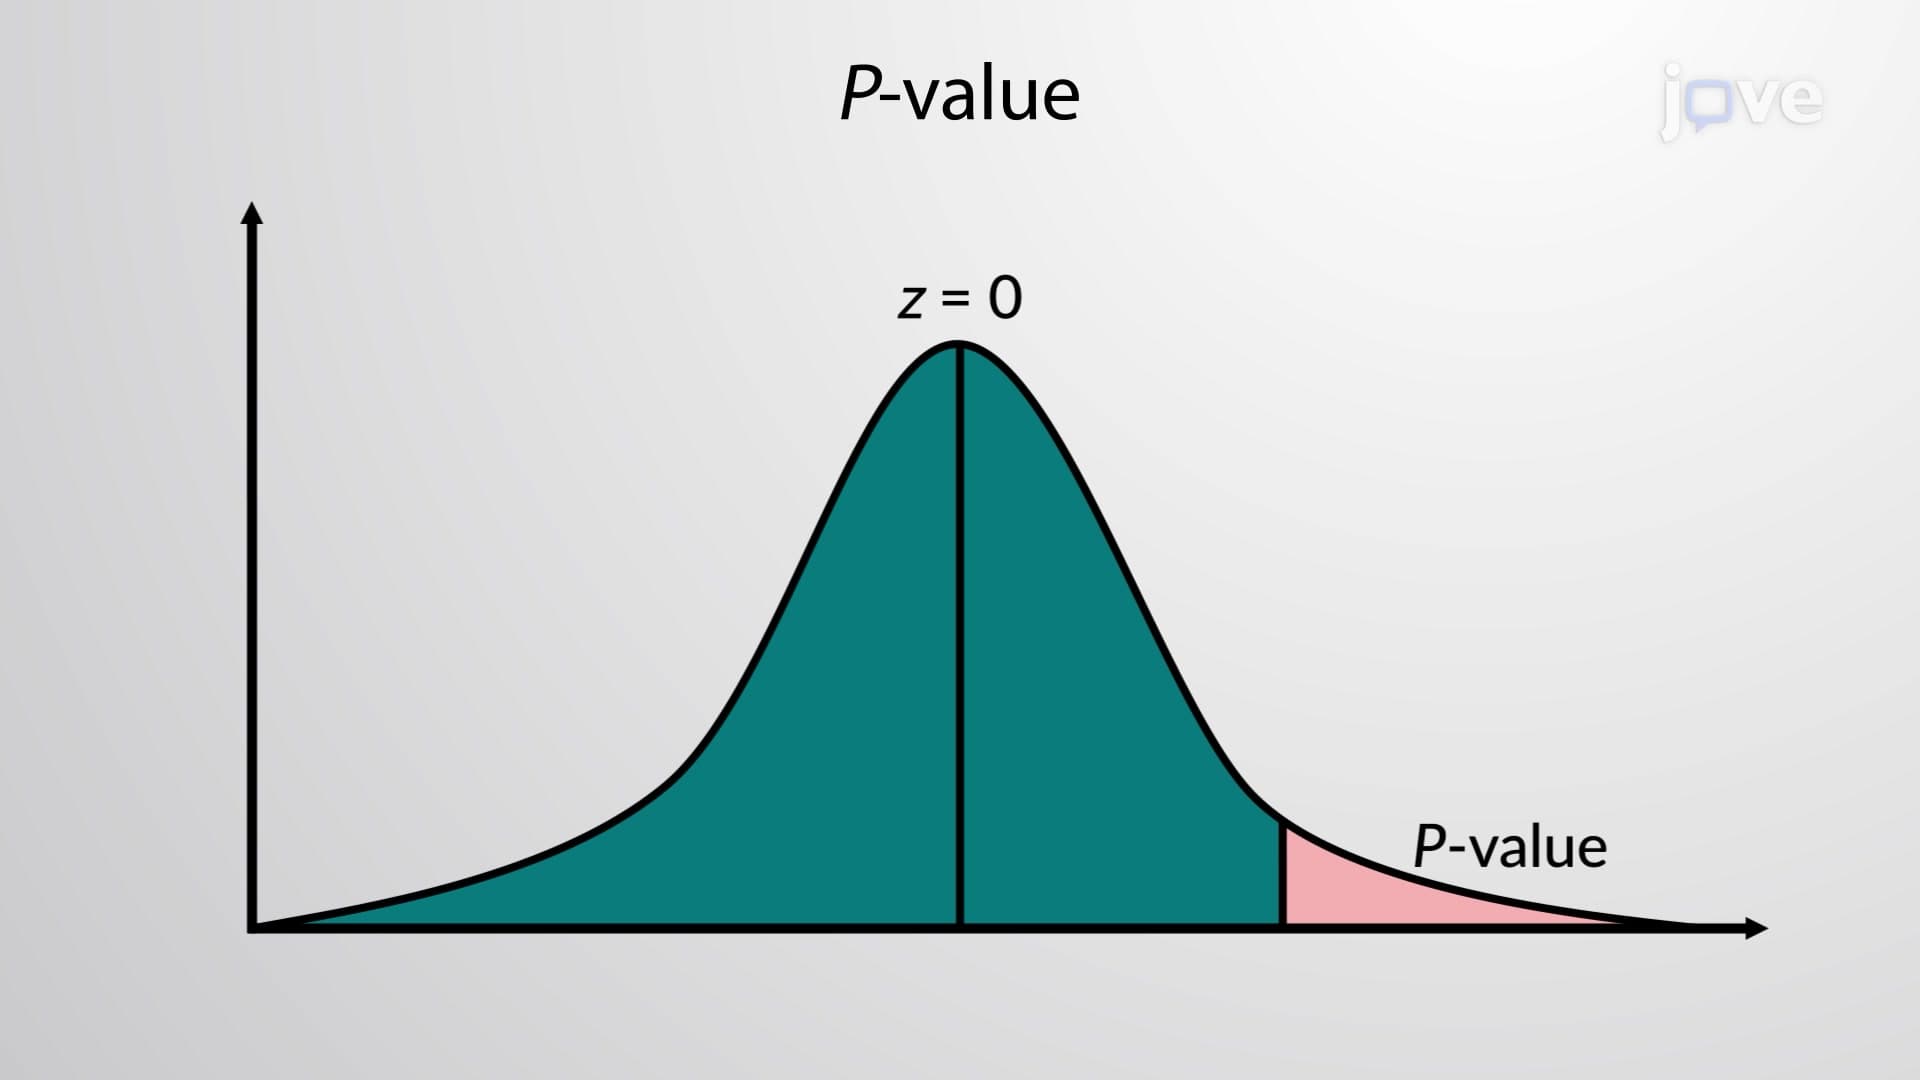
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can...
 01:21
Dimensions of Health and Illness
 01:17
Ethical Dilemmas I
Let us explore some examples to understand the potentially complex moral decisions nurses face.
Take the case of caring for minors, particularly in areas related to reproductive...
 01:27
Ethical Issues
Ethical Concerns in Healthcare: