Related Experiment Video
Updated: Jun 25, 2025
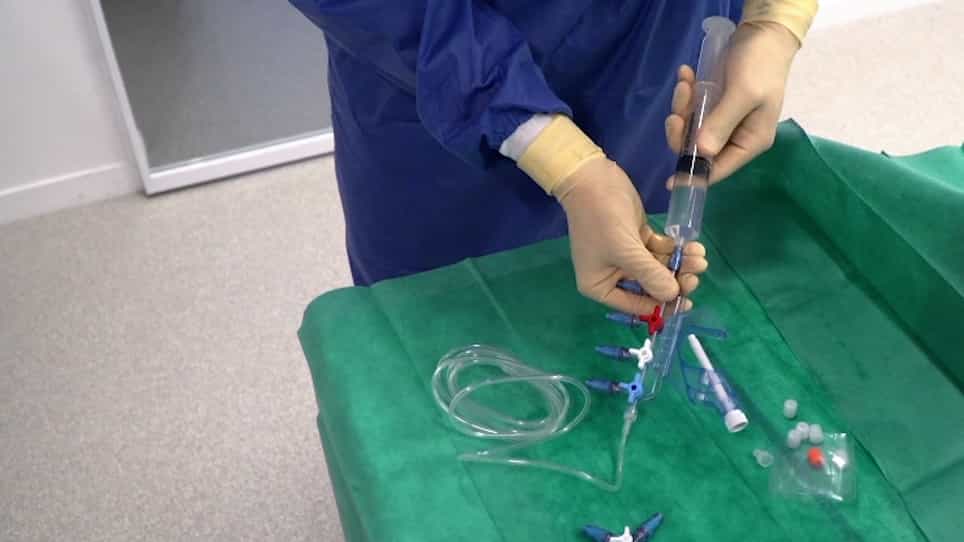

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Dressings and securement devices to prevent complications for peripheral arterial catheters
Jessica A Schults1,2,3, Heather Reynolds3,4,5, Claire M Rickard1,2,3,6
1Herston Infectious Diseases Institute, Nursing Midwifery Research Centre, Metro North Health, Brisbane, Australia.

Background:
Peripheral arterial catheters (ACs) are used in anaesthesia and intensive care settings for blood sampling and monitoring. Despite their importance, ACs often fail, requiring reinsertion. Dressings and securement devices maintain AC function and prevent complications such as infection.
Objectives:
To evaluate the effectiveness of peripheral AC dressing and securement devices to prevent failure and complications in hospitalised people.
Search Methods:
We searched the Cochrane Wounds Specialised Register, CENTRAL, MEDLINE, Embase, and CINAHL Plus up to 16 May 2023. We also searched ClinicalTrials.gov and the World Health Organization International Clinical Trials Registry Platform up to 16 May 2023.
Selection Criteria:
We included randomised controlled trials (RCTs) comparing different dressing and securement devices for the stabilisation of ACs in hospitalised people.
Data Collection And Analysis:
Two review authors independently selected trials for inclusion, extracted data, and assessed risk of bias using Cochrane's RoB 1 tool. We resolved disagreements by discussion, or by consulting a third review author when necessary. We assessed the certainty of evidence using GRADE.
Main Results:
We included five RCTs with 1228 participants and 1228 ACs. All included studies had high risk of bias in one or more domains. We present the following four comparisons, with the remaining comparisons reported in the main review. Standard polyurethane (SPU) plus tissue adhesive (TA) compared with SPU: we are very uncertain whether use of SPU plus TA impacts rates of AC failure (risk ratio (RR) 0.44, 95% confidence interval (CI) 0.20 to 0.98; I² = 0%; 2 studies, 165 participants; very low-certainty evidence). Neither study (165 participants) reported catheter-related bloodstream infections (CRBSI), thus we are very uncertain whether SPU plus TA impacts on the incidence of CRBSI (very low-certainty evidence). It is very uncertain whether use of SPU plus TA impacts AC dislodgement risk (RR 0.54, 95% CI 0.03 to 9.62; I² = 44%; 2 studies, 165 participants; very low-certainty evidence). We are very uncertain whether use of SPU plus TA impacts AC occlusion rates (RR 1.20, 95% CI 0.37 to 3.91; I² = 3%; 2 studies, 165 participants; very low-certainty evidence). We are very uncertain whether use of SPU plus TA impacts rates of adverse events with few reported events across groups (RR 0.89, 95% CI 0.09 to 8.33; I² = 0%; 2 studies, 165 participants; very low-certainty evidence). Bordered polyurethane (BPU) compared to SPU: we are very uncertain whether use of BPU impacts rates of AC failure (RR 0.67, 95% CI 0.21 to 2.13; 1 study, 60 participants; very low-certainty evidence). BPU may make little or no difference to CRBSI compared to SPU (RR 3.05, 95% CI 0.12 to 74.45; I² = not applicable as 1 study (60 participants) reported 0 events; 2 studies, 572 participants; low-certainty evidence). BPU may make little or no difference to the risk of AC dislodgement compared with SPU (RR 0.75, 95% CI 0.17 to 3.22; I² = 0%; 2 studies, 572 participants; low-certainty evidence). BPU may make little or no difference to occlusion risk compared with SPU (RR 0.80, 95% CI 0.60 to 1.07; I² = 0%; 2 studies, 572 participants; low-certainty evidence). It is very uncertain whether BPU impacts on the risk of adverse events compared with SPU (RR 0.33, 95% CI 0.01 to 7.87; 1 study, 60 participants; very low-certainty evidence). SPU plus sutureless securement devices (SSD) compared to SPU: we are very uncertain whether SPU plus SSD impacts risk of AC failure compared with SPU (RR 0.78, 95% CI 0.40 to 1.52; I² = 0%; 2 studies, 157 participants; very low-certainty evidence). We are very uncertain if SPU plus SSD impacts CRBSI incidence rate with no events in both groups (2 studies, 157 participants; very low-certainty evidence). It is very uncertain whether SPU plus SSD impacts risk of dislodgement (RR 0.14, 95% CI 0.01 to 2.57; I² = not applicable as 1 study (96 participants) reported 0 events; 2 studies, 157 participants; very low-certainty evidence). It is very uncertain whether SPU plus SSD impacts risk of AC occlusion (RR 1.94, 95% CI 0.50 to 7.48; I² = 38%; 2 studies, 157 participants; very low-certainty evidence). We are very uncertain whether SPU plus SSD impacts on the risk of adverse events (RR 1.94, 95% CI 0.19 to 20.24; I² = not applicable as 1 study (96 participants) reported 0 events; 2 studies, 157 participants; very low-certainty evidence). Integrated securement dressings compared to SPU: integrated securement dressings may result in little or no difference in risk of AC failure compared with SPU (RR 1.96, 95% CI 0.80 to 4.84; 1 study, 105 participants; low-certainty evidence); may result in little or no difference in CRBSI incidence with no events reported (1 study, 105 participants; low-certainty evidence); may result in little or no difference in the risk of dislodgement (RR 0.33, 95% CI 0.04 to 3.04; 1 study, 105 participants; low-certainty evidence), may result in little or no difference in occlusion rates with no events reported (1 study, 105 participants; low-certainty evidence), and may result in little or no difference in the risk of adverse events (RR 0.35, 95% CI 0.01 to 8.45; 1 study, 105 participants; low-certainty evidence).
Authors' Conclusions:
There is currently limited rigorous RCT evidence available about the relative clinical effectiveness of AC dressing and securement products. Limitations of current evidence include small sample size, infrequent events, and heterogeneous outcome measurements. We found no clear difference in the incidence of AC failure, CRBSI, or adverse events across AC dressing or securement products including SPU, BPU, SSD, TA, and integrated securement products. The limitations of current evidence means further rigorous RCTs are needed to reduce uncertainty around the use of dressing and securement devices for ACs.


Related Concept Videos
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...