Related Experiment Video
Updated: Jun 25, 2025


Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Kidney Measurement and Glomerular Filtration Rate Evolution in Children with Polycystic Kidney Disease
Ramona Stroescu1,2, Mihai Gafencu2,3, Ruxandra Maria Steflea2,3
1Department XI of Pediatrics-1st Pediatric Discipline, Center for Research on Growth and Developmental Disorders in Children, "Victor Babes" University of Medicine and Pharmacy Timisoara, Eftimie Murgu Sq. No. 2, 300041 Timisoara, Romania.

Insights
Autosomal dominant polycystic kidney disease (ADPKD) in children often presents with normal kidney function, despite enlarged kidneys. The quadratic estimation of glomerular filtration rate (qGFR) provides a more accurate assessment than the Schwartz formula, avoiding false hyperfiltration classification.
Area of Science:
- Nephrology
- Pediatric Nephrology
- Medical Genetics
Background:
- Autosomal dominant polycystic kidney disease (ADPKD) is an inherited disorder causing renal tubular cystic dilatations and kidney enlargement.
- Cystic expansion in ADPKD reduces functional nephrons, leading to progressive decline in renal function and complications like glomerular hyperfiltration, albuminuria, proteinuria, and hematuria.
- ADPKD presentation in children varies significantly, from asymptomatic cases to rapid progression, with early-onset disease (<2 years) showing faster renal function decline.
Purpose of the Study:
- To explore glomerular filtration rate (GFR) dynamics and renal ultrasound-adjusted percentiles in children with ADPKD.
- To compare the accuracy of the modified Schwartz formula with the quadratic equation for estimating GFR in pediatric ADPKD patients.
- To evaluate the prevalence of glomerular hyperfiltration in children with ADPKD using different GFR estimation methods.
Main Methods:
- Retrospective analysis of 16 pediatric patients with ADPKD.
- Measurement of glomerular filtration rates (GFR) using both the modified Schwartz formula and a quadratic equation (qGFR) after adjusting serum creatinine.
- Assessment of kidney size using renal ultrasound-adjusted percentiles and correlation with GFR dynamics over a 1-year follow-up.
Main Results:
- 14 out of 16 patients exhibited kidney percentiles over 90%.
- The quadratic equation (qGFR) estimated lower GFR values (111.95 ± 12.43 mL/min/1.73 m²) compared to the Schwartz eGFR (126.28 ± 33.07 mL/min/1.73 m²), p = 0.14.
- Using qGFR, no patients reached the glomerular hyperfiltration threshold, and GFR showed linear or slightly decreasing trends (ΔeGFR = -0.32 ± 5.78 mL/min/1.73 m²), unlike the Schwartz formula which could falsely indicate hyperfiltration (ΔeGFR = 7.51 ± 19.46 mL/min/1.73 m²), p = 0.019.
Conclusions:
- Children with ADPKD often have enlarged kidneys but may maintain normal or near-normal renal function.
- The quadratic equation provides a more reliable estimation of GFR in pediatric ADPKD, accurately reflecting renal function dynamics and avoiding misclassification of hyperfiltration.
- Accurate GFR assessment is crucial for managing pediatric ADPKD, guiding treatment strategies, and predicting disease progression.
Abstract:
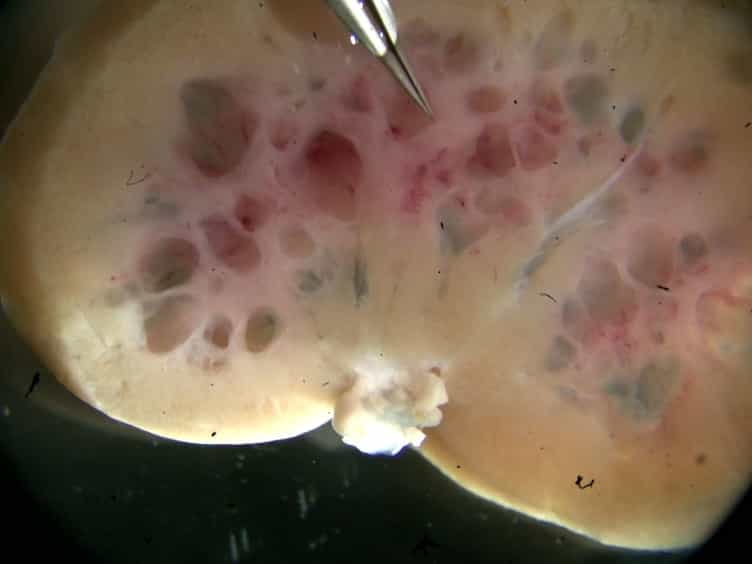
Autosomal dominant polycystic kidney disease (ADPKD) is an inherited disorder characterized by renal tubular cystic dilatations. The cysts can develop anywhere along the nephron, and over time the cystic dilatation leads to kidney enlargement. On the other hand, the cysts begin to reduce the number of functional nephrons as a consequence of cystic expansion that further contributes to the decline in renal function over the years. The pressure exerted by the dilated cysts leads to compensatory mechanisms that further contribute to the decline in renal function. These structural changes are responsible of glomerular hyperfiltration states, albuminuria, proteinuria, and hematuria. However, the presentation of ADPKD varies in children, from a completely asymptomatic child with incidental ultrasound detection of cysts to a rapidly progressive disease. There have been reports of early onset ADPKD in children younger than 2 years that showed a more rapid decline in renal function. ADPKD is caused by a mutation in PKD1 and PKD2 genes. Today, the PKD1 gene mutation seems to account for up to 85% of the cases worldwide, and it is associated with worse renal outcomes. Individuals with PKD2 gene mutation seem to present a milder form of the disease, with a more delayed onset of end-stage kidney disease. The cardinal sign of ADPKD is the presence of renal cysts during renal ultrasound. The current guidelines provide clinicians the recommendations for genetic testing in children with a positive family history. Given that the vast majority of children with ADPKD present with normal or supra-normal kidney function, we explored the glomerular filtration rates dynamics and the renal ultrasound-adjusted percentiles. In total, 14 out of 16 patients had kidney percentiles over 90%. The gene mutations were equally distributed among our cohort. In addition, we compared the modified Schwartz formula to the quadratic equation after adjusting the serum creatinine measurements. It seems that even though children with ADPKD have enlarged kidneys, the renal function is more likely normal or near normal when the quadratic estimation of glomerular filtration rate is used (qGFR tended to be lower, 111.95 ± 12.43 mL/min/1.73 m2 when compared to Schwartz eGFR 126.28 ± 33.07 mL/min/1.73 m2, p = 0.14). Also, when the quadratic equation was employed, not even a single patient reached the glomerular hyperfiltration threshold. The quadratic formula showed that glomerular filtration rates are linear or slightly decreasing after 1 year of follow-up (quadratic ΔeGFR = -0.32 ± 5.78 mL/min/1.73 m2), as opposed to the Schwartz formula that can falsely classify children in a hyperfiltration state (ΔeGFR = 7.51 ± 19.46 mL/min/1.73 m2), p = 0.019.

Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:28
Glomerular Filtration Rate and its Regulation
GFR regulation involves two primary intrinsic controls: the myogenic and tubuloglomerular feedback mechanisms.
The myogenic...
 01:02
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:10
Nephrons