Related Experiment Video
Updated: Jun 25, 2025
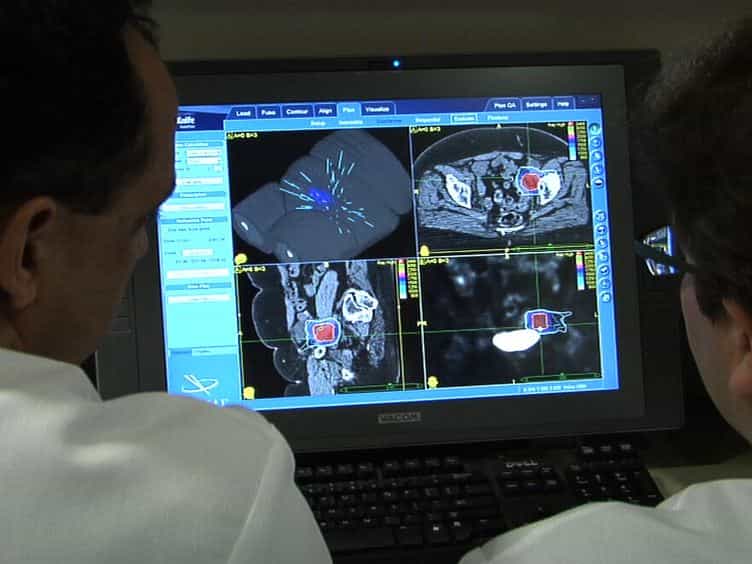

Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Pelvic lymph node motion during cone-beam computed tomography guided stereotactic radiotherapy
J Janssen1, F H E Staal1, J A Langendijk1
1Department of Radiation Oncology, University of Groningen, University Medical Center Groningen, Groningen, the Netherlands.

Background And Purpose:
Stereotactic body radiotherapy (SBRT) is increasingly applied for pelvic lymph node recurrence. Thus far, knowledge on pelvic lymph node motion during CBCT-guided SBRT is lacking and the applied margins vary between institutions. This study evaluated pelvic lymph node motion during CBCT-guided SBRT and assessed the currently applied PTV margins of 3 and 5 mm.
Material And Methods:
In total, 45 pelvic lymph node metastases were included. One observer delineated 45 GTVs on planning CT, 224 GTVs on pre-fraction and 216 on post-fraction CBCT. The GTV centroid coordinates were derived from all images for inter- and intrafraction motion analysis. Additionally, we assessed the influence of treatment time and lesion location on lesion motion. The expected coverage of a 3-mm and 5-mm PTV margin was assessed using the inclusiveness index for GTVs on pre- and post-fraction CBCT.
Results:
Lymph node interfraction motion was limited to 5 mm in 96-97 % of fractions for all translational directions and intrafraction lesion motion was limited to 3 mm in 97-100 % of fractions. Para-rectal lesions (11 %) were associated with significantly larger inter- and intrafraction motion compared to other pelvic locations and treatment duration showed no correlation with lesion motion. The mean (sd) lesion inclusiveness index was 99 % (5 %) for the 5-mm PTV margin and 96 % (9 %) for the 3-mm margin.
Conclusion:
Pelvic lymph node motion during CBCT-guided stereotactic radiotherapy was within the widely applied PTV margin of 5 mm, providing an opportunity to reduce this margin for pelvic lymph node SBRT.

