Related Experiment Video
Updated: May 7, 2026

Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Hybrid stage 1 palliation with simultaneous off-pump ventricular assist device placement in neonates with high-risk
Constantine D Mavroudis1, Matthew J O'Connor1, Carol Wittlieb-Weber1
1Divisions of Cardiothoracic Surgery and Cardiology, Children's Hospital of Philadelphia, Philadelphia, Pa.

Background:
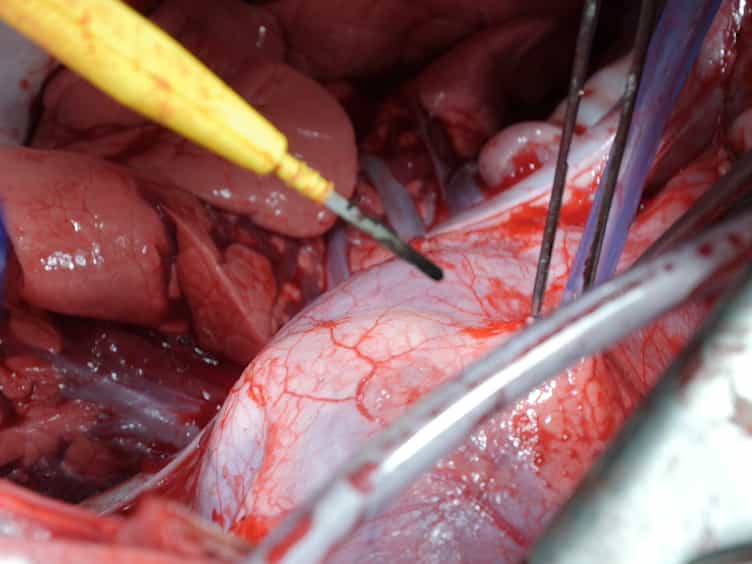
Infants with single ventricle heart disease and severe atrioventricular valve regurgitation have poor outcomes following conventional staged palliation. As such, ventricular assist device (VAD) placement along with hybrid stage 1 palliation has been proposed as a bridge to heart transplant. We present a novel surgical technique for VAD implantation concurrent with hybrid stage 1 that avoids cardiopulmonary bypass.
Methods:
We performed a retrospective review of our institutional experience with this novel surgical technique.
Results:
Three patients (weight, 2.7-3.5 kg; age, 3 to 5 days) underwent hybrid stage 1 with VAD placement, consisting of bilateral 3.5-mm expandable polytetrafluoroethylene (PTFE) pulmonary artery bands, a ductal stent, a 6-mm Berlin Heart outflow cannula onto the main pulmonary trunk with a 10-mm graft, a 6-mm Berlin Heart outflow cannula onto the right atrium, and a 10-mL Berlin Heart pump. In patients with severe aortic arch hypoplasia or coarctation, a 4-mm PTFE graft was sewn from the VAD outflow graft to the innominate artery to protect coronary and cerebral perfusion. Procedures were performed off bypass with minimal blood product use. Patients were extubated on postoperative days 2, 2, and 5. There were no procedural complications. All patients were transferred out of the intensive care unit and demonstrated appropriate weight gain. Anticoagulation strategy was bivalirudin and antiplatelet therapy. The patients underwent transplantation after 149 days, 157 days, and 288 days of support.
Conclusions:
Off-pump single ventricle VAD placement is technically feasible and can be done at the time of hybrid stage 1 palliation with minimal operative morbidity as a bridge to transplant.