Related Experiment Video
Updated: Jun 24, 2025

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Impact of a 6-12-h delay between ileocolic intussusception diagnostic US and fluoroscopic reduction on patients'
Julian Lopez-Rippe1, J Christopher Davis1,2, Rebecca A Dennis1,2
1Department of Radiology, Children's Hospital of Philadelphia, 3401 Civic Center Blvd, Philadelphia, PA, 19104, USA.

Background:
Image-guided reduction of intussusception is considered a radiologic urgency requiring 24-h radiologist and technologist availability.
Objective:
To assess whether a delay of 6-12 h between US diagnosis and fluoroscopic reduction of ileocolic intussusception affects the success frequency of fluoroscopic reduction.
Materials And Methods:
Retrospective review of 0-5-year-olds undergoing fluoroscopic reduction for ileocolic intussusception from 2013 to 2023. Exclusions were small bowel intussusception, self-reduced intussusception, first fluoroscopic reduction attempt>12 h after US, prior bowel surgery, inpatient status, and patient transferred for recurrent intussusception. Data collected included demographics, symptoms, air/contrast enema selection, radiation dose, reduction failure, 48-h recurrence, surgery, length of stay, and complications. Comparisons between<6-h and 6-12-h delays after ultrasound diagnosis were made using chi-square, Fisher's exact test, and Mann-Whitney U tests (P< 0.05 considered significant).
Results:
Of 438 included patients, 387 (88.4%) were reduced in <6 h (median age 1.4 years) and 51 (11.7%) were reduced between 6 and 12 h (median age 2.05 years), with median reduction times of 1:42 and 7:07 h, respectively. There were no significant differences between the groups for reduction success (<6 h 87.3% vs. 6-12 h 94.1%; P-value = 0.16), need for surgery (<6 h 11.1% vs. 6-12 h 3.9%; P-value=0.112), recurrence of intussusception within 48 h after reduction (<6 h 9.3% vs. 6-12 h 15.7%; P-value=0.154), or length of hospitalization (<6 h 21:07 h vs. 6-12 h 20:03 h; P-value=0.662).
Conclusion:
A delay of 6-12 h between diagnosis and fluoroscopic reduction of ileocolic intussusception is not associated with reduced fluoroscopic reduction success, need for surgical intervention after attempted reduction, recurrence of intussusception following successful reduction, or hospitalization duration after reduction.

Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:23
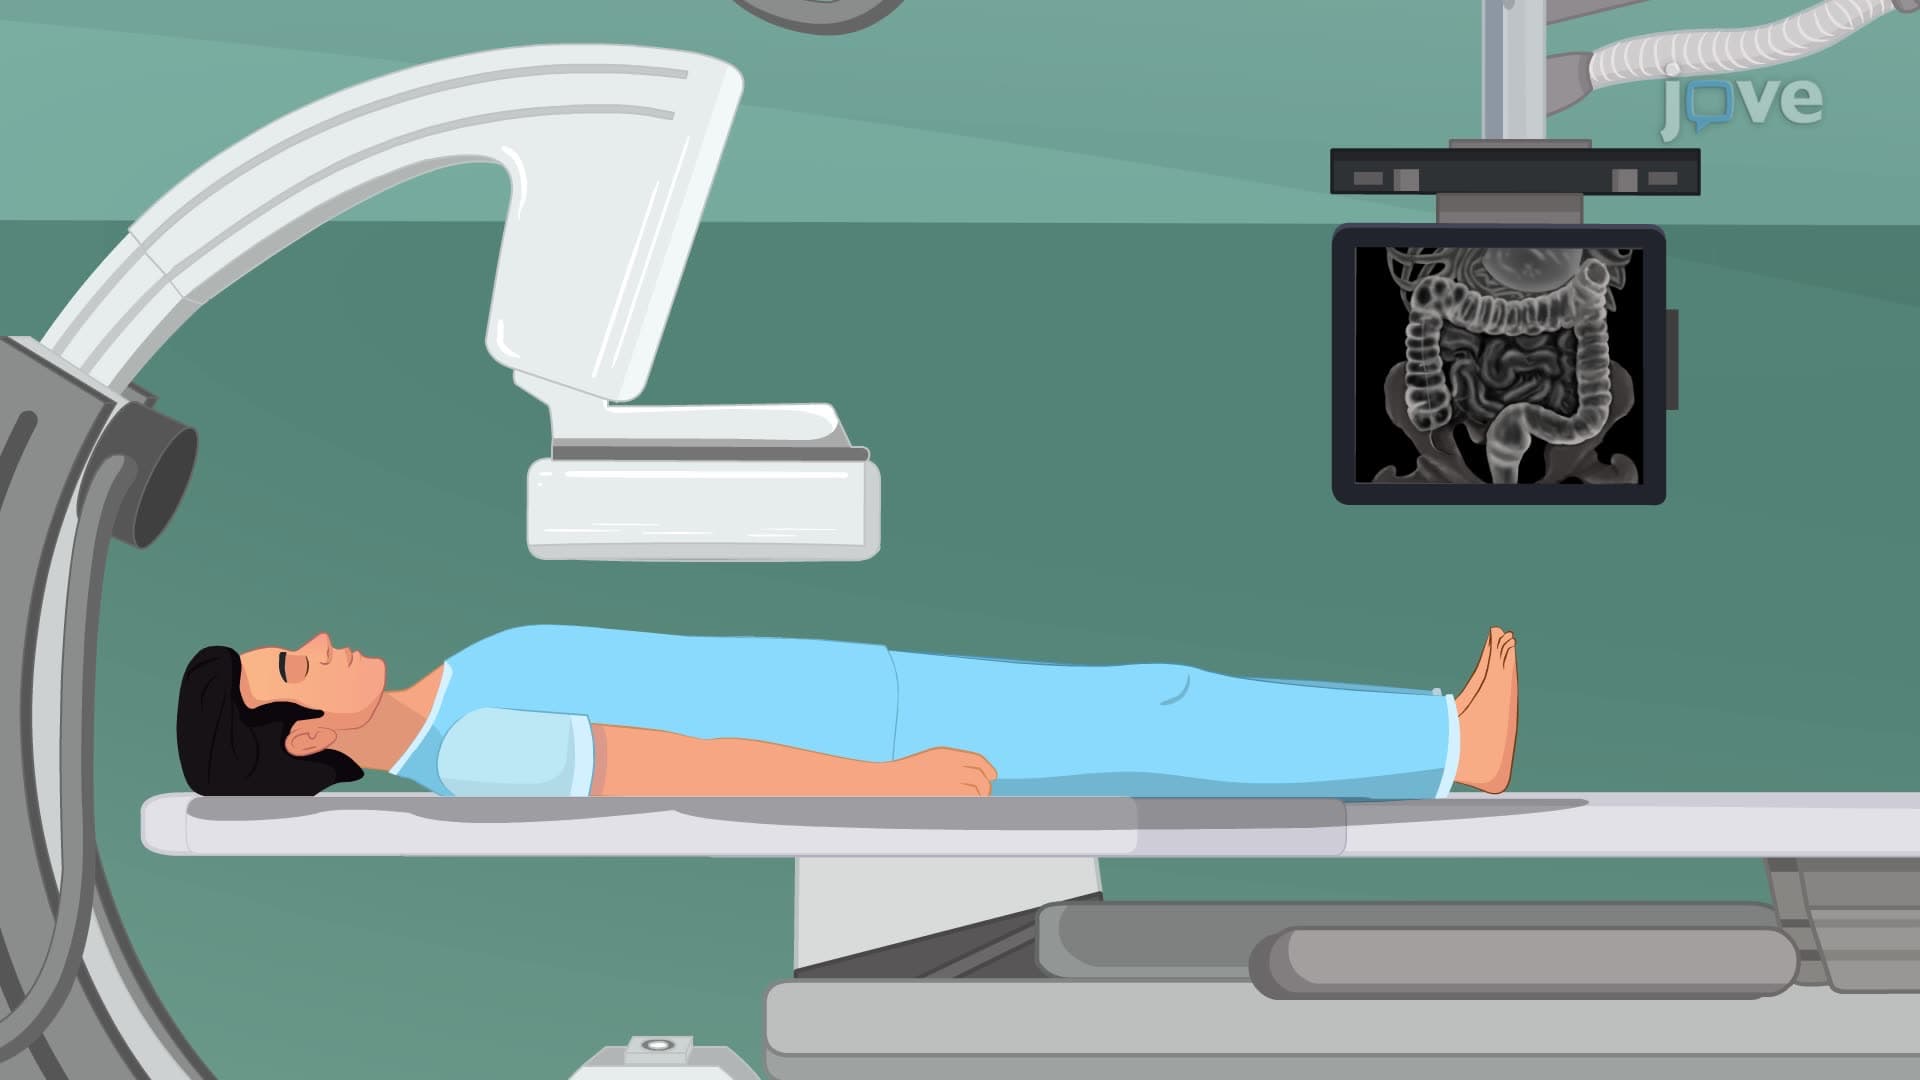
Lower GI Series: Barium Enema
Procedure Details
The examination begins by inserting a lubricated rectal tube into the patient's rectum to administer a radiopaque barium solution. The barium flow is carefully...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Endoscopic Procedures II: Colonoscopy
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...