Related Experiment Video
Updated: Jun 24, 2025
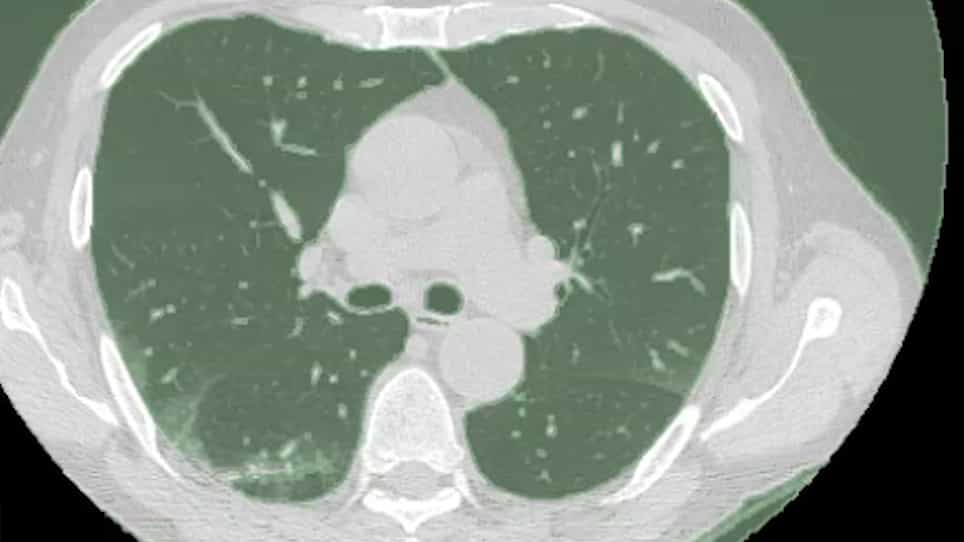

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Association of clinical and imaging characteristics with pulmonary function testing in patients with Long-COVID
Lin-Mei Zhao1,2, Andrew C Lancaster1,3, Ritesh Patel1
1Department of Radiology and Radiological Science, Johns Hopkins University School of Medicine, Baltimore, MD, USA.

Purpose:
The purpose of this study is to identify clinical and imaging characteristics associated with post-COVID pulmonary function decline.
Methods:
This study included 22 patients recovering from COVID-19 who underwent serial spirometry pulmonary function testing (PFT) before and after diagnosis. Patients were divided into two cohorts by difference between baseline and post-COVID follow-up PFT: Decline group (>10 % decrease in FEV1), and Stable group (≤10 % decrease or improvement in FEV1). Demographic, clinical, and laboratory data were collected, as well as PFT and chest computed tomography (CT) at the time of COVID diagnosis and follow-up. CTs were semi-quantitatively scored on a five-point severity scale for disease extent in each lobe by two radiologists. Mann-Whitney U-tests, T-tests, and Chi-Squared tests were used for comparison. P-values <0.05 were considered statistically significant.
Results:
The Decline group had a higher proportion of neutrophils (79.47 ± 4.83 % vs. 65.45 ± 10.22 %; p = 0.003), a higher absolute neutrophil count (5.73 ± 2.68 × 10⁹/L vs. 3.43 ± 1.74 × 10⁹/L; p = 0.031), and a lower proportion of lymphocytes (9.90 ± 4.20 % vs. 21.21 ± 10.97 %; p = 0.018) compared to the Stable group. The Decline group also had significantly higher involvement of ground-glass opacities (GGO) on follow-up chest CT [8.50 (4.50, 14.50) vs. 3.0 (1.50, 9.50); p = 0.032] and significantly higher extent of reticulations on chest CT at time of COVID diagnosis [6.50 (4.00, 9.00) vs. 2.00 (0.00, 6.00); p = 0.039] and follow-up [5.00 (3.00, 13.00) vs. 2.00 (0.00, 5.00); p = 0.041]. ICU admission was higher in the Decline group than in the Stable group (71.4 % vs. 13.3 %; p = 0.014).
Conclusions:
This study provides novel insight into factors influencing post-COVID lung function, irrespective of pre-existing pulmonary conditions. Our findings underscore the significance of neutrophil counts, reduced lymphocyte counts, pulmonary reticulation on chest CT at diagnosis, and extent of GGOs on follow-up chest CT as potential indicators of decreased post-COVID lung function. This knowledge may guide prediction and further understanding of long-term sequelae of COVID-19 infection.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction