Related Experiment Video
Updated: Oct 12, 2026

Non-Invasive Model of Neuropathogenic Escherichia coli Infection in the Neonatal Rat
Published on: October 29, 2014
Endemic Serratia marcescens infection in a neonatal intensive care nursery associated with gastrointestinal

Abstract:
Serratia marcescens (SM) produced a prolonged outbreak in a neonatal intensive care unit of high level gastrointestinal colonization (10(9) SM/g feces) which in the early part of the outbreak predisposed to respiratory infection. The early outbreak featured a strain of SM carrying a 54 X 10(6) dalton conjugative plasmid which mediated resistance to gentamicin, tobramycin and beta-lactam agents. The second part of the outbreak involved primarily gastrointestinal colonization with SM strains that were plasmid-free. Acquisition of SM was related to very low birth weight (less than 1500 g). Among very low birth weight neonates, SM colonization was associated with pneumonia, patent ductus arteriosus, congestive heart failure and septicemia. Among neonates greater than 1500 g, SM colonization was associated with bronchopulmonary dysplasia, use of a respirator, patent ductus arteriosus and congestive heart failure. Respirator contamination, respiratory tract colonization and consequent pneumonia were reduced by more frequent changing of respirator tubing. Colonized sinks remained chronically colonized with multiresistant SM.
Insights
Serratia marcescens (SM) caused a prolonged NICU outbreak, leading to gastrointestinal colonization and respiratory infections, particularly in very low birth weight infants. Frequent respirator tubing changes reduced SM-associated pneumonia.
Area of Science:
- Medical Microbiology
- Infectious Diseases
- Neonatal Care
Background:
- Serratia marcescens (SM) outbreaks pose significant risks in Neonatal Intensive Care Units (NICUs).
- High-level gastrointestinal colonization by SM was observed during a prolonged NICU outbreak.
- Early outbreak strains harbored a plasmid conferring resistance to gentamicin, tobramycin, and beta-lactam agents.
Purpose of the Study:
- To investigate the characteristics and clinical impact of a Serratia marcescens outbreak in a NICU.
- To identify risk factors and associated morbidities in neonates colonized or infected with SM.
- To evaluate the effectiveness of interventions in controlling the SM outbreak.
Main Methods:
- Observational study during a prolonged NICU outbreak.
- Analysis of SM strains, including plasmid carriage and antibiotic resistance profiles.
- Correlation of SM colonization with neonatal birth weight and clinical outcomes.
- Assessment of intervention impact on SM transmission and associated infections.
Main Results:
- SM colonization was linked to very low birth weight (<1500 g).
- In very low birth weight neonates, SM was associated with pneumonia, patent ductus arteriosus, congestive heart failure, and septicemia.
- In neonates >1500 g, SM was associated with bronchopulmonary dysplasia, respirator use, patent ductus arteriosus, and congestive heart failure.
- Frequent changing of respirator tubing reduced respiratory tract colonization and pneumonia.
- Contaminated sinks remained a source of multiresistant SM.
Conclusions:
- Serratia marcescens outbreaks in NICUs can lead to severe gastrointestinal and respiratory complications, especially in vulnerable neonates.
- Antibiotic resistance patterns, including plasmid-mediated resistance, are critical factors in outbreak dynamics.
- Environmental contamination, such as sinks and respirator equipment, contributes to sustained transmission.
- Interventions targeting environmental hygiene and equipment management are crucial for outbreak control.
Related Concept Videos
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...
 01:30
Development of Human Microbiota
 01:28
Development of the Oral Microbiota
 01:29
Staphylococcal Skin Infections
 01:18
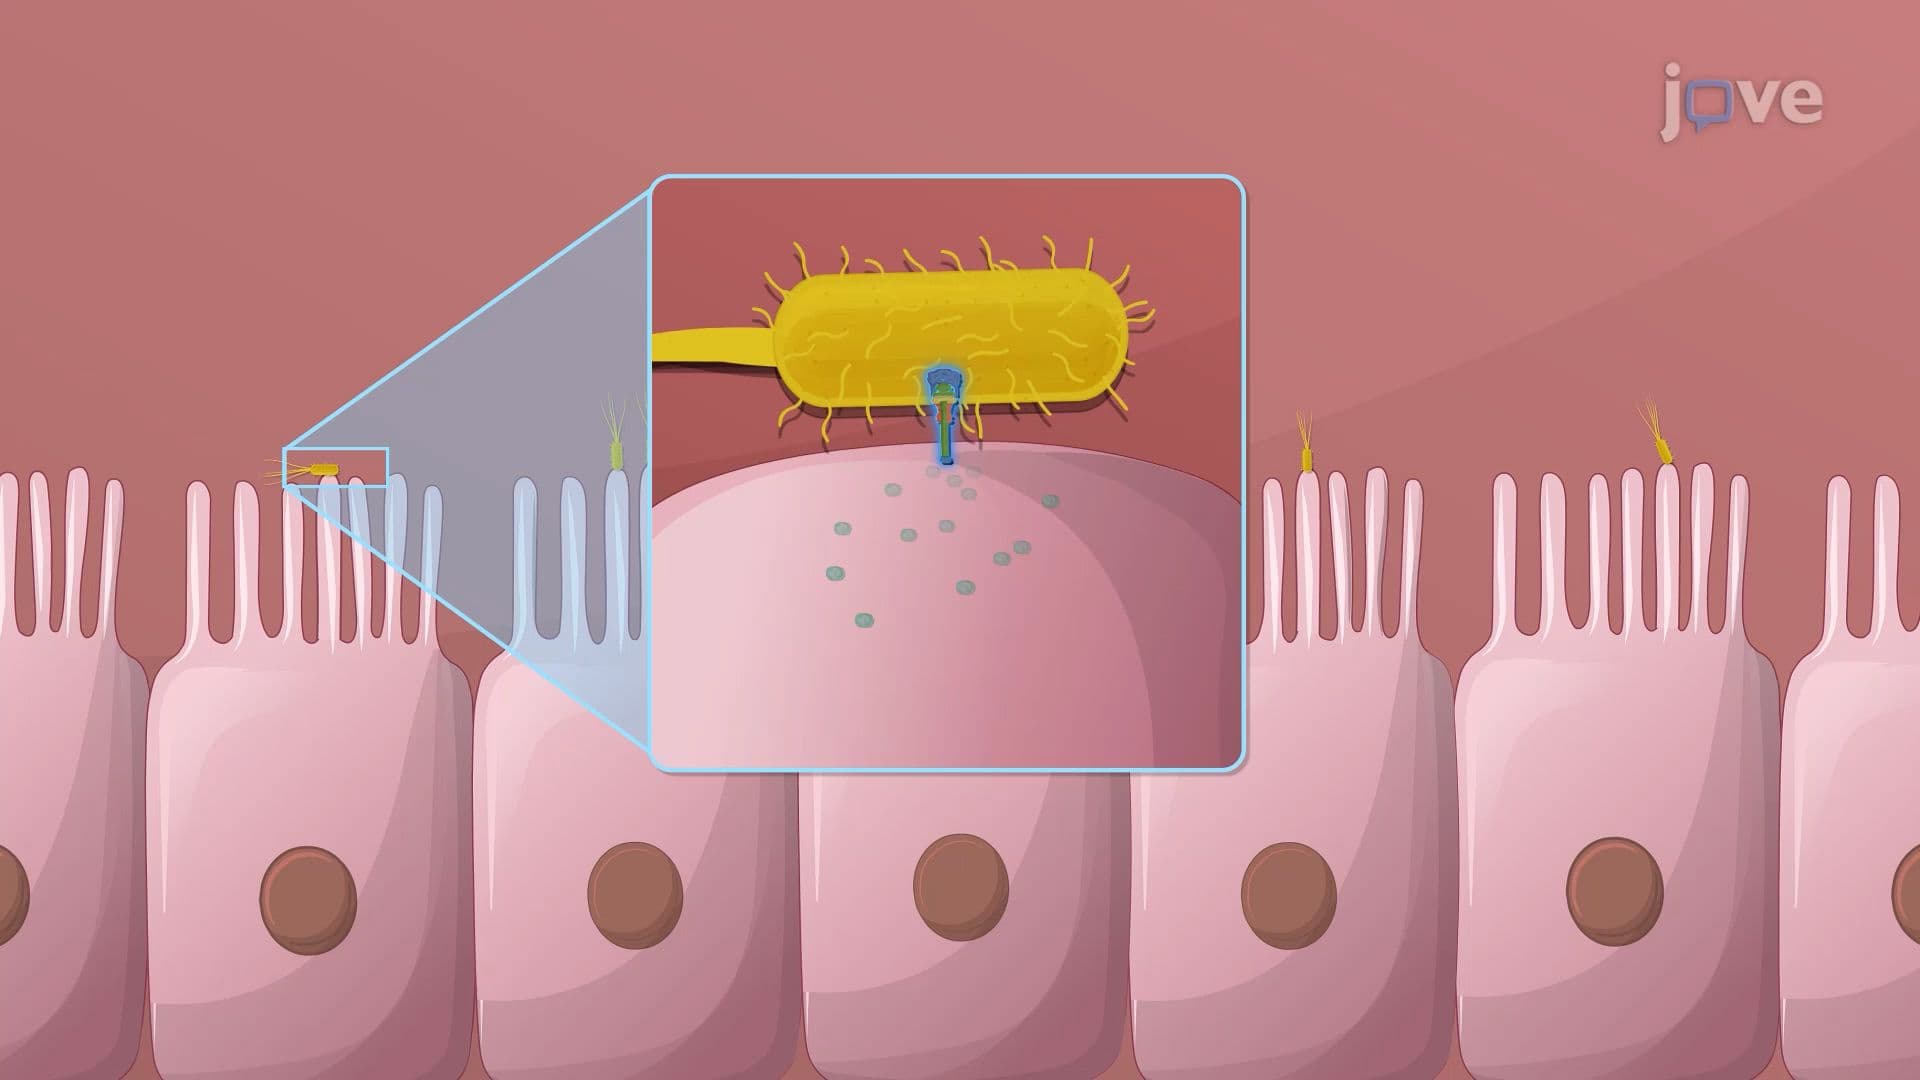
Bacterial Gastroenteritis
 01:12
Giardiasis