Related Experiment Video
Updated: Jun 24, 2025
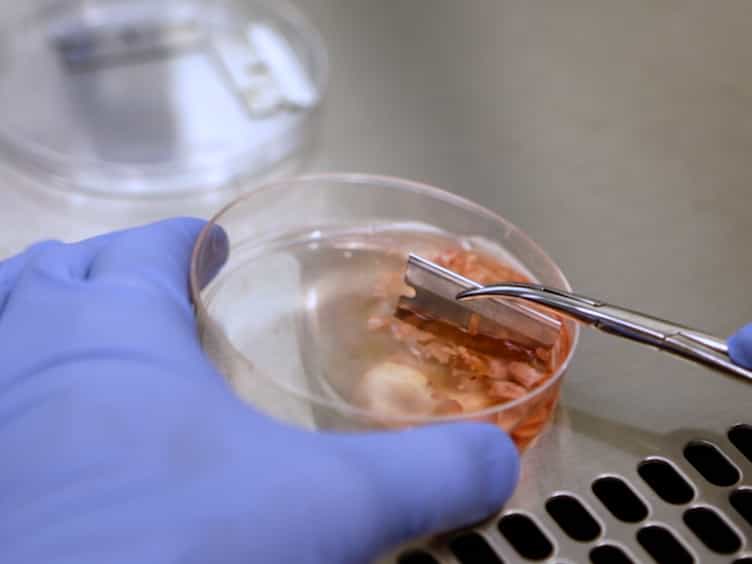

A Protocol for Rapid Post-mortem Cell Culture of Diffuse Intrinsic Pontine Glioma DIPG
Published on: March 7, 2017
Risk Factors for Pediatric Intracranial Neoplasms in the Kids' Inpatient Database
Anthony Price1,2, Sean O'Leary3,4, Hannah Parker3,4
1John Sealy School of Medicine, The University of Texas Medical Branch at Galveston, Galveston, Texas, USA, antprice@utmb.edu.

Insights
Pediatric brain cancer mortality is higher in females and Black patients compared to males and white patients. These disparities highlight the need for improved resource allocation in pediatric central nervous system (CNS) tumor care.
Area of Science:
- Pediatric Oncology
- Neuro-oncology
- Epidemiology
Background:
- Central nervous system (CNS) tumors are the leading cause of cancer-related mortality in children and adolescents.
- Previous research indicates racial disparities in intracranial cancer rates and other risk factors.
- This study utilizes the 2019 Kids' Inpatient Database (KID) to investigate these disparities.
Purpose of the Study:
- To analyze mortality rates and associated risk factors for pediatric brain and CNS tumors.
- To identify potential disparities in care based on race, sex, and socioeconomic factors.
- To provide data for improving resource allocation and care for pediatric CNS tumor patients.
Main Methods:
- Analysis of 7,818 pediatric patients (<21 years) with malignant neoplasms of the brain, brainstem, and cerebral meninges from the 2019 Kids' Inpatient Database (KID).
- Evaluation of modifiable risk factors (hospital region, insurance, city size, income, hospital type) and non-modifiable factors (race, sex).
- Statistical analysis using χ2 test with Yates' continuity correction and Tukey's ANOVAs in Excel and GraphPad Prism 9.
Main Results:
- Significant differences in mortality rates were observed between females (2.88%) and males (1.99%), and across racial groups: Black (4.17%), Hispanic (2.95%), Asian/Pacific Islander (3.86%), compared to White (1.68%).
- Black patients exhibited significantly higher mortality across all races (p < 0.01).
- No significant difference in mortality was found based on hospital type or insurance status after accounting for race. Significant racial differences were noted in length of stay and charges.
Conclusions:
- Findings confirm that gender and race are significant factors influencing mortality in pediatric intracranial neoplasms.
- The study identifies significant disparities but does not pinpoint root causes.
- Results emphasize the need for improved national resource allocation to enhance care for pediatric CNS tumor patients.
Introduction:
In children and adolescents, brain and central nervous system (CNS) tumors are the leading types of cancers. Past studies have found differing rates of intracranial cancers among races and identified additional cancer risk factors. This study aimed to see if these differences can be substantiated with further investigation of the latest version (2019) of the Kids' Inpatient Database (KID).
Methods:
A total of 7,818 pediatric patients <21 years old in KID with ICD-10 codes consisting of malignant neoplasms of the brain, brainstem, and cerebral meninges (C700, C709-C719) were queried. Modifiable risk factors evaluated include: hospital region, insurance type, hospital city size, the average income of patient zip code, and location/teaching status of a hospital. Non-modifiable risk factors were race and sex at birth. Dependent variables were tested in Excel and GraphPad Prism 9 using a χ2 test with Yates' continuity correction and Tukey's one-way and two-way ANOVAs.
Results:
Mortality rates of females (2.88%) compared to males (1.99%) were significant (p < 0.05). Mortality was (4.17%) in black patients compared to (1.68%) for white (p < 0.0001), Hispanic mortality (2.95%) compared to white (p < 0.01), and mortality of Asian/Pacific Islander (3.86%) compared to white (p < 0.01). Black patients had significantly higher mortality than white, Hispanic, Asian/Pacific Islander, Native American, and other races overall (p < 0.01). There was no significant difference in the mortality rates between children's hospitals and large hospitals for any race. After accounting for patient race, mortality was still not significantly different for patients with Medicaid insurance compared to non-Medicaid insurance types. Of the children treated at children's hospitals, the most transferred in from outside hospitals were Native American (20.00%) followed by Asian/Pacific Islander (15.09%) then Hispanic patients (13.67%). A significant difference between races was also seen regarding length of stay (p < 0.001) and number of charges (p < 0.001).
Conclusion:
These findings confirm prior studies suggesting gender and race are significant factors in mortality rates for children with intracranial neoplasms. However, the findings do not identify the root causes of these discrepancies but may serve as an impetus for clinicians, healthcare administrators, and governmental leaders to improve national resource allocation to better care for pediatric patients with intracranial neoplasms.


