Related Experiment Video
Updated: Jun 24, 2025


Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Creatine homeostasis and the kidney: comparison between kidney transplant recipients and healthy controls
Adrian Post1, Dion Groothof2, Daan Kremer2
1Department of Internal Medicine, University Medical Center Groningen, University of Groningen, Groningen, 9713 GZ, The Netherlands. a.post01@umcg.nl.

Abstract:
Creatine is a natural nitrogenous organic acid that is integral to energy metabolism and crucial for proper cell functioning. The kidneys are involved in the first step of creatine production. With kidney transplantation being the gold-standard treatment for end-stage kidney disease, kidney transplant recipients (KTR) may be at risk of impaired creatine synthesis. We aimed to compare creatine homeostasis between KTR and controls. Plasma and urine concentrations of arginine, glycine, guanidinoacetate, creatine and creatinine were measured in 553 KTR and 168 healthy controls. Creatine intake was assessed using food frequency questionnaires. Iothalamate-measured GFR data were available in subsets of 157 KTR and 167 controls. KTR and controls had comparable body weight, height and creatine intake (all P > 0.05). However, the total creatine pool was 14% lower in KTR as compared to controls (651 ± 178 vs. 753 ± 239 mmol, P < 0.001). The endogenous creatine synthesis rate was 22% lower in KTR as compared to controls (7.8 ± 3.0 vs. 10.0 ± 4.1 mmol per day, P < 0.001). Despite lower GFR, the plasma guanidinoacetate and creatine concentrations were 21% and 41% lower in KTR as compared to controls (both P < 0.001). Urinary excretion of guanidinoacetate and creatine were 66% and 59% lower in KTR as compared to controls (both P < 0.001). In KTR, but not in controls, a higher measured GFR was associated with a higher endogenous creatine synthesis rate (std. beta: 0.21, 95% CI: 0.08; 0.33; P = 0.002), as well as a higher total creatine pool (std. beta: 0.22, 95% CI: 0.11; 0.33; P < 0.001). These associations were fully mediated (93% and 95%; P < 0.001) by urinary guanidinoacetate excretion which is consistent with production of the creatine precursor guanidinoacetate as rate-limiting factor. Our findings highlight that KTR have a disturbed creatine homeostasis as compared to controls. Given the direct relationship of measured GFR with endogenous creatine synthesis rate and the total creatine pool, creatine supplementation might be beneficial in KTR with low kidney function.Trial registration ID: NCT02811835.Trial registration URL: https://clinicaltrials.gov/ct2/show/NCT02811835 .


Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
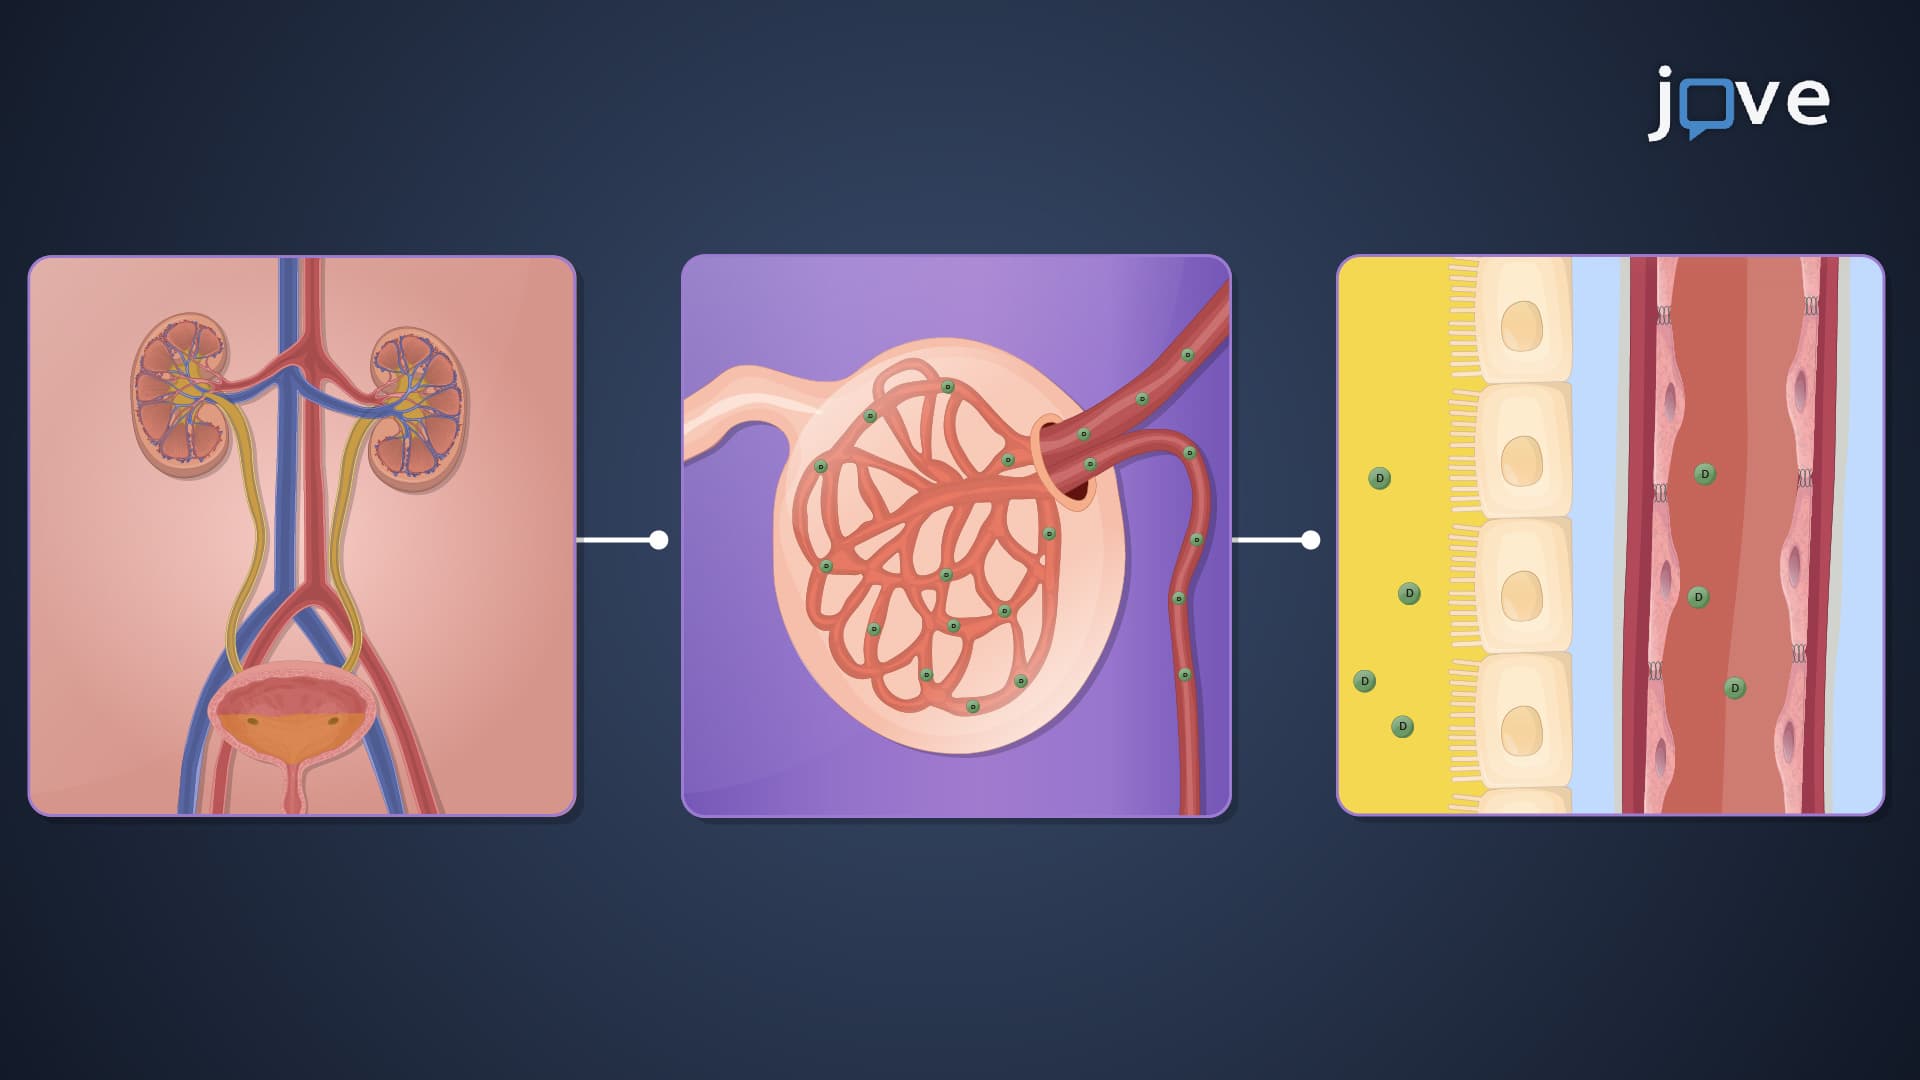
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:22
Heart Failure Drugs: Diuretics