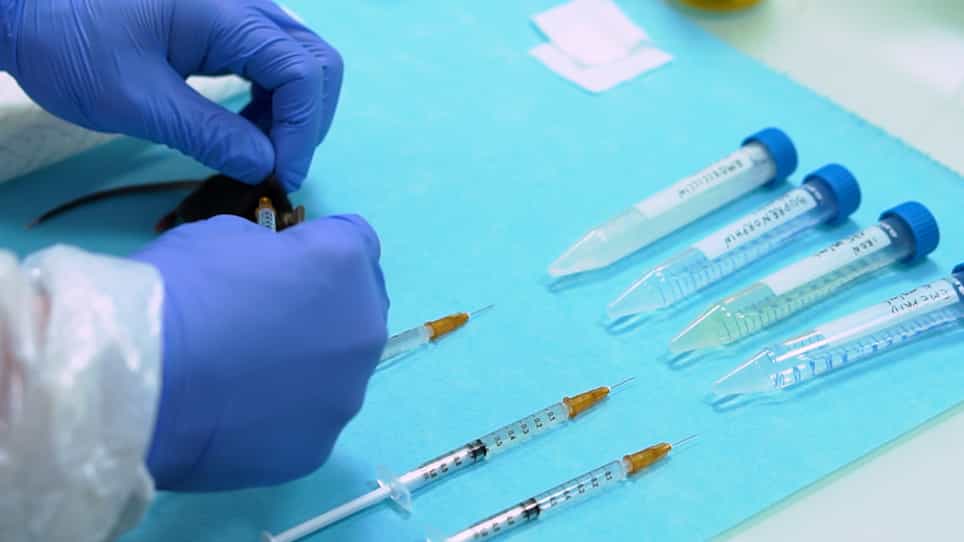
Related Experiment Video
Updated: Jun 23, 2025


A Murine Model of Vertical Sleeve Gastrectomy
Published on: December 18, 2017
Short-term effects of gastric bypass versus sleeve gastrectomy on high LDL cholesterol: The BASALTO randomized
David Benaiges1,2,3,4,5, Albert Goday6,7,8,9, Anna Casajoana7,10
1Department of Endocrinology and Nutrition, Hospital del Mar, Passeig Marítim, 25-29, Barcelona, 08003, Spain. dbenaiges@psmar.cat.

Background:
There has been a substantial increase in the use of laparoscopic sleeve gastrectomy (SG) to treat morbid obesity despite observational evidence demonstrating the superiority of Roux-en-Y gastric bypass (RYGB) for reducing low-density lipoprotein (LDL) cholesterol. The main aim was to ascertain whether high LDL cholesterol levels should be considered when selecting the most appropriate surgical procedure for each patient (RYGB or SG).
Methods:
In this single-center, randomized clinical trial using intention-to-treat analysis, 38 patients with severe obesity and elevated levels of LDL cholesterol were randomly assigned to undergo RYGB or SG. The primary outcome was LDL cholesterol remission at 12 months, defined as LDL cholesterol < 3.36 nmol/l without lipid-lowering medications. Secondary outcomes included changes in weight, other comorbidities, qualitative lipoprotein traits, cholesterol esters, glycoproteins, cholesterol absorption and synthesis metabolites and complications.
Results:
Intention-to-treat analysis revealed that LDL cholesterol remission occurred in 66.6% of RYGB patients compared to 27.8% of SG patients (p = 0.019). Among patients completing follow-up, RYGB demonstrated superior remission (80.0% vs. 29.4%, p = 0.005). Exclusive benefits of RYGB included a reduction in large, medium, and small LDL particles. Cholesterol absorption markers showed differential behavior after both techniques: campesterol (Δ -15.2 µg/mg, 95% CI -30.2 to -0.1) decreased after RYGB, and sitosterol (Δ 21.1 µg/mg, 95% CI 0.9 to 41.2), cholestanol (Δ 30.6 µg/mg, 95% CI 14.8 to 57.9) and campesterol (Δ 18.4 µg/mg, 95% CI 4.4 to 32.3) increased after SG. No differences in weight loss, cholesterol esters, glycoproteins, cholesterol synthesis metabolites or postoperative complications were observed between techniques.
Conclusion:
In conclusion, RYGB is superior to SG in terms of short-term of high LDL cholesterol remission. Furthermore, RYGB also led to a greater improvement in lipoprotein parameters that confer an atherogenic profile. Therefore, the presence of elevated levels of LDL cholesterol should be considered when determining the optimal bariatric surgery procedure for each patient.
Trial Registration:
Clinicaltrials.gov number, NCT03975478).