Related Experiment Video
Updated: Jun 23, 2025

Diagnosis and Surgical Treatment of Human Brucellar Spondylodiscitis
Published on: May 23, 2021
[Nonspecific craniovertebral spondylitis]
I Yu Lisitsky1, A V Lychagin1, A Yu Zarov1
1Sechenov First Moscow State Medical University, Moscow, Russia.

Objective:
To analyze surgical strategy for nonspecific spondylitis of the craniovertebral region (CVR) taking into account clinical features and morphological signs of disease.
Material And Methods:
Eight patients with nonspecific spondylitis of CVR underwent surgery (4 women and 4 men aged 31-75 years). Three patients had pain syndrome, 5 ones - conduction disorders. Combined interventions were performed in 5 patients with neurological disorders. Of these, 3 patients underwent transoral decompression with subsequent occipitospondylodesis. In other cases, stages of surgical treatment were reverse. Four patients underwent simultaneous interventions, 1 patient - with 7-day interval. Patients with pain syndrome underwent occipitospondylodesis.
Results:
In all patients, postoperative VAS score of pain syndrome decreased by 5-7 points (mean 5.5). Among 5 patients with conduction symptoms, regression of neurological disorders 1 year after surgery was achieved in 2 cases, and complete recovery was observed in 3 patients (Frankel E). In all cases, examination confirmed relief of inflammatory process and no compression of the spinal cord and medulla oblongata. One patient had a dehiscence of the wound edges of posterior pharyngeal wall, and another one had implant fracture in 3 years after surgery.
Conclusion:
Active surgical approach is reasonable for nonspecific spondylitis of CVR. Craniocervical fixation eliminates pain and risk of neurological complications following atlantoaxial instability. Conduction disorders require simultaneous transoral decompression and occipitospondylodesis in patients with nonspecific purulent craniovertebral lesions. Impaired head tilt complicates transoral stage. In this regard, it is more rational to carry out craniocervical fixation at the last stage.


Related Concept Videos
 01:28
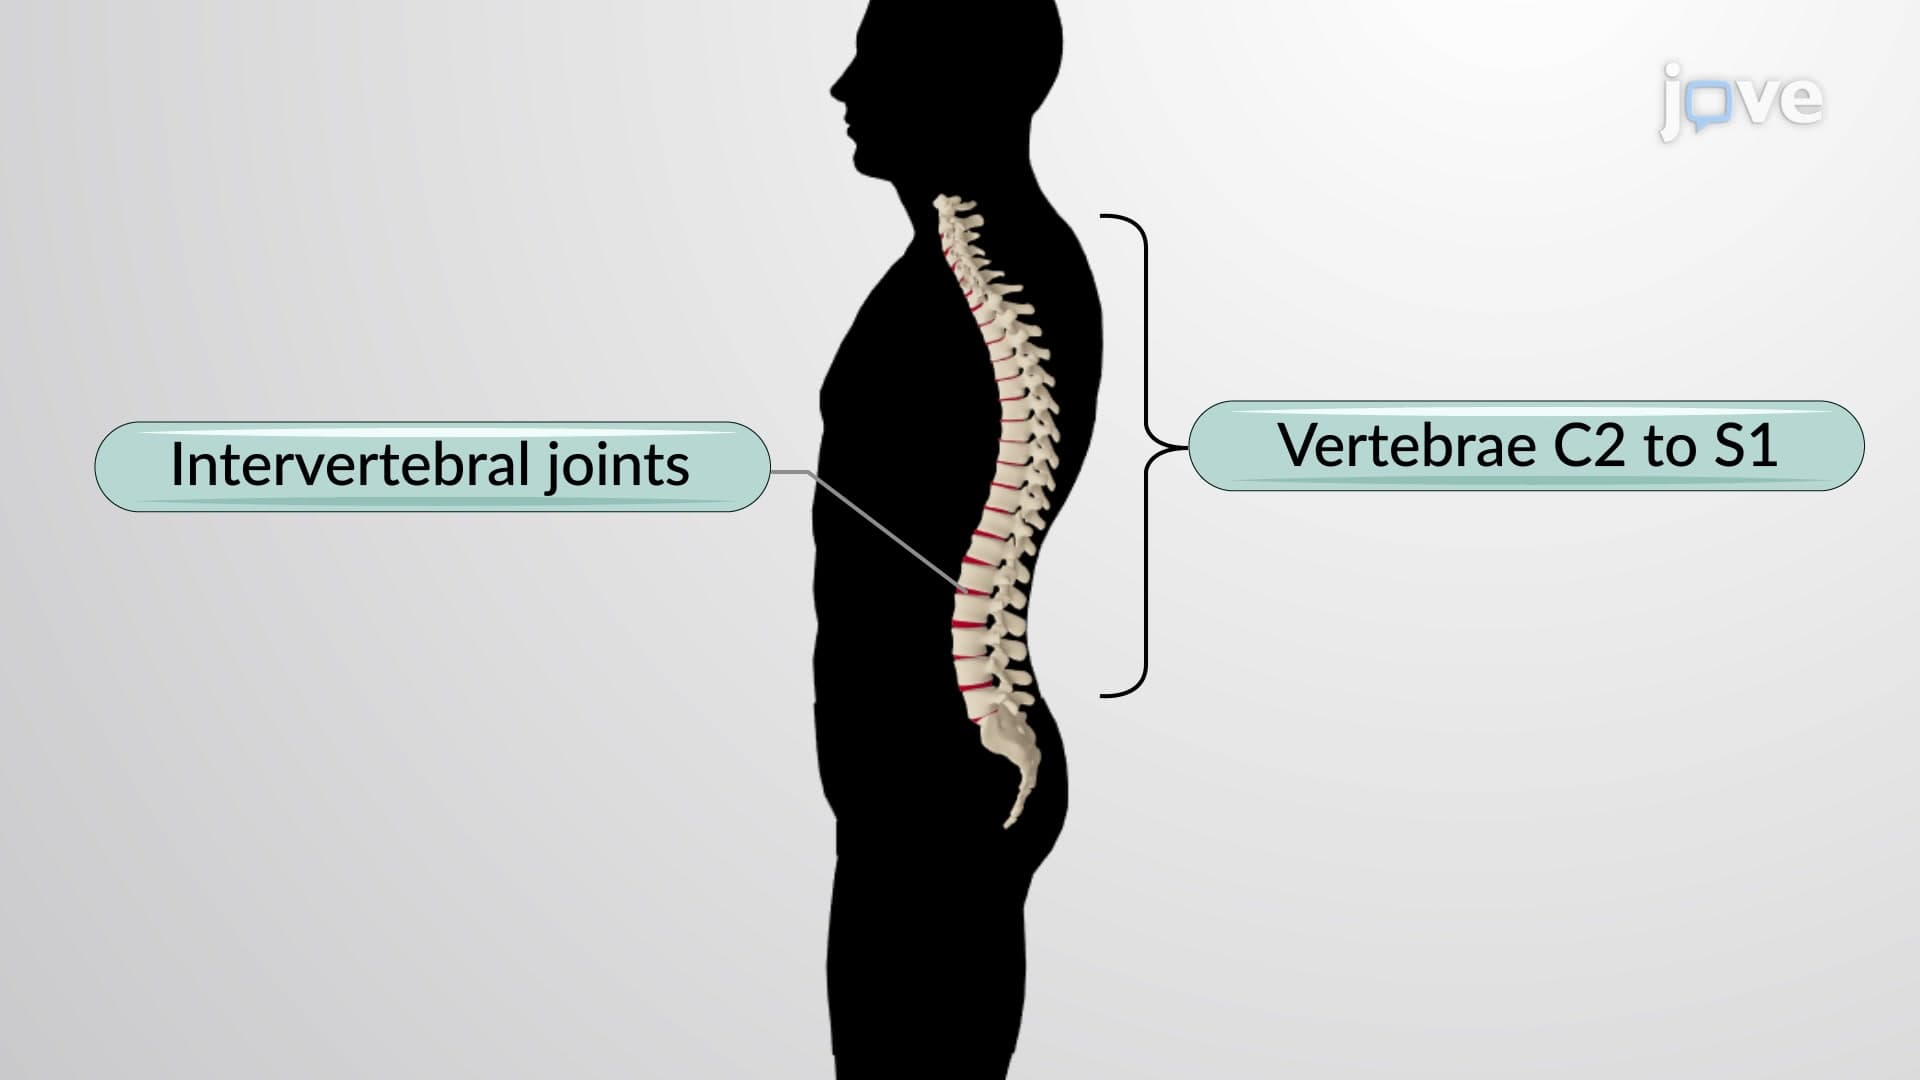
Articulations of the Vertebral Column
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:22
Somatic Spinal Reflexes
One of the most well-known somatic spinal reflexes is the stretch reflex, which is activated by the sudden stretching of a muscle. This reflex involves the activation of specialized sensory receptors called muscle spindles, which are located in the muscle tissue and detect changes in the length and speed of muscle contractions. When a muscle is suddenly...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:16
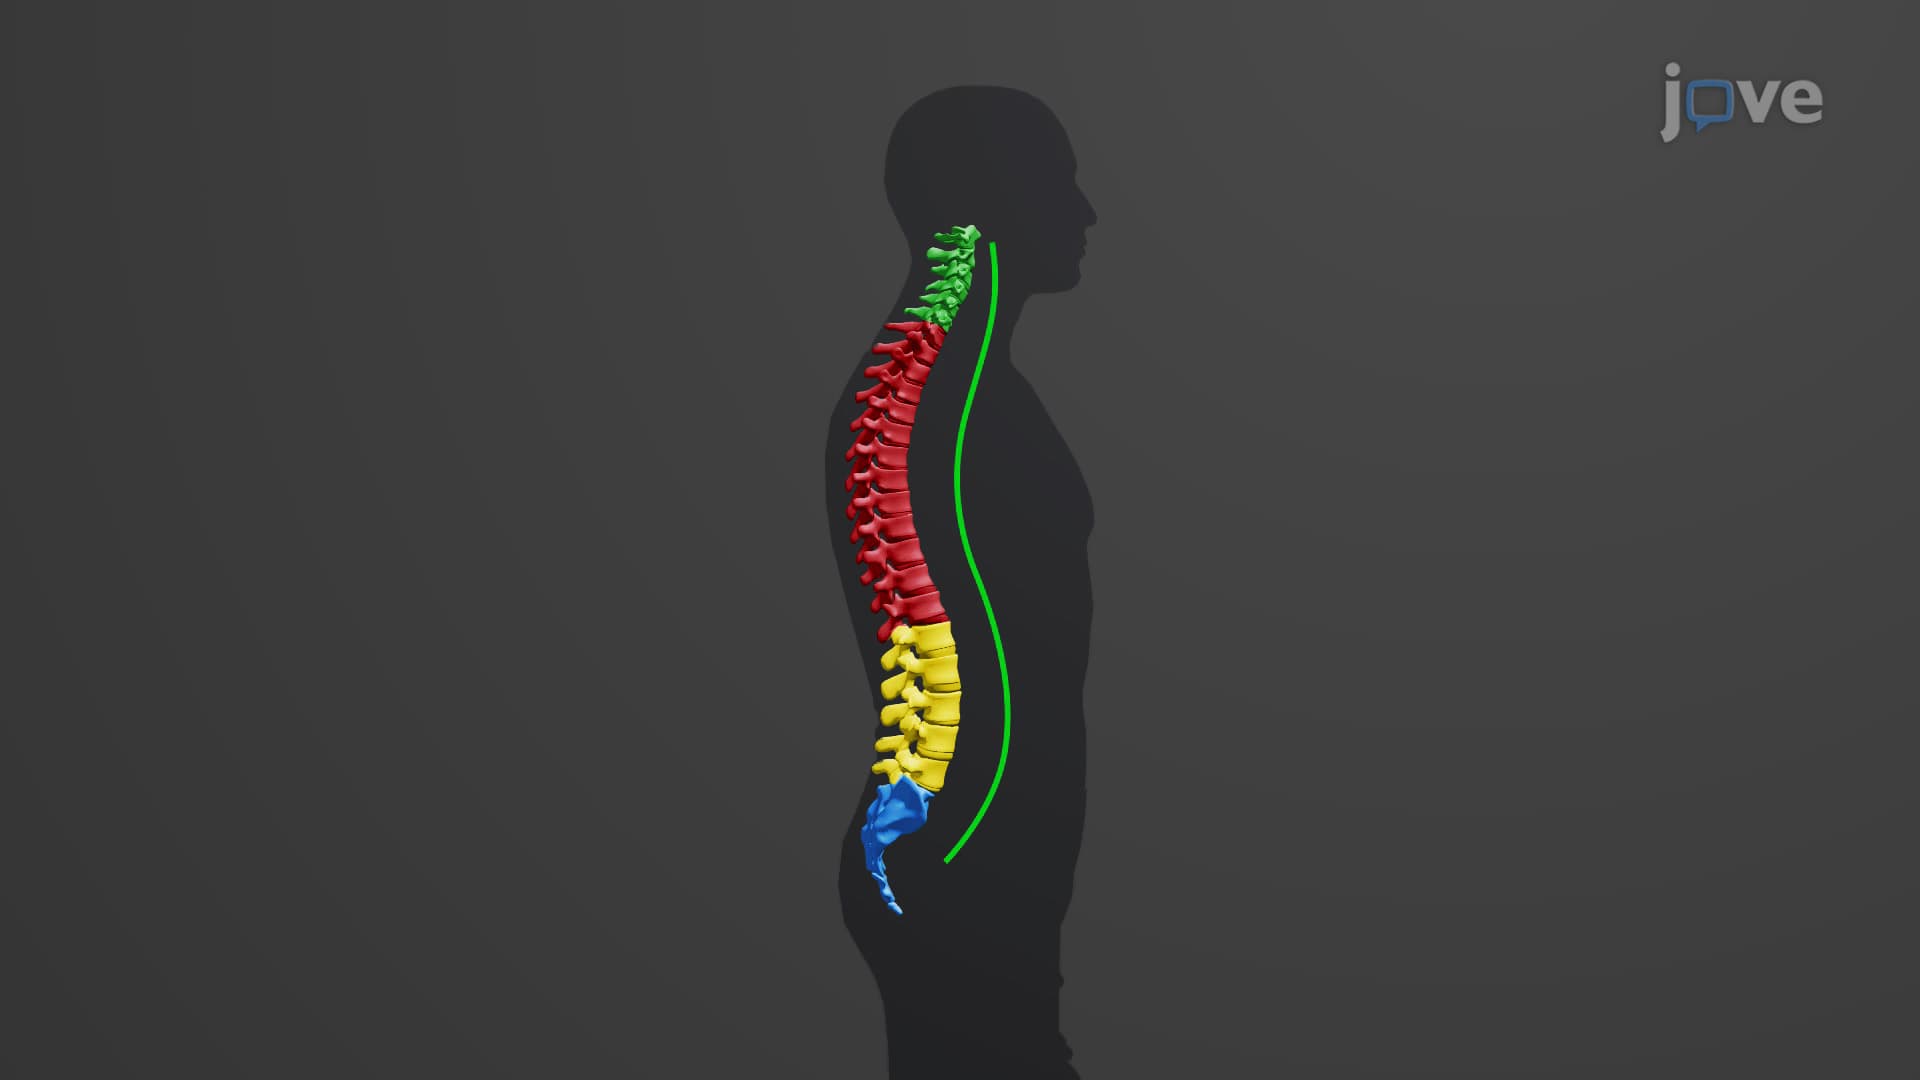
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...