Related Experiment Video
Updated: Jun 23, 2025


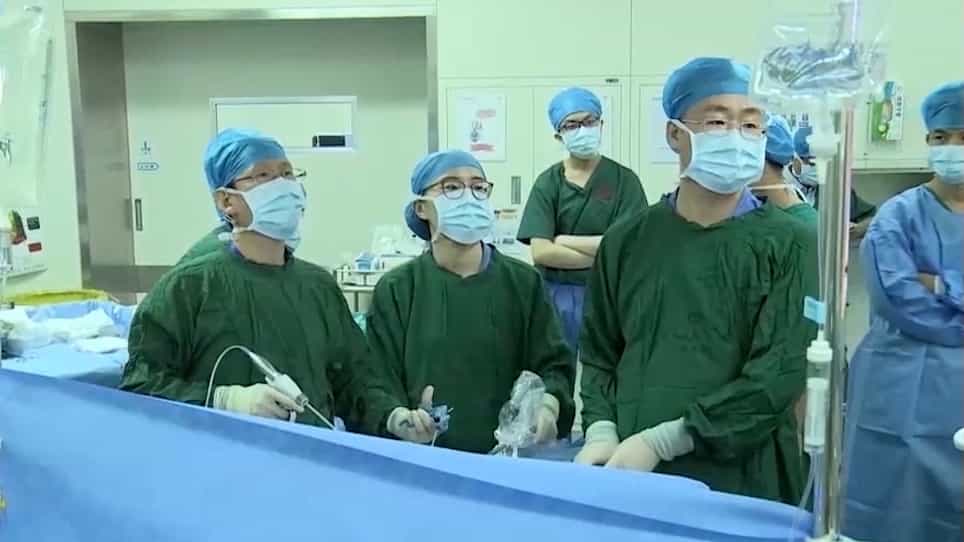
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
[A Case of Recurrent Gastric GIST with Long-Term Survival after Multidisciplinary Treatment]
Ryosuke Machi1, Kaname Ishii, Kentaro Hayashi
1Dept. of Surgery, Public Central Hospital of Matto Ishikawa.

Abstract:
An 80-year-old male patient presented with a 2.5 cm-sized submucosal tumor on the greater curvature side of the upper gastric body during an endoscopic examination in 200X. We diagnosed gastric GIST by biopsy and performed laparoscopic- assisted partial gastrectomy. Imatinib was started as postoperative adjuvant therapy, but was discontinued after 1 month due to eyelid edema. The patient was followed up with a contrast-enhanced CT scan and a PET-CT scan. A 7 cm-sized mass in the gastrosplenic region was discovered on a 200X+7 years CT scan; this mass was thought to be possible recurrence of peritoneal dissemination. The patient did not want to undergo surgery or drug treatment, and was followed up. Five months later he complained of abdominal pain. The CT scan showed that the mass had shrunk slightly, but a small amount of ascites was observed, and tumor rupture was suspected. Therefore, we performed resection of the tumor in the office. Numerous disseminated nodules were found in the intra-abdominal cavity. Pathological examination revealed recurrence of GIST, and the patient was started on imatinib 200 mg/day. The dose was temporarily increased to 300 mg/day, but was reduced again to 200 mg/day 1 month later due to eyelid edema. Thereafter, the dose was temporarily discontinued due to stomatitis, and from 200X+8 years, 200 mg/day was administered for 2 weeks and then discontinued for 2 weeks. At present, 14 years after the first surgery and 6 years after recurrence, he remains alive thanks to imatinib continuation.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...