Related Experiment Video
Updated: Aug 9, 2026


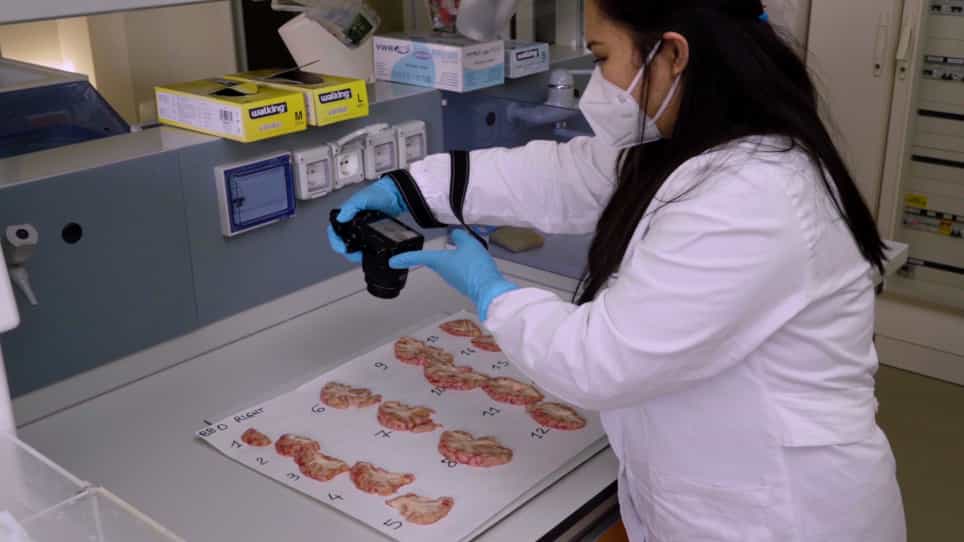
Symmetric Bihemispheric Postmortem Brain Cutting to Study Healthy and Pathological Brain Conditions in Humans
Published on: December 18, 2016
Cerebral Amyloid Angiopathy-Related Inflammation and Biopsy-Positive Primary Angiitis of the CNS: A Comparative Study
Lou Grangeon1, Grégoire Boulouis1, Jean Capron1
1From Neurology (L.G., O.O.-W., A.T.-B., D.W., P.V., G.Q.), CHU de Rouen; Radiology (G.B., F.B.), CHRU de Tours; Service des Urgences Neurovasculaires (J.C., S.A.), Hôpital Pitié-Salpêtrière, Sorbonne Université, AP-HP, Stare Team, iCRIN, Institut du Cerveau, Paris; Neurology (D. Renard, A.W., E. Thouvenot), CHU de Nîmes; Neurology (N.R., C.G., J.P.), CHU de Toulouse; Neurology (X.A., C.A., P.M.L.), CHU de Montpellier; Radiology (E.G.), CHU de Rouen; Neurology (P.K.), CHU de Luxembourg; Neurology (D.S., N.O., T.A.), CH de Perpignan; Neurology (M.F.), Hospices Civils de Lyon; Neurology (F.P.), CH de Versailles; Neurology (G.T., C.I.), GHU Paris; Geriatric Medicine (M. Verny), Hôpital Pitié-Salpêtrière, AP-HP, Paris; Neurology (L.H.), CHRU de Nancy; Neurology (M. Gaudron), CHRU de Tours; Neurology (S.V.), CHU de Rennes; Neurology (N.D., H.Z.), CHU de Lille; Neurology (B.G.), CHU de Nantes; Université Grenoble Alpes (O.D.), INSERM, U1216, Neurology, CHU de Grenoble Alpes, Grenoble Institute Neurosciences; Neurology (S.G.), CHU de Angers; UR2CA-URRIS (B.C.), Stroke Unit, CHU Pasteur 2, Nice Cote d'Azur University; Internal Medicine (M.L., S.B.), CHU de Nice; Internal Medicine (M.G.-V.), Hôpital Croix-Rousse, Lyon; Neurology (L.K.), CHRU de Strasbourg; Neurology (L.D.), CH de Lorient, France; Neurology (N.L.), CHU de Liège/CHR la Citadelle, Liège, Belgique; Neurology (S.L.), Hôpital du Sacré-cœur de Montréal; Neurology (A.P.), CH de l'Université de Montréal, Québec, Canada; Internal Medicine (A.R., B.T.), Université Paris-Cité, Hôpital Cochin, AP-HP; Neurology (D.W.-L.), Hôpital Foch, Suresnes; Internal Medicine (M. Vautier), Hôpital Pitié-Salpêtrière, Paris; Neurology (S.C.), CH de Gonesse; Internal Medicine (A. Neel), CHU de Nantes; Université Caen-Normandie (O.M., R.S., E. Touzé, A. Nehme), Neurology, CHU de Caen-Normandie; Internal Medicine (T.P.), Hôpital Bichat; Internal Medicine (C.C.-O.), Hôpital Lariboisière; Neurology (E.J.), Hôpital Lariboisière, Paris; Neurology (M.S.), HIA Sainte-Anne, Toulon; Neurology (L.P.-M.), CHU de Clermont-Ferrand; Neurology (M.A.K.), CH Troyes; Neurology (F.L.), CH d'Orsay; Neurology, CH de Saint-Denis; Université de Franche-Comté (E.M.), LINC Laboratoire de Recherches Intégratives en Neurosciences et Psychologie Cognitive et CMRR, Service de Neurologie, CHU de Besançon; Neurology (Q.T., M. Graber), CHU de Dijon; Neurology (Y.B.), CH de Béziers; Neurology (G.B.-F., D. Ratiu), CH de Narbonne, France; Vasculitis Clinic (C.P.), Mount Sinai Hospital, University of Toronto, Ontario, Canada; and Université Caen-Normandie (H.D.B.), Internal Medicine, CHU de Caen-Normandie, France.

Background And Objectives:
Cerebral amyloid angiopathy-related inflammation (CAA-RI) and biopsy-positive primary angiitis of the CNS (BP-PACNS) have overlapping clinicoradiologic presentations. It is unknown whether clinical and radiologic features can differentiate CAA-RI from BP-PACNS and whether both diseases have different relapse rates. The objectives of this study were to compare clinicoradiologic presentations and relapse rates in patients with CAA-RI vs BP-PACNS.
Methods:
Patients with CAA-RI and BP-PACNS were enrolled from 2 retrospective multicenter cohorts. Patients with CAA-RI were biopsy-positive or met probable clinicoradiologic criteria. Patients with BP-PACNS had histopathologic confirmation of CNS angiitis, with no secondary etiology. A neuroradiologist read brain MRIs, blinded to the diagnosis of CAA-RI or BP-PACNS. Clinicoradiologic features were compared using univariable logistic regression models. Relapse rates were compared using a univariable Fine-Gray subdistribution hazard model, with death as a competing risk.
Results:
This study enrolled 104 patients with CAA-RI (mean age 73 years, 48% female sex) and 52 patients with BP-PACNS (mean age 45 years, 48% female sex). Patients with CAA-RI more often had white matter hyperintense lesions meeting the probable CAA-RI criteria (93% vs 51%, p < 0.001), acute subarachnoid hemorrhage (15% vs 2%, p = 0.02), cortical superficial siderosis (27% vs 4%, p < 0.001), ≥1 lobar microbleed (94% vs 26%, p < 0.001), past intracerebral hemorrhage (17% vs 4%, p = 0.04), ≥21 visible centrum semiovale perivascular spaces (34% vs 4%, p < 0.01), and leptomeningeal enhancement (70% vs 27%, p < 0.001). Patients with BP-PACNS more often had headaches (56% vs 31%, p < 0.01), motor deficits (56% vs 36%, p = 0.02), and nonischemic parenchymal gadolinium enhancement (82% vs 16%, p < 0.001). The prevalence of acute ischemic lesions was 18% in CAA-RI and 22% in BP-PACNS (p = 0.57). The features with the highest specificity for CAA-RI were acute subarachnoid hemorrhage (98%), cortical superficial siderosis (96%), past intracerebral hemorrhage (96%), and ≥21 visible centrum semiovale perivascular spaces (96%). The probable CAA-RI criteria had a 71% sensitivity (95% CI 44%-90%) and 91% specificity (95% CI 79%-98%) in differentiating biopsy-positive CAA-RI from BP-PACNS. The rate of relapse in the first 2 years after remission was lower in CAA-RI than in BP-PACNS (hazard ratio 0.46, 95% CI 0.22-0.96, p = 0.04).
Conclusion:
Clinicoradiologic features differed between patients with CAA-RI and those with BP-PACNS. Specific markers for CAA-RI were hemorrhagic signs of subarachnoid involvement, past intracerebral hemorrhage, ≥21 visible centrum semiovale perivascular spaces, and the probable CAA-RI criteria. A biopsy remains necessary for diagnosis in some cases of CAA-RI. The rate of relapse in the first 2 years after disease remission was lower in CAA-RI than in BP-PACNS.