Related Experiment Video
Updated: Jun 23, 2025
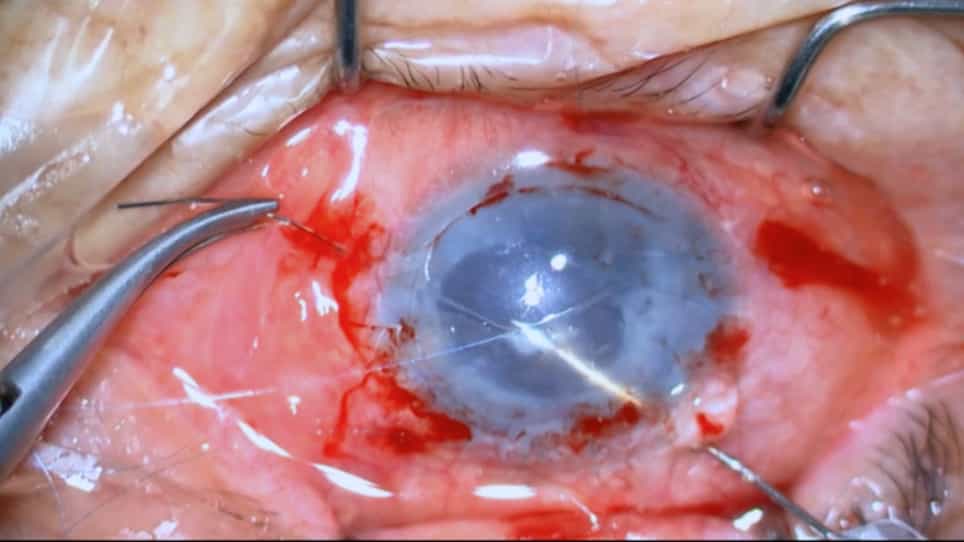

Iris Fixation via External Pentagram Suturing
Published on: May 5, 2022
A Case of Refractory Posterior Scleritis with Marked Retinochoroidal Detachment Associated with Panuveitis
Yoshihiro Nakagawa, Takahiro Suzuki1, Ami Sahashi
1Department of Ophthalmology, Tokai University School of Medicine, 143 Shimokasuya, Isehara, Kanagawa 259-1193, Japan. taka-su@tokai.ac.jp.

Abstract:
An 84-year-old man presented with decreased right-eye visual acuity. Upon initial examination, the rightand left-eye visual acuities were 0.03 and 1.2, respectively; moreover, the right- and left-eye intraocular pressure was 12 mmHg and 13 mmHg, respectively. Examination revealed a shallow anterior chamber of the right eye, anterior chamber inflammation, vitreous opacity, and marked retinochoroidal detachment. Optical coherence tomography (OCT) revealed retinal detachment (RD) and choroidal folds; moreover, B-scan ultrasonography (B-scan) showed RD as well as thickened sclera with fluid in Tenon's space. Fluorescent fundus angiography revealed hyperfluorescence in the optic disc and vascular hyperpermeability in the right eye. The left eye lacked extra-ocular symptoms or abnormalities. The right ocular axis measured 23.4 mm with no apparent subretinal fluid migration due to positional changes. Accordingly, the patient was diagnosed with panuveitis associated with posterior scleritis and immediately started on 40 mg prednisolone, which improved his symptoms. However, at 3 post-treatment months, choroidal folds were observed and was restarted on 20 mg prednisolone. The choroidal folds subsequently disappeared, with a current visual acuity of 0.3 in the right eye and no recurrence. Our findings indicated the utility of accurate diagnosis of posterior scleritis by B-scan and prompt systemic steroid administration.


