Splenic abscess and infective endocarditis
Related Experiment Video
Updated: Jun 23, 2025

Visualization of Streptococcus pneumoniae within Cardiac Microlesions and Subsequent Cardiac Remodeling
Published on: April 7, 2015
Monique Boukobza1, Lionel Rebibo2,3, Emila Ilic-Habensus4
1Department of Radiology, Bichat-Claude Bernard University Hospital, Assistance Publique-Hôpitaux de Paris, 46 Rue Henri Huchard, 75018, Paris, France. m.boukobza@orange.fr.

Objective:
To determine the background, bacteriological, clinical and radiological findings, associated lesions, treatment and outcome of splenic abscesses (SAs) in infective endocarditis (IE).
Methods:
Retrospective study (2005-2021) of 474 patients with definite IE. The diagnosis of SA was made in 36 (7.6%) patients (31, 86.1%, males, mean age = 51.3) on abdominal CT.
Results:
The main implicated organisms were Streptococcus spp (36.1%), Enterococcus faecalis (27.7%), Staphyloccus spp (19.4%). Rare agents were present in 10 patients (27.8%). Pre-existing conditions included a prosthetic valve (19.4%), previous IE (13.9%), intravenous drug use (8.4%), diabetes (25%) alcohol abuse (13.9%), liver disease (5.5%). Vegetations ≥ 15 mm were present in 36.1%. Common presentations were abdominal pain (19.4%) and left-sided pleural effusion (16.5%). SA were more often small (50%; 7 multiple) than large (36.1%; 1 multiple) or microabscesses (13.9%, 3 multiple). Associated complications were extrasplenic abscesses (brain, 11.1%; lung, 5.5%; liver, 2.8%), infectious aneurysms (16.7%: 3 intracranial, 1 splenic, 1 hepatic, 1 popliteal), emboli (brain, 52.8%; spleen, 44.4%, 5 evolving to SA; kidney, 22.2%; aorta, 2.8%), osteoarticular infections (25%). Twenty-eight (77.8%) patients only received antimicrobials, 7 (19.4%) underwent splenectomy, after cardiac surgery in 5. One had percutaneous drainage. The outcome was uneventful (follow-up 3 months-14 years; mean: 17.2 months).
Conclusion:
In SA-IE patients, the prevalence of vegetation size, Enterococcus faecalis, rare germs, diabetes, osteo-arthritic involvement and cancer was higher than in non-SA patients. Some SAs developed from splenic infarcts. IE-patients with evidence of splenic emboli should be evaluated for a possible abcedation. Cardiac surgery before splenectomy was safe.


Related Concept Videos
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
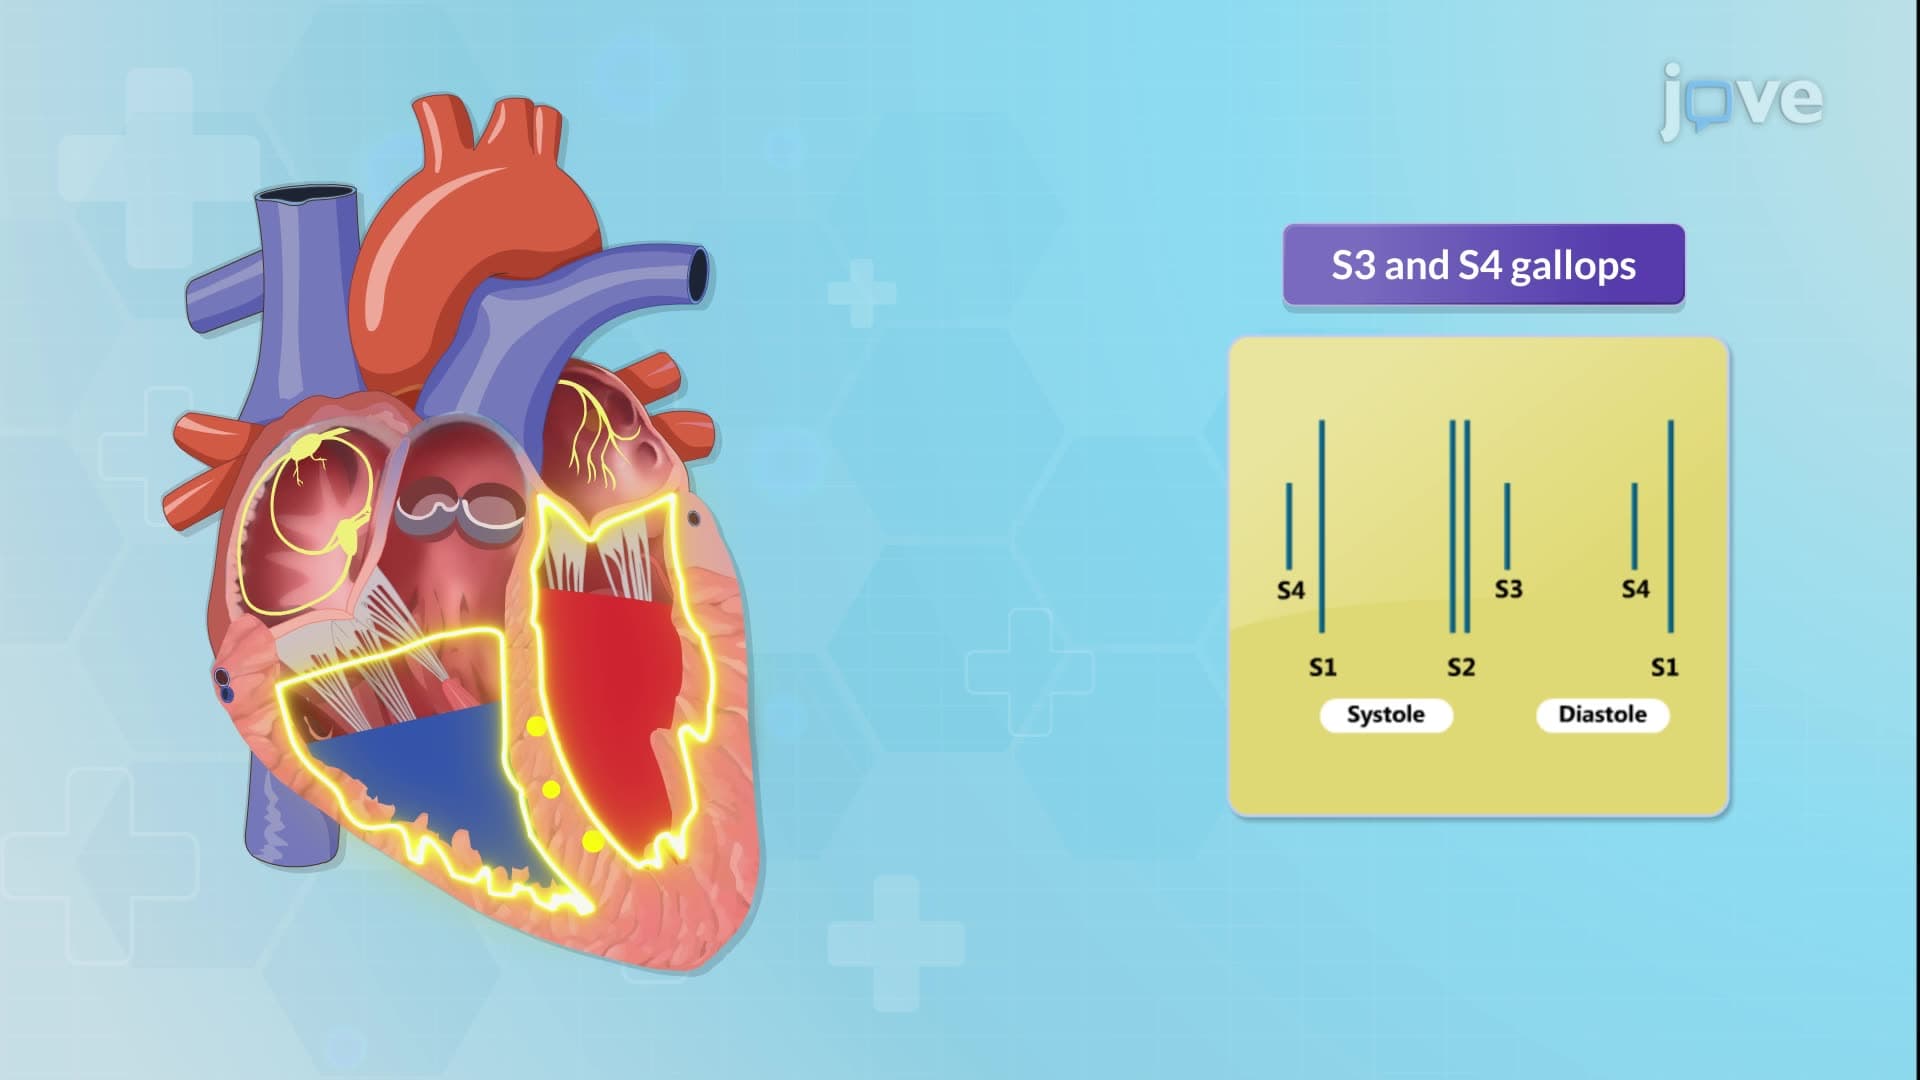
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:30
Pneumonia III: Complications and Assessment
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: