Related Experiment Video
Updated: Jun 22, 2025


5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Spot urinary sodium in CKD patients: correlation with 24h-excretion and evaluation of commonly used prediction
Johanna T Kurzhagen1, Stephanie Titze2,3, Beatrix Büschges-Seraphin4
1Department of Nephrology and Hypertension, University of Erlangen-Nuremberg, Medizinische Klinik 4, Universitätsklinikum Erlangen, Erlangen, Germany. johanna.kurzhagen@uk-erlangen.de.

Background:
Salt intake in CKD patients can affect cardiovascular risk and kidney disease progression. Twenty-four hour (24h) urine collections are often used to investigate salt metabolism but are cumbersome to perform. We assessed urinary sodium (U-Na) concentration in spot urine samples and investigated the correlation with 24h U-Na excretion and concentration in CKD patients under nephrological care. Further, we studied the role of CKD stage and diuretics and evaluated the performance of commonly used formulas for the prediction of 24h U-Na excretion from spot urine samples.
Methods:
One hundred eight patients of the German Chronic Kidney Disease (GCKD) study were included. Each participant collected a 24h urine and two spot urine samples within the same period. The first spot urine sample (AM) was part of the second morning urine. The second urine sample was collected before dinner (PM). Patients were advised to take their medication as usual without changing dietary habits. U-Na concentrations in the two spot urine samples and their average ((AM + PM)/2) were correlated with U-Na concentration and total Na excretion in the 24h urine collections. Correlations were subsequently studied after stratification by CKD stage and diuretic intake. The usefulness of three commonly applied equations to estimate 24h U-Na excretion from spot urine samples (Kawasaki, Tanaka and Intersalt) was determined using Bland-Altman plots, analyses of sensitivity, specificity, as well as positive (PPV) and negative predictive values (NPV).
Results:
Participants (42 women, 66 men) were on average (± SD) 62.2 (± 11.9) years old, with a mean serum creatinine of 1.6 (± 0.5) mg/dl. 95% had arterial hypertension, 37% diabetes mellitus and 55% were on diuretics. The best correlation with 24h U-Na total excretion was found for the PM spot U-Na sample. We also found strong correlations when comparing spot and 24h urine U-Na concentration. Correction of spot U-Na for U-creatinine did not improve strength of correlations. Neither CKD stage, nor intake of diuretics had significant impact on these correlations. All examined formulas revealed a significant mean bias. The lowest mean bias and the strongest correlation between estimated and measured U-Na excretion in 24h were obtained using the Tanaka-formula. Also, application of the Tanaka-formula with PM U-Na provided best sensitivity, specificity, PPV and NPV to estimate U-Na excretion > 4g/d corresponding to a salt consumption > 10g/d.
Conclusion:
U-Na concentration of spot urine samples correlated with 24h U-Na excretion especially when PM spot U-Na was used. However, correlation coefficients were relatively low. Neither CKD stage nor intake of diuretics appeared to have an influence on these correlations. There was a significant bias for all tested formulas with the Tanaka-formula providing the strongest correlation with measured 24h U-Na excretion. In summary, using spot urine samples together with the Tanaka-formula in epidemiological studies appears feasible to determine associations between approximate salt intake and outcomes in CKD patients. However, the usefulness of spot-urine samples to guide and monitor salt consumption in individual patients remains limited.
More Related Videos

Related Concept Videos
 01:11
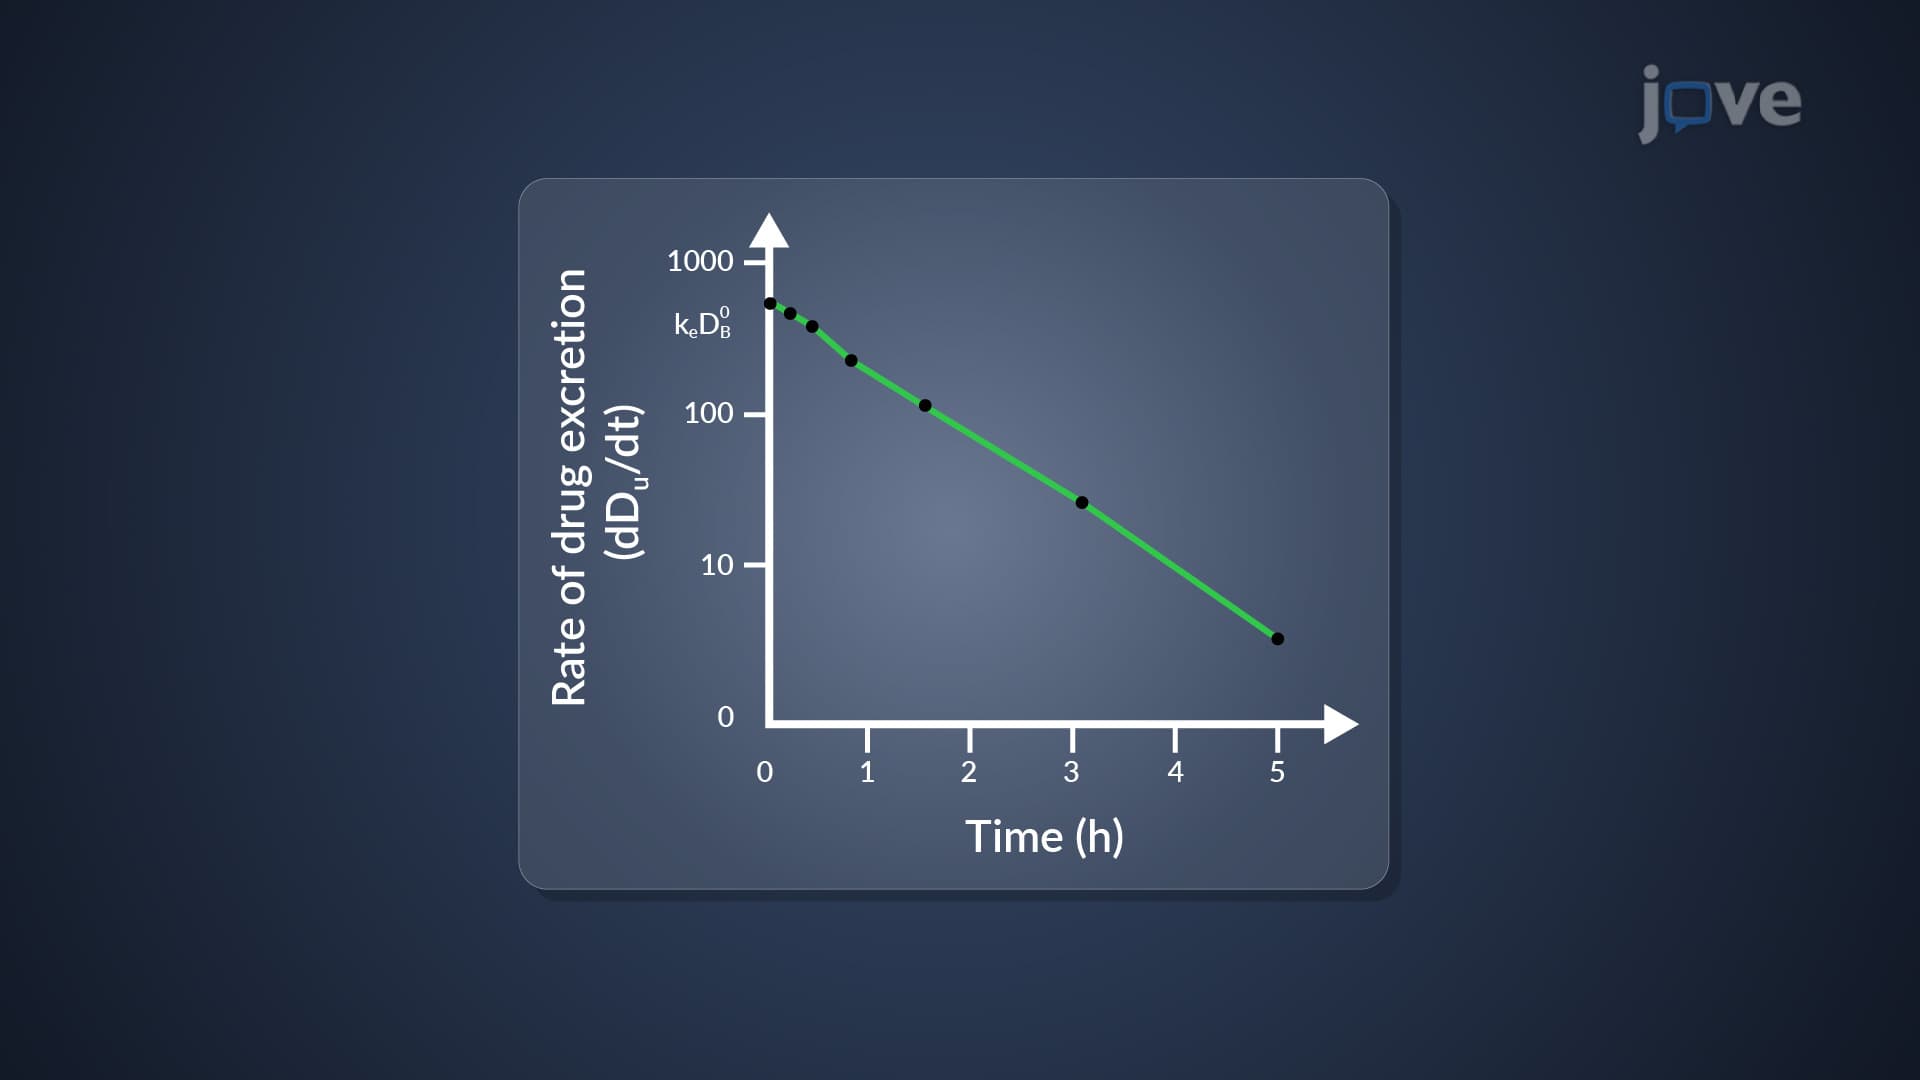
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:07
Determination of Renal Drug Clearance: Graphical and Midpoint Methods
The graphical method involves plotting the rate of drug excretion in urine against the plasma drug concentration. By analyzing the graph, the clearance can be calculated and obtained. Drugs rapidly excreted by the kidneys exhibit a...
 01:26
Regulation of Sodium and Potassium
Sodium Regulation
Sodium ions make up approximately 90% of extracellular cations, with a normal blood plasma concentration of 136–148 mEq/L. A decrease in blood volume and pressure triggers the release of renin from granular cells in the juxtaglomerular complex (JGC), primarily...
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:26
Regulation of Water Output