Related Experiment Video
Updated: Aug 18, 2026
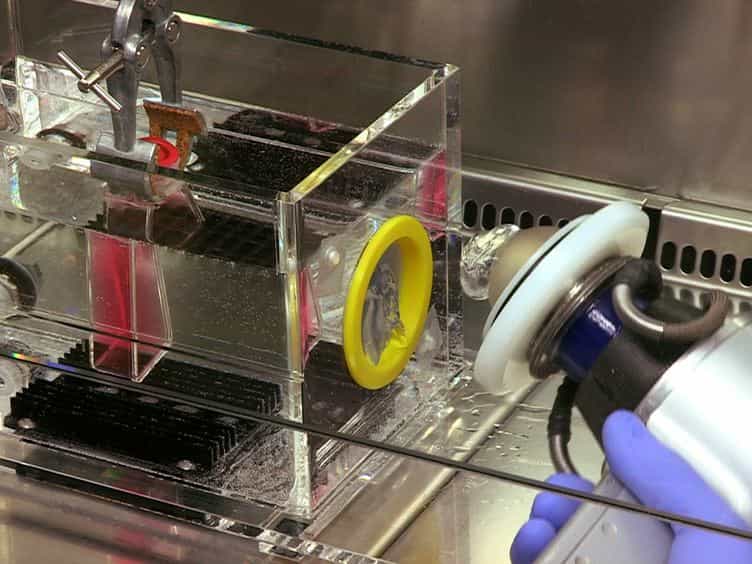

Shock Wave Application to Cell Cultures
Published on: April 8, 2014

Abstract:
In spite of all the scientific and technical advances in recent years, shock that is not rapidly correctable with fluid can have a morbidity rate exceeding 80%. Consequently awareness of such precipitating factors as sepsis and early diagnosis and treatment are essential. Treatment should be rapid and should follow a previously outlined protocol. Such protocols should include correction of the precipitating problem and aggressive resuscitation to assure adequate ventilation and oxygenation of the blood and optimal oxygen delivery to the tissues. Fluid and blood should be given as needed until filling pressures begin to rise rapidly with further fluid infusion. With hemorrhagic shock in previously healthy individuals, a hemoglobin level of 10.0 g/dL is usually adequate. In older, septic, or cardiogenic shock patients, a hemoglobin level of 12.5 to 14.0 may be preferable. If an optimal preload does not increase cardiac output to normal or higher levels, inotropic agents should be used. If shock still persists, one must be sure that the arterial pH is not excessively high or low. Glucocorticoids may then be given in low dose (200 mg hydrocortisone) in case some degree of adrenal insufficiency is present. They can also be given in high doses (equivalent to 150 mg/kg hydrocortisone) early in septic shock primarily to prevent excess complement activation and to preserve membrane integrity. Vasopressors may occasionally be required if there is excessive vasodilation, especially if there is persistent hypotension in the presence of high-grade coronary or cerebral artery stenosis. Vasodilators may be used to try to correct myocardial ischemia (nitroglycerin), excessive preload (nitroglycerin), or excessive afterload (nitroprusside or hydralazine). Combinations of vasodilators and inotropic agents may be required in some patients with high systemic vascular resistance and persistently low cardiac outputs. Mechanical assist with IABP can be of great value in persistent cardiogenic shock. Diuretics may occasionally help prevent renal failure in patients who are persistently oliguric after blood flow and pressure are restored. Heparin is occasionally of value if DIC develops with no concomitant fibrinolysis. Antibiotics are important in septic shock and may also be important if persistent shock has reduced gastrointestinal mucosal integrity so that bacteria and bacterial products can enter the portal system.(ABSTRACT TRUNCATED AT 400 WORDS)


Related Concept Videos
 01:32
The Scientific Method
 02:40
The Scientific Method
 01:22
Case Studies
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:13
Psychology as a Science
The scientific method in psychology involves six critical steps: making observations, formulating hypotheses, conducting tests, analyzing...
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...