Related Experiment Video
Updated: Jun 21, 2025

Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Feasibility and comparative prognosis of segmentectomy versus lobectomy in centrally located small and solid dominant
Norifumi Tsubokawa1, Takahiro Mimae1, Akira Saeki1
1Department of Surgical Oncology, Hiroshima University, Horoshima, Japan.

Objectives:
To determine the feasibility of segmentectomy in patients with central, whole tumor size ≤2 cm and radiologically solid-dominant cN0 non-small cell lung cancer (NSCLC).
Methods:
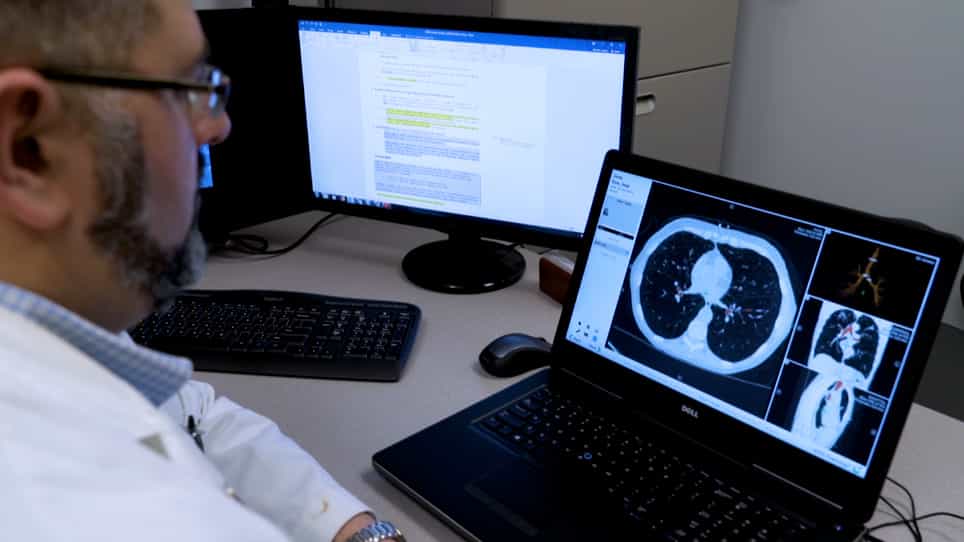
We retrospectively reviewed 1240 patients who underwent lobectomy or segmentectomy for small and radiologically solid-dominant cN0 NSCLC between January 2010 and December 2022. The inclusion criteria encompassed centrally located tumors, defined as tumors located in the inner two-thirds of the pulmonary parenchyma. Propensity score matching was applied to balance the baseline characteristics in the 2 study groups.
Results:
Among the 299 eligible patients, no significant differences in recurrence-free survival (RFS) and overall survival (OS) were observed between the segmentectomy (n = 121) and lobectomy (n = 178) groups (P = .794 and .577, respectively). After propensity score matching, no significant differences in hilar and mediastinal lymph node upstaging were found among the 93 matched patients (P = 1.00), and locoregional recurrence was comparable in the segmentectomy (n = 4) and lobectomy (n = 4) groups. RFS and OS did not differ significantly between the 2 groups (P = .700 and .870, respectively). Propensity score-adjusted multivariable Cox analysis for RFS and OS indicated that segmentectomy was not an independent prognostic factor (RFS: hazard ratio [HR], 0.89; 95% confidence interval [CI], 0.43-1.85; P = .755; OS: HR, 1.09; 95% CI, 0.38-3.14; P = .860).
Conclusions:
Segmentectomy may be a viable treatment option, with local control and prognosis comparable to that of lobectomy in appropriately selected patients with central, small (≤2 cm), and radiologically solid-dominant NSCLC.