Related Experiment Video
Updated: Jun 21, 2025
An Intramedullary Locking Nail for Standardized Fixation of Femur Osteotomies to Analyze Normal and Defective Bone Healing in Mice
Published on: November 13, 2016
Intramedullary Threaded Nail Fixation of Distal Ulnar Fractures: The Surgical Technique and Case Series
Alexander D Jeffs1, Andrew D Allen1, Bradley J Lauck1
1Department of Orthopaedics, Chapel Hill School of Medicine, University of North Carolina, Chapel Hill, USA.

Background:
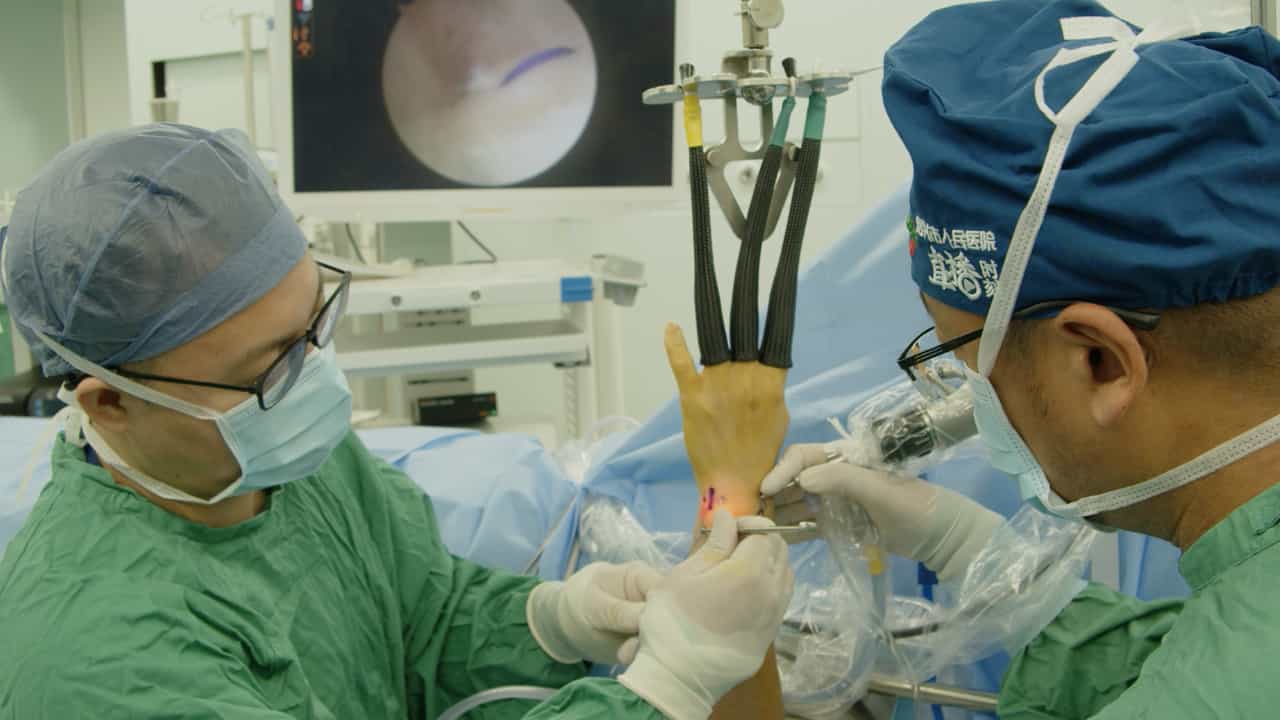
To describe the surgical technique of non-compressive intramedullary threaded nail (IMTN) fixation of distal ulnar neck fractures and present the clinical and radiographic outcomes of four patients treated with this novel technique.
Methods:
At a single Level 1 Trauma Center, a retrospective review was conducted for patients with distal ulnar neck fractures treated with retrograde IMTN between 2022 and 2024. Exclusion criteria included inadequate follow-up. A single surgeon performed all procedures using percutaneous retrograde IMTN fixation through the central disc of the triangular fibrocartilage complex (TFCC). Patients initiated a range of motion (ROM) protocol two weeks post-operatively. Post-operative radiographic images were used to calculate the ratio of IMTN diameter to the distal ulnar medullary isthmus diameter proximal to the fracture site. Radiographic changes in displacement, angulation, and ulnar variance were calculated between the first and last follow-up radiographs. Functional outcomes including grip strength and ROM were collected.
Results:
Four patients with distal ulnar neck fractures were treated with retrograde IMTN between 2022 and 2024. They were followed for a minimum of three months post-operatively. All were female with an average age of 65 years. All distal ulna fractures were associated with operatively treated intraarticular distal radius fractures. All patients were treated with 75 mm length and 4.5 mm diameter IMTNs. IMTN-to-Isthmus ratio was greater than 60% in all cases. Average radiographic displacement and angulation were unchanged at the final follow-up. The average ulnar variance increased by 1.2 mm. At the final follow-up, there were no post-operative complications. No cases demonstrated ulnar-sided wrist pain, nonunion, or required revision surgery.
Conclusions:
Retrograde IMTN fixation is a novel surgical technique for the treatment of distal ulnar neck fractures. We found limited but promising post-operative radiographic and functional outcomes in our patients without reported ulnar-sided wrist pain, nonunion, or need for hardware removal.