Related Experiment Video
Updated: Aug 8, 2026
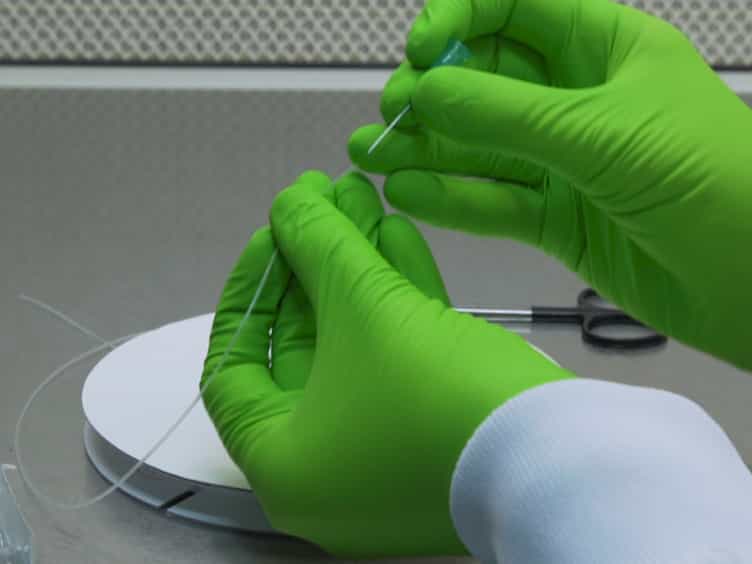

Bronchoalveolar Lavage of Murine Lungs to Analyze Inflammatory Cell Infiltration
Published on: May 4, 2017
Asbestosis. Bronchoalveolar lavage fluid proteins and their relationship to pulmonary epithelial permeability

Abstract:
We measured levels of albumin and immunoglobulins in serum and bronchoalveolar lavage (BAL) fluid in 28 men with asbestosis and 11 control subjects. The half-time clearance of inhaled diethylene triamine pentacetate labelled with technetium-99m (99mTc-DTPA) from the lungs (t1/2LB) was measured in 26 patients with asbestosis and in 31 normal nonsmoking controls. In those individuals in whom immunoglobulins were detected in BAL fluid, the mean IgG:albumin ratio in BAL fluid was 0.30 (range, 0.11 to 0.97), significantly less than the ratio of 0.43 (0.28 to 0.66) in control subjects (p less than 0.05). There was no significant difference in IgA:albumin ratios between patients and control subjects. The mean BAL:serum albumin ratio in patients with asbestosis was 2.3 X 10(-3) (range, 0.2 to 9.5 X 10(-3), significantly greater than the ratio of 1.2 X 10(-3) (0.5 to 2.0 X 10(-3] in control subjects (p less than 0.02). The t1/2LB was significantly shorter in both smokers and nonsmokers with asbestosis, compared with 31 normal nonsmoking controls, but there were no relationships between t1/2LB and BAL:serum albumin ratio or any other BAL protein levels in either smokers or nonsmokers with asbestosis.
More Related Videos


Related Concept Videos
 01:05
Breathing
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:10
Atelectasis II: Pathophysiology
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:18
Pulmonary Edema II: Pathophysiology