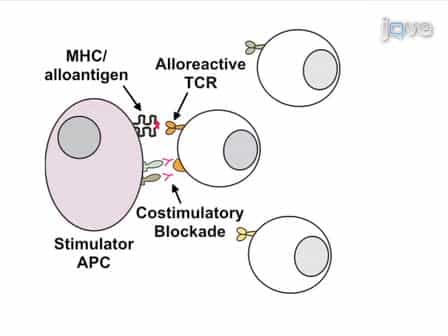
Abatacept for acute graft-versus-host disease prophylaxis after unrelated donor hematopoietic cell transplantation
Leslie S Kean1,2,3, Linda J Burns4, Tzuyung D Kou5
1Division of Hematology/Oncology, Boston Children's Hospital, Boston, MA.

Abatacept plus calcineurin inhibitors/methotrexate (CNI/MTX) is the first US Food and Drug Administration (FDA)-approved regimen for acute graft-versus-host disease (aGVHD) prophylaxis during unrelated-donor hematopoietic cell transplantation (URD-HCT). Using Center for International Blood and Marrow Transplant Research data, we investigated its impact in patients receiving 7/8 HLA-mismatched unrelated donor (MMUD) or 8/8 HLA-matched unrelated donor (MUD) URD-HCT between 2011 and 2018. Primary outcomes included day-180, 1-year, and 2-year overall survival (OS) and relapse-free survival (RFS) for abatacept + CNI/MTX vs CNI/MTX, CNI/MTX + antithymocyte globulin (ATG), and posttransplant cyclophosphamide-based prophylaxis (PT-Cy). For 7/8 MMUDs, day-180 OS (primary end point supporting FDA approval) was significantly higher for abatacept + CNI/MTX vs CNI/MTX (98% vs 75%; P = .0028). Two-year RFS was significantly higher for abatacept + CNI/MTX vs CNI/MTX (74% vs 49%; P = .0098) and CNI/MTX + ATG (77% vs 35%; P = .0002), and similar vs PT-Cy (72% vs 56%; P = .1058). For 8/8 MUDs, 2-year RFS for abatacept + CNI/MTX was numerically higher vs CNI/MTX (63% vs 52%; P = .1497), with an improved hazard ratio (HR) of 0.46 (0.25-0.86), and vs CNI/MTX + ATG (66% vs 55%; P = .1193; HR, 0.39 [0.21-0.73]), and was similar vs PT-Cy (68% vs 57%; P = .2356; HR, 0.54 [0.26-1.11]). For 7/8 MMUD and 8/8 MUD recipients, abatacept + CNI/MTX prophylaxis improved survival outcomes vs CNI/MTX and CNI/MTX + ATG; outcomes were similar to PT-Cy-based regimens. Abatacept + CNI/MTX may facilitate unrelated donor pool expansion for HCT.
Abatacept plus calcineurin inhibitors/methotrexate (CNI/MTX) is the first US Food and Drug Administration (FDA)-approved regimen for acute graft-versus-host disease (aGVHD) prophylaxis during unrelated-donor hematopoietic cell transplantation (URD-HCT). Using Center for International Blood and Marrow Transplant Research data, we investigated its impact in patients receiving 7/8 HLA-mismatched unrelated donor (MMUD) or 8/8 HLA-matched unrelated donor (MUD) URD-HCT between 2011 and 2018. Primary outcomes included day-180, 1-year, and 2-year overall survival (OS) and relapse-free survival (RFS) for abatacept + CNI/MTX vs CNI/MTX, CNI/MTX + antithymocyte globulin (ATG), and posttransplant cyclophosphamide-based prophylaxis (PT-Cy). For 7/8 MMUDs, day-180 OS (primary end point supporting FDA approval) was significantly higher for abatacept + CNI/MTX vs CNI/MTX (98% vs 75%; P = .0028). Two-year RFS was significantly higher for abatacept + CNI/MTX vs CNI/MTX (74% vs 49%; P = .0098) and CNI/MTX + ATG (77% vs 35%; P = .0002), and similar vs PT-Cy (72% vs 56%; P = .1058). For 8/8 MUDs, 2-year RFS for abatacept + CNI/MTX was numerically higher vs CNI/MTX (63% vs 52%; P = .1497), with an improved hazard ratio (HR) of 0.46 (0.25-0.86), and vs CNI/MTX + ATG (66% vs 55%; P = .1193; HR, 0.39 [0.21-0.73]), and was similar vs PT-Cy (68% vs 57%; P = .2356; HR, 0.54 [0.26-1.11]). For 7/8 MMUD and 8/8 MUD recipients, abatacept + CNI/MTX prophylaxis improved survival outcomes vs CNI/MTX and CNI/MTX + ATG; outcomes were similar to PT-Cy-based regimens. Abatacept + CNI/MTX may facilitate unrelated donor pool expansion for HCT.

Related Concept Videos
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:40
Cell-mediated Immune Responses
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...