Related Experiment Video
Updated: Jun 20, 2025
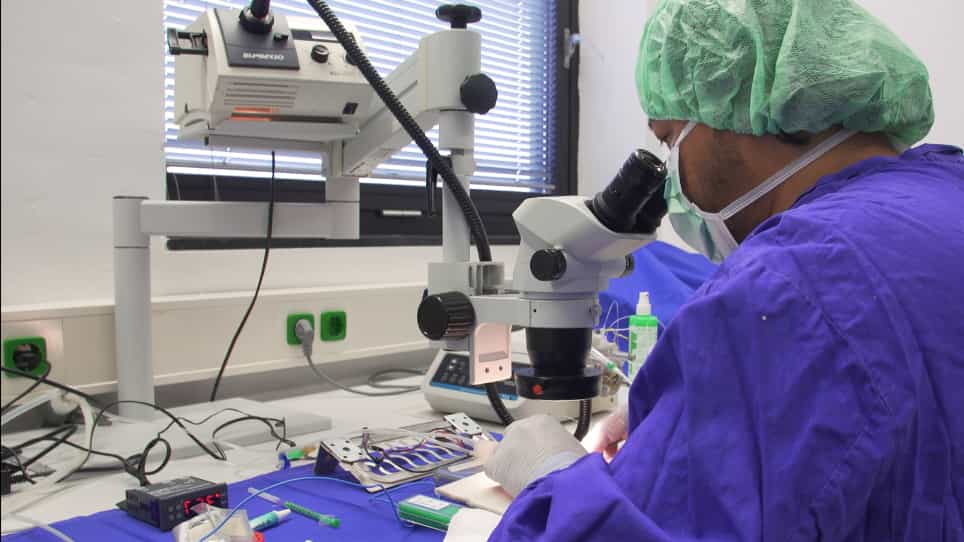

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Why do children not survive extracorporeal membrane oxygenation?
Georgina K Alexander1, Siva P Namachivayam1,2,3,4, Roberto Chiletti1,2,4
1Paediatric Intensive Care Unit, The Royal Children's Hospital, Melbourne, Victoria, Australia.

Insights
Extracorporeal membrane oxygenation (ECMO) is a life-saving treatment for critically ill children. While overall survival is 67%, understanding reasons for death, especially in those with comorbidities, is crucial for optimizing care.
Area of Science:
- Pediatric Critical Care Medicine
- Cardiopulmonary Support
- Medical Technology Assessment
Background:
- Extracorporeal membrane oxygenation (ECMO) use is rising in critically ill children, including those with complex comorbidities.
- Understanding the specific reasons why children do not survive ECMO is essential for improving outcomes.
- This study addresses a gap in knowledge regarding mortality in pediatric ECMO patients.
Purpose of the Study:
- To describe the characteristics and causes of death in children receiving ECMO.
- To compare mortality rates in pediatric ECMO patients with high-risk comorbidities.
- To evaluate trends in ECMO survival over a ten-year period.
Main Methods:
- Retrospective analysis of 428 children (<18 years) who received ECMO between 2011 and 2020.
- Categorization of outcomes: death within 48 hours, death after 48 hours, and hospital discharge survival.
- Classification of reasons for ECMO withdrawal in non-survivors, including irrecoverable original condition and poor neurological prognosis.
Main Results:
- Overall hospital survival to discharge was 67%, with no significant change over the decade.
- The majority of deaths occurred after ECMO withdrawal due to irrecoverable disease (39%) or poor prognosis (32% neurological, 18% complex conditions).
- Children with high-risk comorbidities like genetic syndromes (58% mortality) and malignancy (0% survival) had significantly lower survival rates.
Conclusions:
- In pediatric ECMO, death is often associated with elective withdrawal of support due to irrecoverable disease or poor prognosis.
- Despite challenges, children with high-risk comorbidities demonstrate a potential for survival with ECMO therapy.
- This study supports ECMO as a viable therapeutic option for select critically ill children, even those with complex conditions.
Background:
Extracorporeal membrane oxygenation (ECMO) is used in critically ill children with cardiac and/or respiratory failure. Use is increasing in children with high-risk comorbidities. Reasons children do not survive ECMO are poorly described.
Aims:
Describe characteristics and cause of death, compare mortality in children with high-risk comorbidities, evaluate mortality trends over a decade.
Method:
All children <18 years old who received ECMO at this institution from 1 January 2011 to 31 December 2020 were described and categorised by outcome: died on or <48 h post-ECMO, died ≥48 h post-ECMO, survived to hospital discharge. Children who did not survive ECMO (DNSE) were categorised to: ECMO withdrawal for irrecoverable original condition, withdrawal for poor prognosis neurological condition, brain death, withdrawal for poor prognosis with multiple complex conditions, and unsupportable. Poison regression was used to analyse survival trends.
Results:
Four hundred twenty-eight children received ECMO, 19% DNSE, 14% died ≥48 h post-ECMO and 67% survived. ECMO was electively withdrawn for irrecoverable original condition (39%), poor prognosis for neurological condition (32%) or multiple complex conditions (18%). One hundred twenty-two children had ≥1 high-risk comorbidity. Children with genetic syndromes (58%), risk-adjusted congenital heart surgery score-1 ≥4 (53%), primary immunodeficiency (50%) had lower hospital survival. No children with malignancy/bone marrow transplant survived to hospital discharge. Overall hospital survival was 67%, with no significant change during the study period (P-trend = 0.99).
Conclusion:
Children who DNSE have therapy electively withdrawn for irrecoverable disease or poor prognosis. Children with high-risk comorbidities have a reasonable chance of survival. This study informs clinicians ECMO may be a therapeutic option.


Related Concept Videos
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
Factors Affecting Respiration
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...