Related Experiment Video
Updated: Jun 20, 2025


Dry Powder and Nebulized Aerosol Inhalation of Pharmaceuticals Delivered to Mice Using a Nose-only Exposure System
Published on: April 6, 2017
Getting the dose right using physiologically-based pharmacokinetic modeling: dexamethasone to prevent post-extubation
Joyce E M van der Heijden1, Marika de Hoop-Sommen1, Noa Hoevenaars1
1Division of Pharmacology and Toxicology, Department of Pharmacy, Radboud University Medical Center, Nijmegen, Netherlands.

Introduction:
Critically ill patients show large variability in drug disposition due to e.g., age, size, disease and treatment modalities. Physiologically-based pharmacokinetic (PBPK) models can be used to design individualized dosing regimens taking this into account. Dexamethasone, prescribed for the prevention post-extubation stridor (PES), is metabolized by the drug metabolizing enzyme CYP3A. As CYP3A4 undergoes major changes during childhood, we aimed to develop age-appropriate dosing recommendations for children of dexamethasone for PES, as proof of concept for PBPK modeling to individualize dosing for critically ill patients.
Methods:
All simulations were conducted in Simcyp™ v21 (a population-based PBPK modeling platform), using an available dexamethasone compound model and pediatric population model in which CYP3A4 ontogeny is incorporated. Published pharmacokinetic (PK) data was used for model verification. Evidence for the dose to prevent post-extubation stridor was strongest for 2-6 year old children, hence simulated drug concentrations resulting from this dose from this age group were targeted when simulating age-appropriate doses for the whole pediatric age range.
Results:
Dexamethasone plasma concentrations upon single and multiple intravenous administration were predicted adequately across the pediatric age range. Exposure-matched predictions of dexamethasone PK indicated that doses (in mg/kg) for the 2-6 years olds can be applied in 3 month-2 year old children, whereas lower doses are needed in children of other age groups (60% lower for 0-2 weeks, 40% lower for 2-4 weeks, 20% lower for 1-3 months, 20% lower for 6-12 year olds, 40% lower for 12-18 years olds).
Discussion:
We show that PBPK modeling is a valuable tool that can be used to develop model-informed recommendations using dexamethasone to prevent PES in children. Based on exposure matching, the dose of dexamethasone should be reduced compared to commonly used doses, in infants <3 months and children ≥6 years, reflecting age-related variation in drug disposition. PBPK modeling is an promising tool to optimize dosing of critically ill patients.


Related Concept Videos
 01:26
Pharmacokinetic Models: Comparison and Selection Criterion
Physiological models take a detailed approach by considering specific molecular processes. They can predict drug distribution, metabolism, and elimination changes, providing a comprehensive understanding of how drugs interact with the body.
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant,...
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...
 01:09
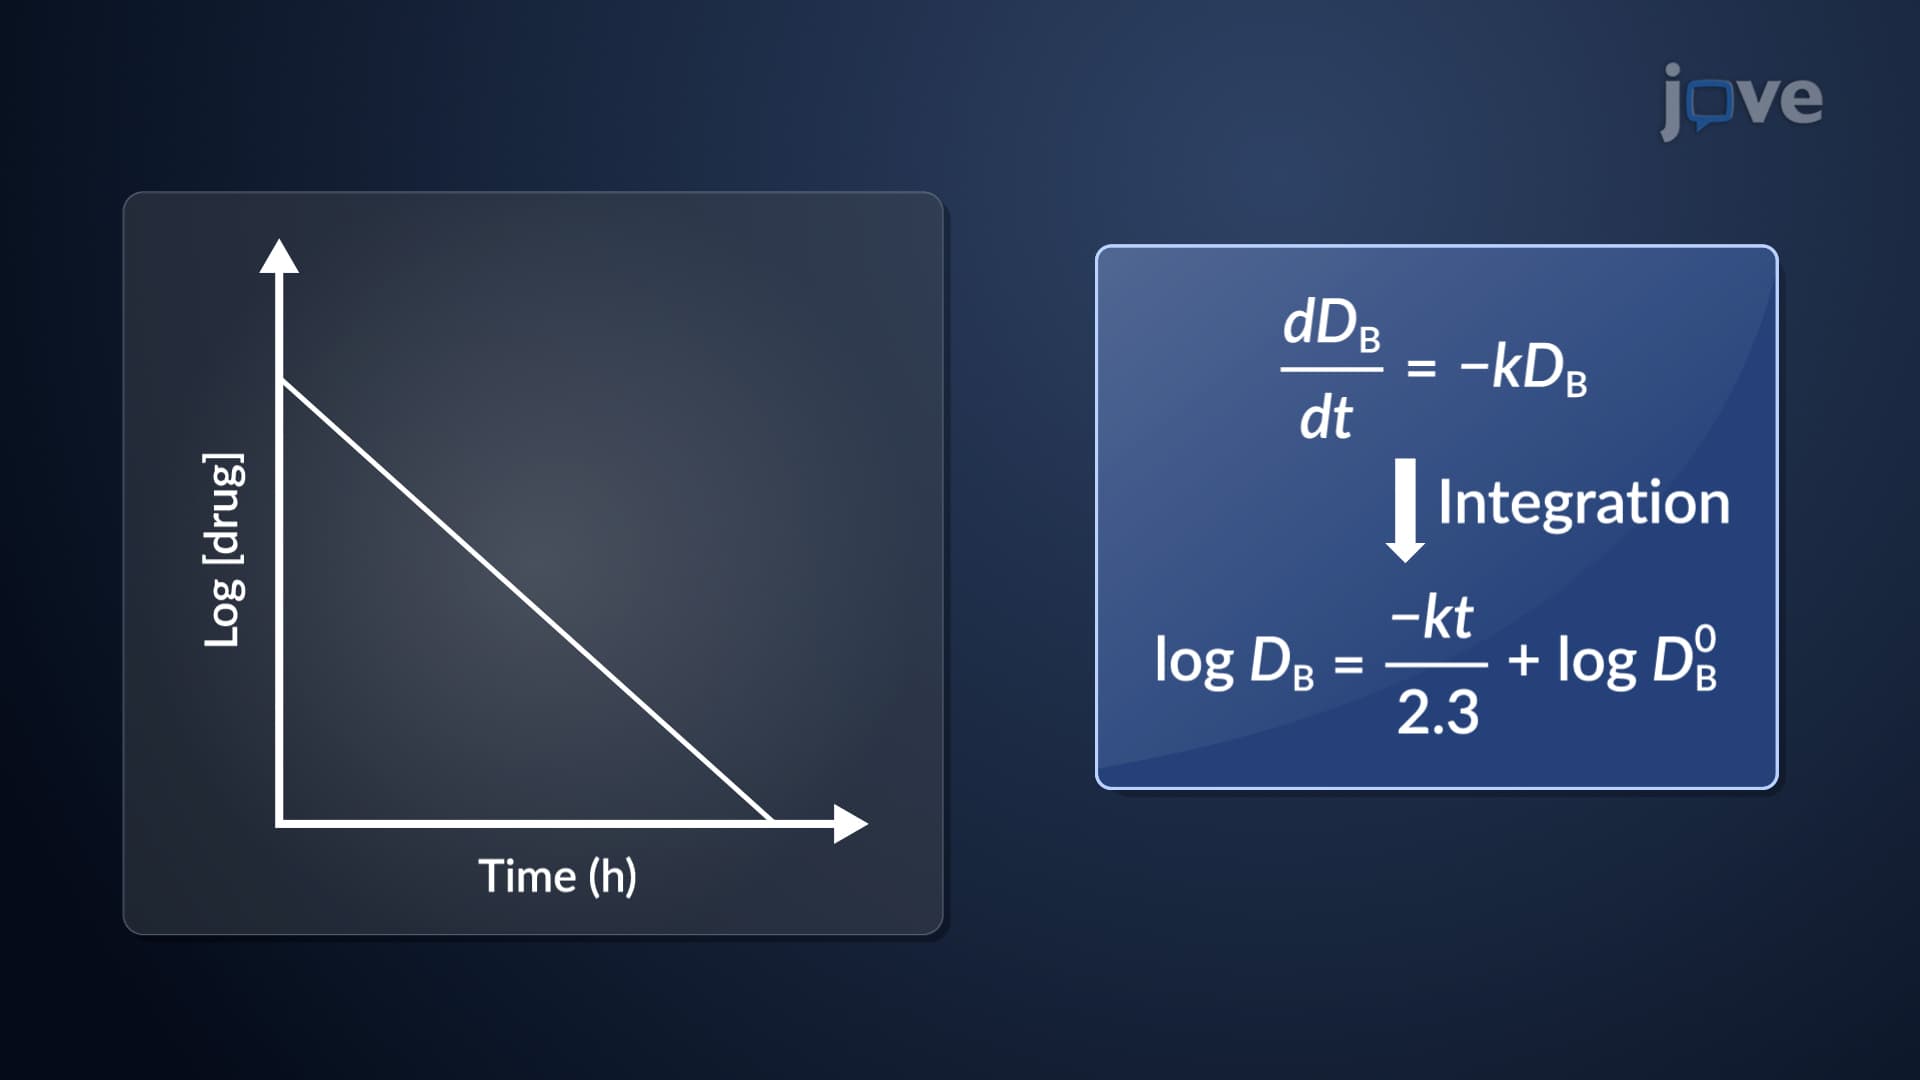
One-Compartment Open Model for IV Bolus Administration: Estimation of Elimination Rate Constant, Half-Life and Volume of Distribution
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal...
 01:06
Model Approaches for Pharmacokinetic Data: Distributed Parameter Models
The distributed parameter models are specifically designed to account for variations and differences in some drug classes. This model is particularly useful for assessing regional concentrations of anticancer or...