Related Experiment Video
Updated: Jun 19, 2025

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
A dive into the physiological responses to maximal apneas, O2 and CO2 tables in apnea novices
Louise Declercq1, Janne Bouten1,2, Matthew Van Dyck1
1Department of Movement and Sports Sciences, Ghent University, Watersportlaan 2, 9000, Ghent, Belgium.

Purpose:
Apnea duration is dependent on three factors: oxygen storage, oxygen consumption, hypoxia and hypercapnia tolerance. While current literature focuses on maximal apneas to improve apnea duration, apnea trained individuals use timed-repeated submaximal apneas, called "O2 and CO2 tables". These tables claim to accommodate the body to cope with hypoxia and hypercapnia, respectively. The aim of this study was twofold. First, to investigate the determinants of maximal apnea duration in apnea novices. Second, to compare physiologic responses to maximal apneas, O2 and CO2 tables.
Methods:
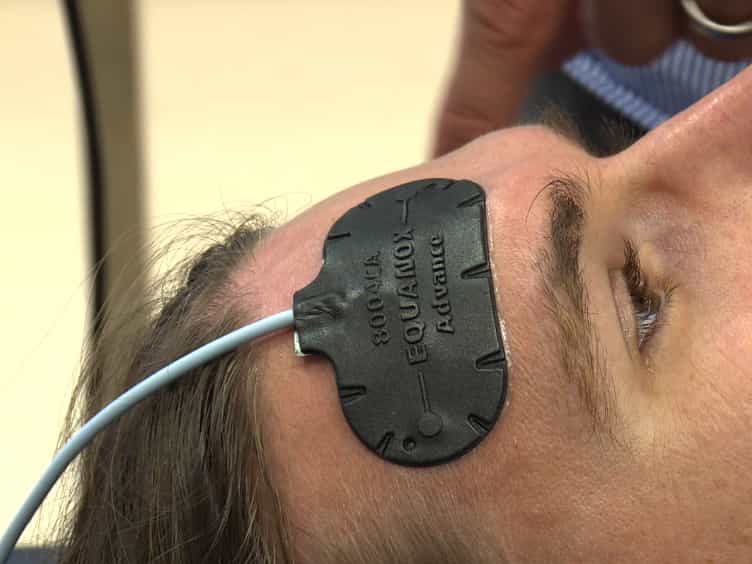
After medical screening, lung function test and hemoglobin mass measurement, twenty-eight apnea novices performed three apnea protocols in random order: maximal apneas, O2 table and CO2 table. During apnea, peripheral oxygen saturation (SpO2), heart rate (HR), muscle (mTOI) and cerebral (cTOI) tissue oxygenation index were measured continuously. End-tidal carbon dioxide (EtCO2) was measured before and after apneas.
Results:
Larger lung volumes, higher resting cTOI and lower resting EtCO2 levels correlated with longer apnea durations. Maximal apneas induced greater decreases in SpO2 (- 16%) and cTOI (- 13%) than O2 (- 8%; - 8%) and CO2 tables (- 6%; - 6%), whereas changes in EtCO2, HR and mTOI did not differ between protocols.
Conclusion:
These results suggest that, in apnea novices, O2 and CO2 tables did not induce a more profound hypoxia and hypercapnia, but a similar reduction in oxygen consumption than maximal apneas. Therefore, apnea novices should mainly focus on maximal apneas to improve hypoxia and hypercapnia tolerance. The use of specific lung training protocols can help to increase oxygen storage capacity.
More Related Videos
 05:45
Experimental Approach to Examine Leptin Signaling in the Carotid Bodies and its Effects on Control of Breathing
Published on: October 25, 2019
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:25
Hyperpnea and Hyperventilation
 01:26
Respiratory Volumes and Capacities I
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: