Related Experiment Video
Updated: Jun 19, 2025

A Modified Two Kidney One Clip Mouse Model of Renin Regulation in Renal Artery Stenosis
Published on: October 26, 2020
Effects of ACE inhibitor/ARB therapy and long COVID on kidney disease: a retrospective cohort study using real-world
Yue Zhang1, Djibril M Ba1, Kathryn Risher1
1Department of Public Health Sciences, Penn State College of Medicine, Hershey, PA, USA.

Background:
The association between angiotensin-converting enzyme inhibitors (ACEIs) or angiotensin II receptor blockers (ARBs) and severe acute respiratory syndrome coronavirus 2 susceptibility, particularly via ACE-2 receptor upregulation in the kidneys, raises concerns about potential kidney disease risks in long coronavirus disease (COVID) patients. This study explores the association of ACEI/ARB therapy on acute kidney injury (AKI), chronic kidney disease (CKD) and all-cause mortality in patients with and without long COVID.
Methods:
A retrospective cohort study using TriNetX datasets was conducted, with diagnoses of long COVID via International Classification of Diseases, Tenth Revision (ICD-10) codes and prescription for ACEI/ARB as the classification of four cohorts: long COVID ACEI/ARB users (LCAUs), long COVID ACEI/ARB non-users (LCANs), non-long COVID ACEI/ARB users (NLCAUs) and non-long COVID ACEI/ARB non-users (NLCANs). Multivariable stratified Cox proportional hazards regression models assessed the adjusted hazard ratios (aHRs) across groups. Additional analyses were conducted, including time-dependent exposure analysis and comparison with an active comparator, calcium channel blockers.
Results:
Our study included 18 168 long COVID and 181 680 propensity score-matched non-long COVID patients from October 2021 to October 2023. ACEI/ARB use did not significantly affect the risk of AKI or CKD when comparing LCAUs with LCANs and NLCAUs with NLCANs. However, a protective effect against all-cause mortality was observed {aHR 0.79 [95% confidence interval (CI) 0.65-0.93]} in the NLCAU group compared with the NLCAN group. Conversely, long COVID was associated with increased risks of CKD [aHR 1.49 (95% CI 1.03-2.14)] and all-cause mortality [aHR 1.49 (95% CI 1.00-2.23)] when comparing LCANs with NLCANs. The additional analyses support the primary findings.
Conclusions:
ACEI/ARB treatment does not increase the incidence of CKD or AKI, regardless of long COVID status. However, long COVID itself is associated with increasing risks of kidney diseases and all-cause mortality.
Insights
Angiotensin-converting enzyme inhibitors (ACEIs) or angiotensin II receptor blockers (ARBs) do not increase kidney disease risk in long COVID patients. However, long COVID itself is linked to higher risks of chronic kidney disease and mortality.
Area of Science:
- Nephrology
- Infectious Diseases
- Pharmacology
Background:
- Concerns exist regarding ACEI/ARB therapy and kidney disease risk in long COVID patients due to potential ACE-2 receptor upregulation.
- This study investigates the impact of ACEI/ARB therapy on kidney outcomes and mortality in patients with and without long COVID.
Purpose of the Study:
- To evaluate the association between ACEI/ARB use and the risk of acute kidney injury (AKI) and chronic kidney disease (CKD) in long COVID patients.
- To assess the impact of ACEI/ARB therapy on all-cause mortality in patients with and without long COVID.
Main Methods:
- Retrospective cohort study using TriNetX datasets with ICD-10 codes for long COVID diagnosis.
- Four cohorts were established: long COVID ACEI/ARB users (LCAUs), long COVID non-users (LCANs), non-long COVID ACEI/ARB users (NLCAUs), and non-long COVID non-users (NLCANs).
- Multivariable Cox proportional hazards regression models were used to assess adjusted hazard ratios (aHRs).
Main Results:
- ACEI/ARB use did not significantly alter the risk of AKI or CKD in either long COVID or non-long COVID groups.
- A protective effect against all-cause mortality was observed in NLCAUs compared to NLCANs (aHR 0.79).
- Long COVID was associated with increased risks of CKD (aHR 1.49) and all-cause mortality (aHR 1.49) when comparing LCANs with NLCANs.
Conclusions:
- ACEI/ARB treatment does not elevate the incidence of CKD or AKI, irrespective of long COVID status.
- Long COVID independently increases the risk of kidney diseases and all-cause mortality.
- The findings suggest that ACEI/ARB therapy is safe concerning kidney outcomes in long COVID patients.


Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:15
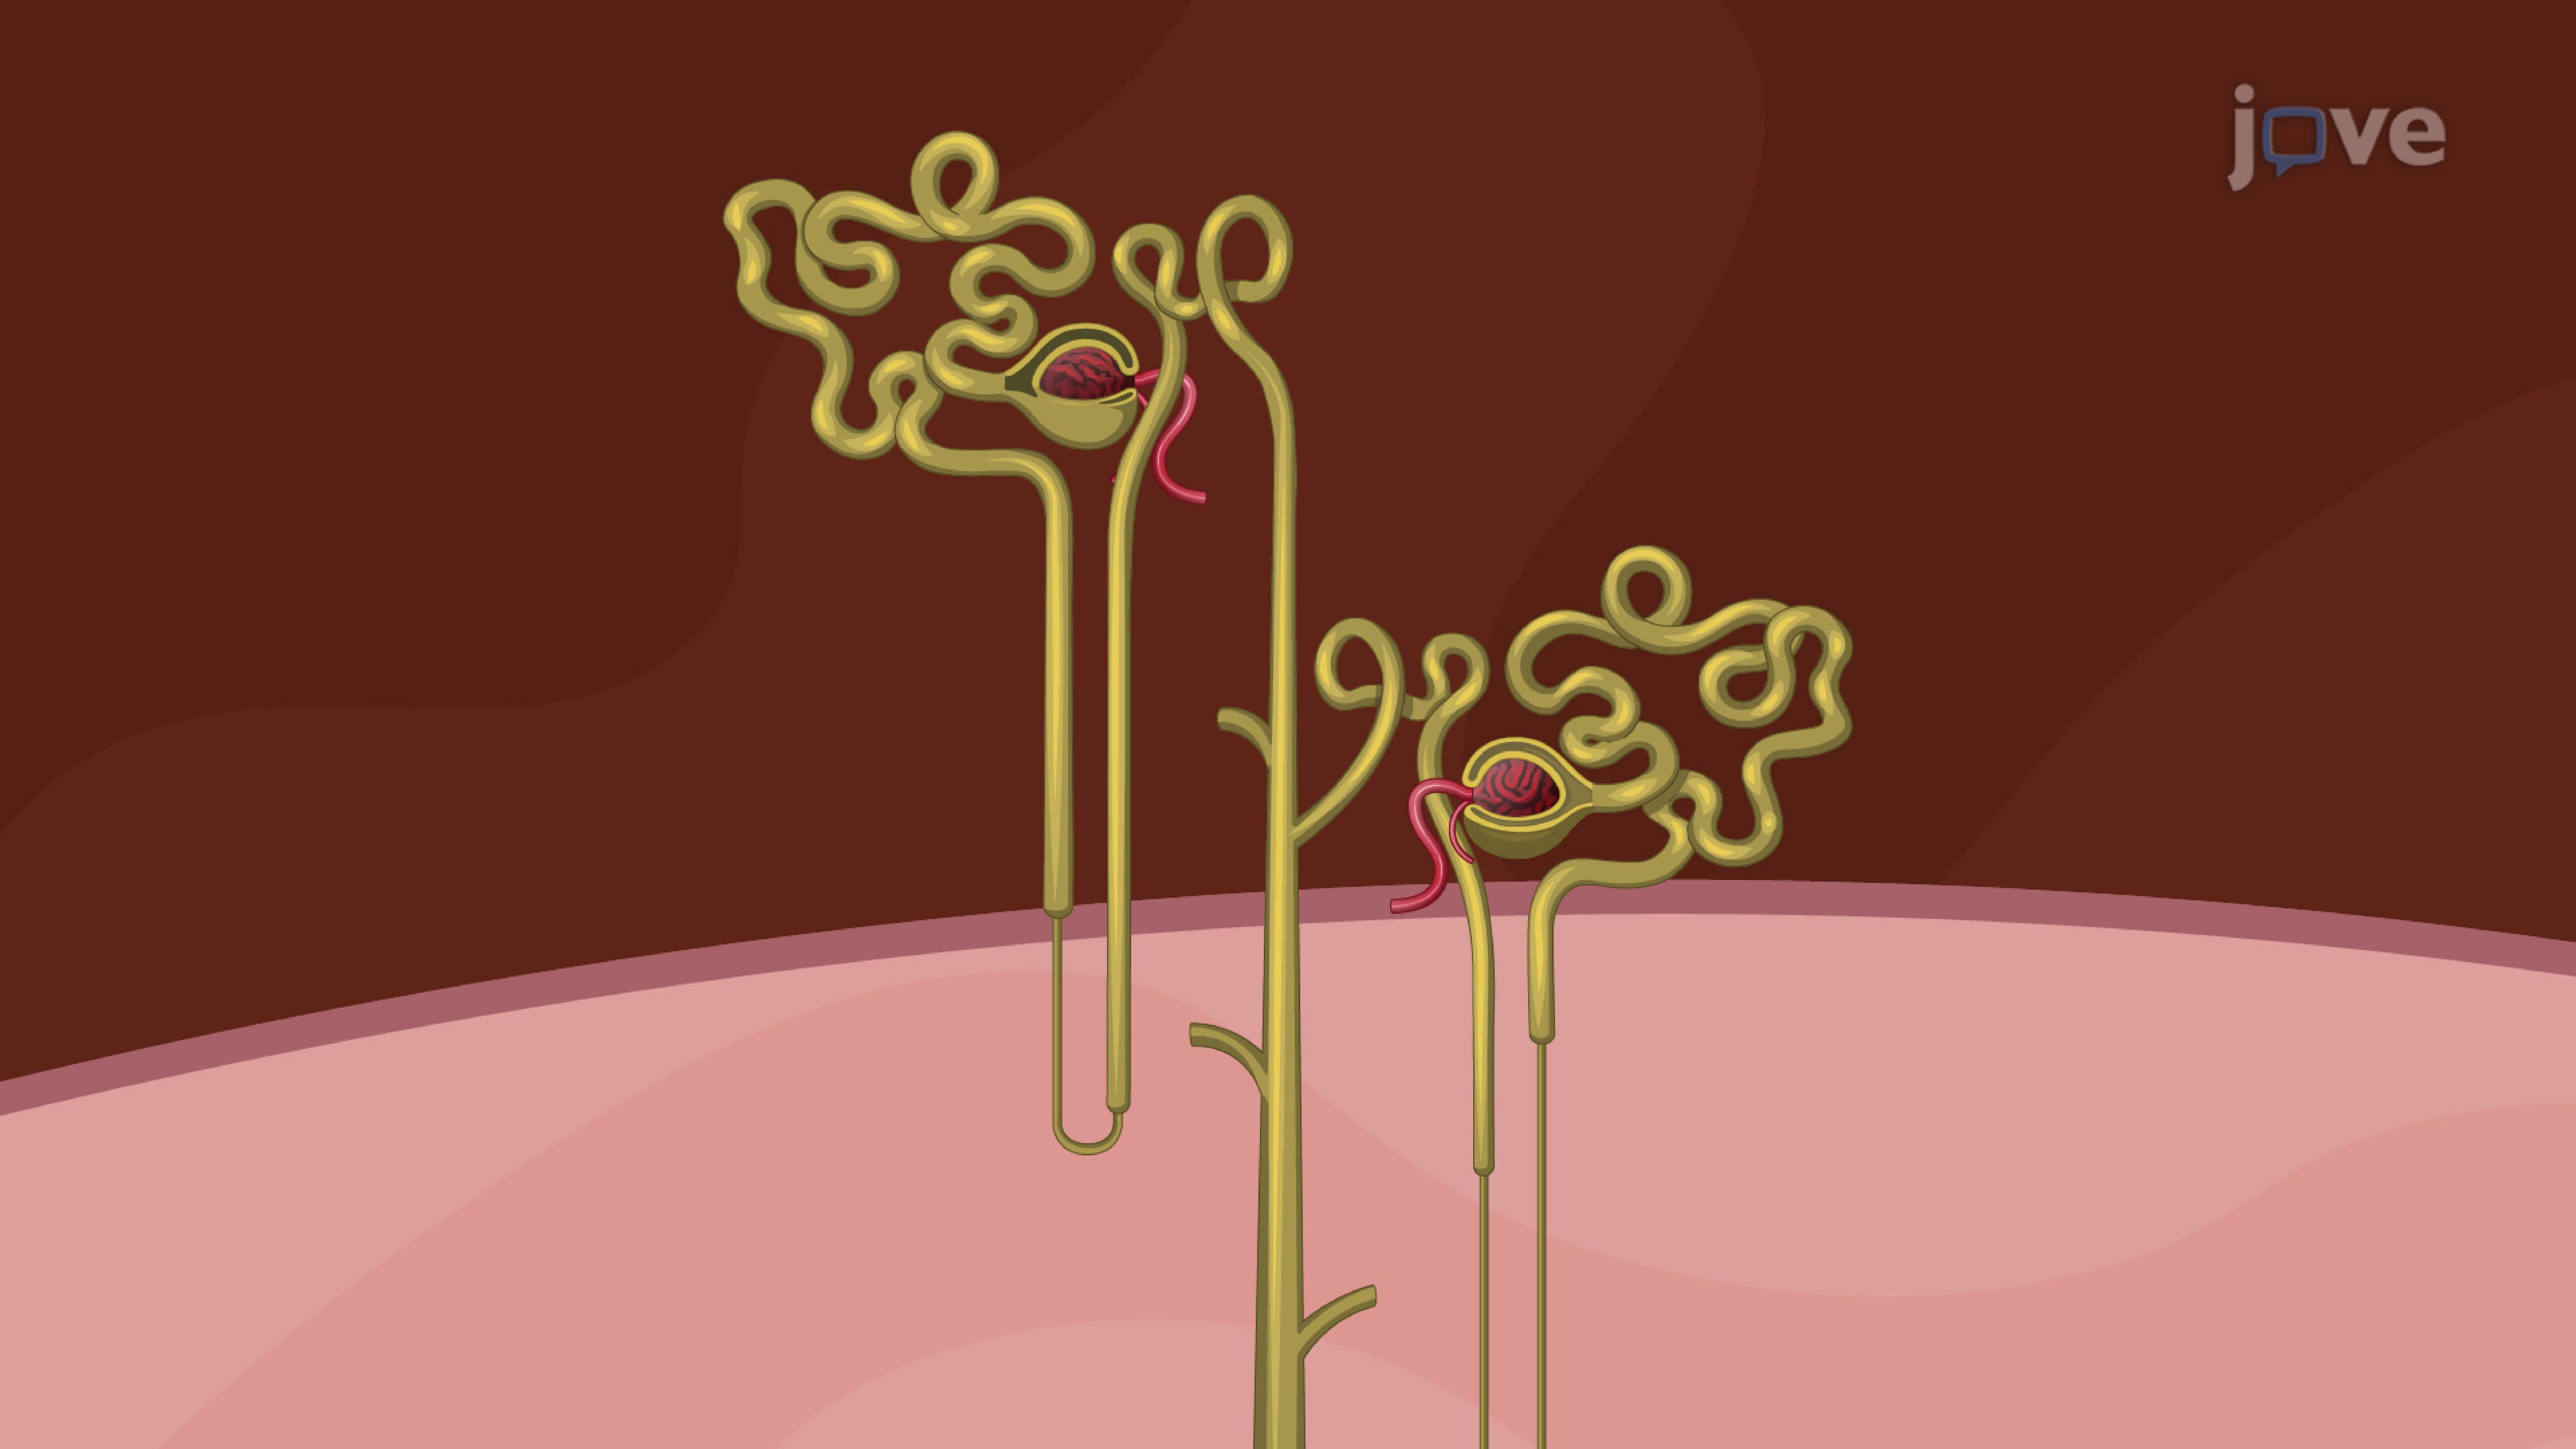
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
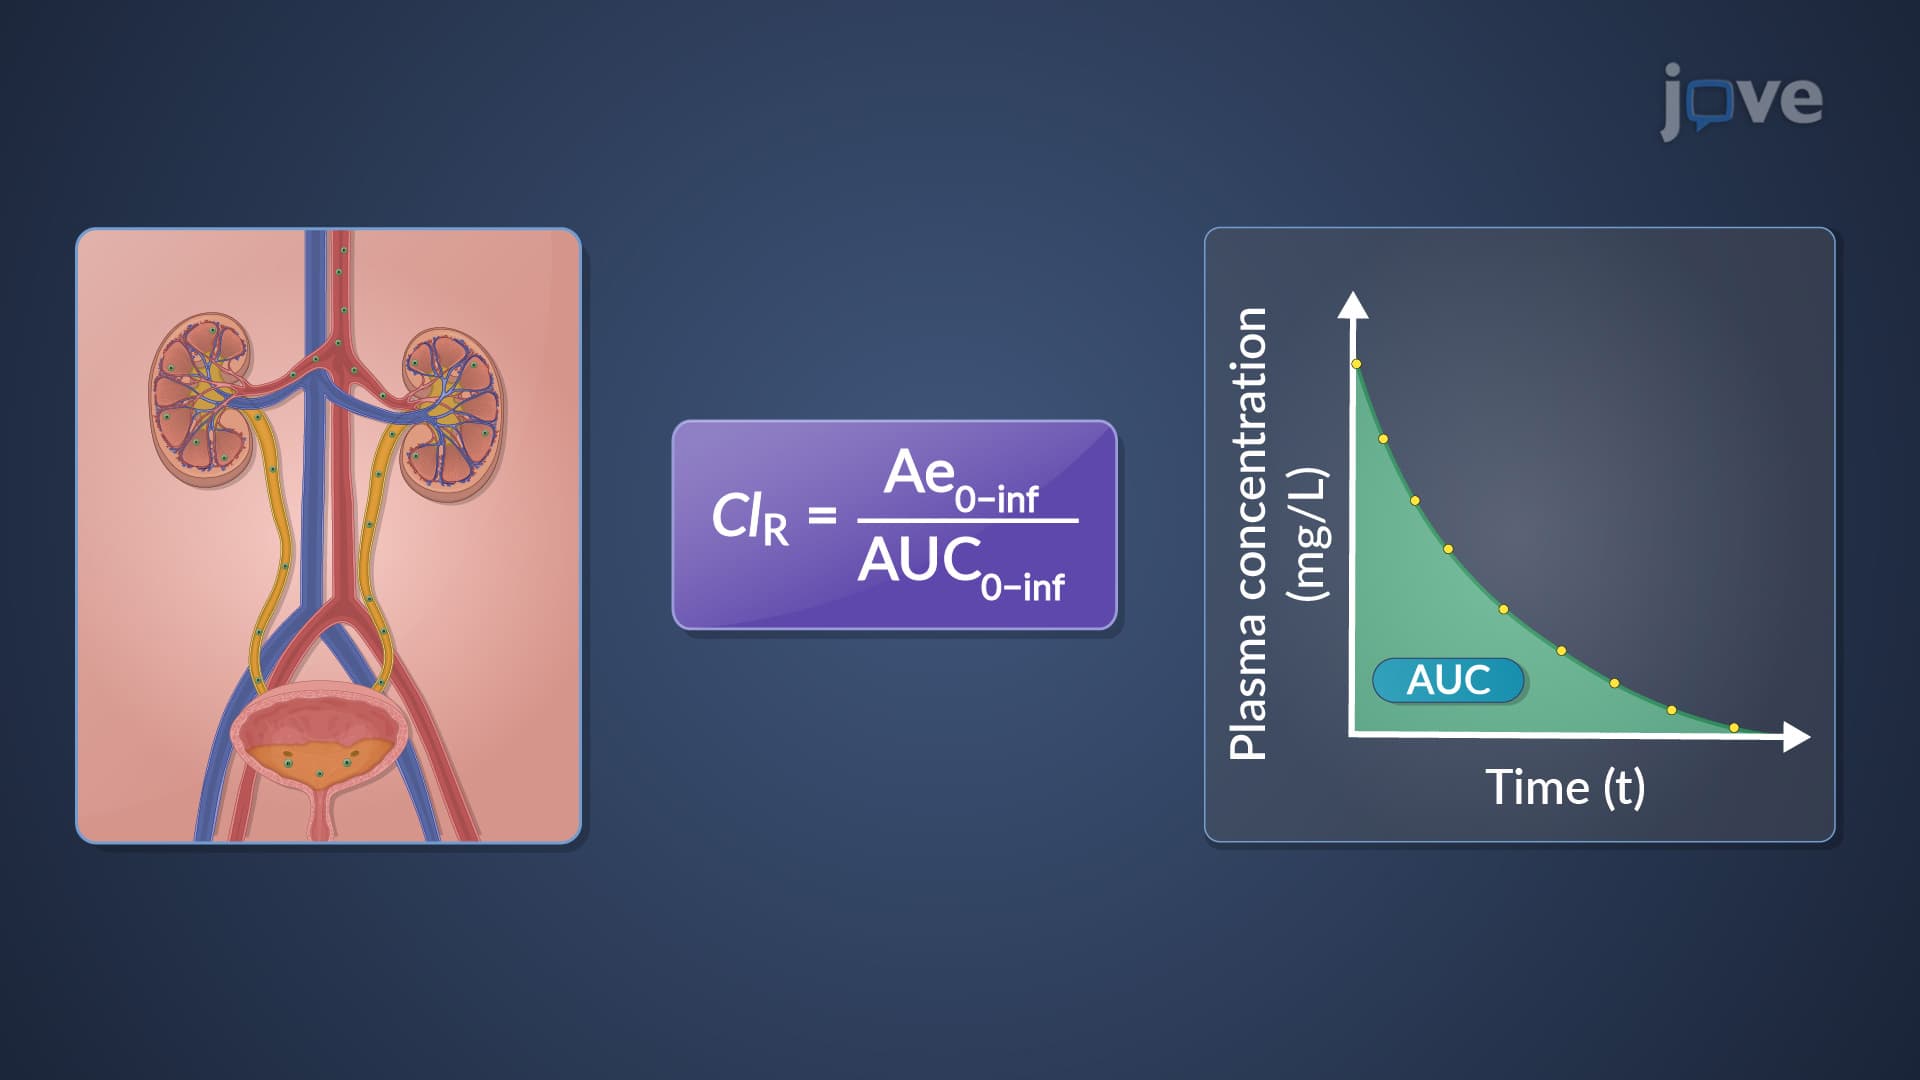
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...