Related Experiment Video
Updated: Jun 18, 2025

Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Blood pressure control in diabetic kidney disease: a post-hoc analysis of the FANTASTIC trial
Cheol Ho Park1, Soon Jun Hong2, Sung Gyun Kim3
1Department of Internal Medicine, Institute of Kidney Disease Research, Yonsei University College of Medicine, Seoul, Republic of Korea.

Insights
Strictly controlling blood pressure (BP) below 130 mmHg in diabetic kidney disease (DKD) patients did not lower cardiovascular/renal events. However, achieving a systolic BP of 130-139 mmHg was linked to reduced event risk.
Area of Science:
- Nephrology
- Cardiology
- Endocrinology
Background:
- The optimal blood pressure (BP) target for diabetic kidney disease (DKD) remains uncertain.
- This study evaluated the impact of strict BP control versus standard control on clinical outcomes in DKD patients.
Purpose of the Study:
- To assess the effect of a strict BP target (<130 mmHg) compared to a standard target (<140 mmHg) on cardiovascular and renal events in DKD patients.
- To analyze the association between achieved BP levels and clinical outcomes post-hoc.
Main Methods:
- A post-hoc analysis of the FANTASTIC trial (NCT02620306), a randomized phase III study.
- 341 DKD patients were assigned to standard (<140 mmHg SBP) or strict (<130 mmHg SBP) BP control.
- Outcomes included cardiovascular and renal events; analyses also considered achieved average SBP levels.
Main Results:
- Mean SBP was similar in both groups (approx. 140 mmHg).
- Strict BP control (<130 mmHg) did not significantly reduce cardiovascular/renal events (HR 1.32).
- Achieved SBP of 130-139 mmHg was associated with reduced risk (HR 0.15), but further reduction (<130 mmHg) showed no additional benefit.
Conclusions:
- Targeting SBP <130 mmHg did not improve outcomes compared to <140 mmHg in DKD patients.
- Achieved SBP within the 130-139 mmHg range correlated with decreased cardiovascular/renal event risk.
Background:
The target blood pressure (BP) value is unclear for diabetic kidney disease (DKD). Therefore, we aimed to evaluate the effect of strict BP control or 'on treatment' BP on clinical outcomes in patients with DKD.
Methods:
A post-hoc analysis of the prespecified secondary outcomes of the FimAsartaN proTeinuriA SusTaIned reduCtion in comparison with losartan in diabetic chronic kidney disease (FANTASTIC) trial, a randomized multicenter double-blind phase III trial. Eligible patients were aged ≥ 19 years with DKD. We assigned 341 participants with DKD to BP control strategy (standard-systolic BP [SBP] < 140 mmHg versus strict-SBP < 130 mmHg). The outcome was the occurrence of cardiovascular events and renal events. Separate analyses were performed to compared the risk of outcome according to achieved average BP levels.
Results:
A total of 341 participants were included in the analysis. Over a median follow-up of 2.8 years, cardiovascular/renal events were observed in 25 (7.3%) participants. Mean (SD) SBPs in the standard and strict BP control group were 140.2 (11.6) and 140.2 (11.9) mmHg, respectively. The strict BP control group did not show significantly reduced risk of cardiovascular/renal events (HR 1.32; 95% CI 0.60-2.92]). In the post-hoc analyses using achieved BP, achieved average SBP of 130-139 mmHg resulted in reduced risk of cardiovascular/renal events (HR 0.15; 95% CI 0.03-0.67) compared to achieved average SBP ≥ 140 mmHg, whereas further reduction in achieved average SBP < 130 mmHg did not impart additional benefits.
Conclusion:
In patients with DKD, targeting a SBP of less than 130 mmHg, as compared with less than 140 mmHg, did not reduce the rate of a composite of cardiovascular and renal events. Achieved SBP of 130-139 mmHg was associated with a decreased risk for the primary outcome in patients with DKD.
Trial Registration:
ClinicalTirals.gov Identifier: NCT02620306, registered December 3, 2015. ( https://clinicaltrials.gov/study/NCT02620306 ).


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Blood Pressure
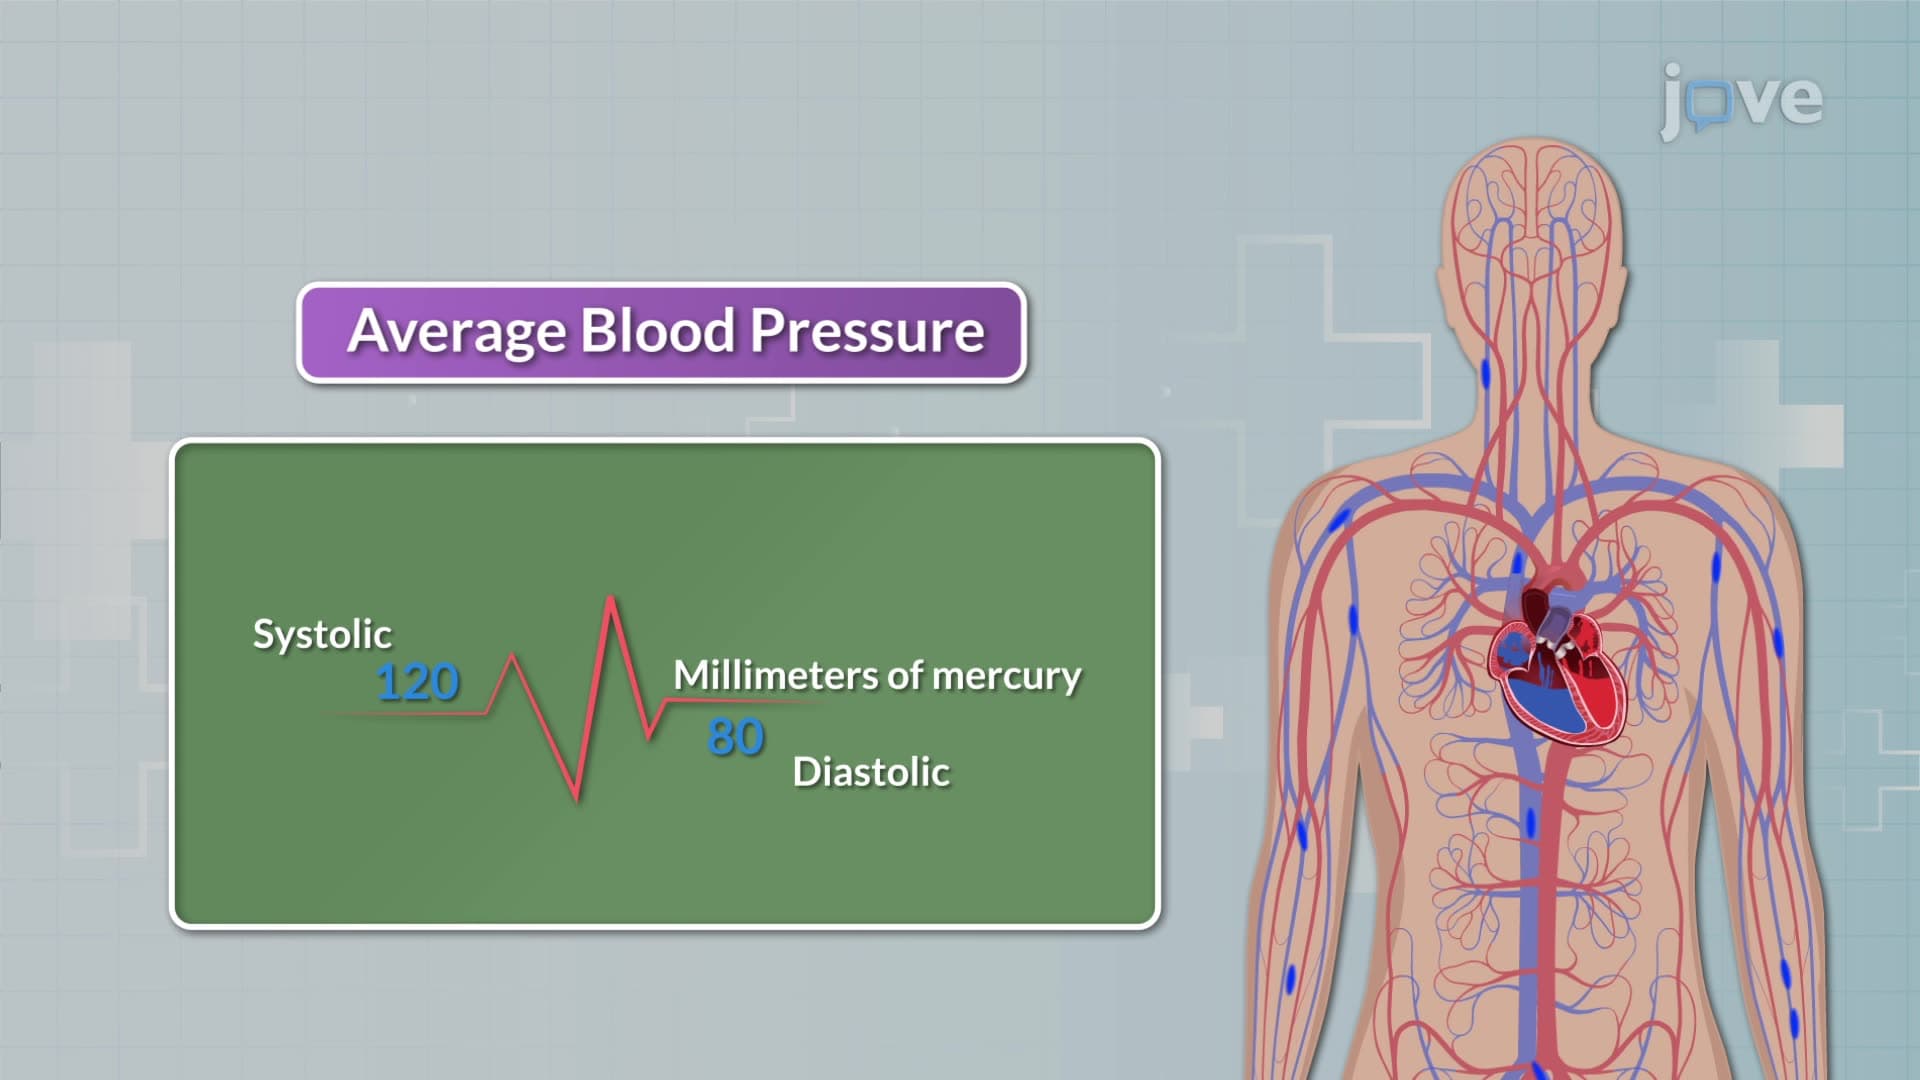
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:22
Heart Failure Drugs: Diuretics
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors