Related Experiment Video
Updated: Jun 18, 2025
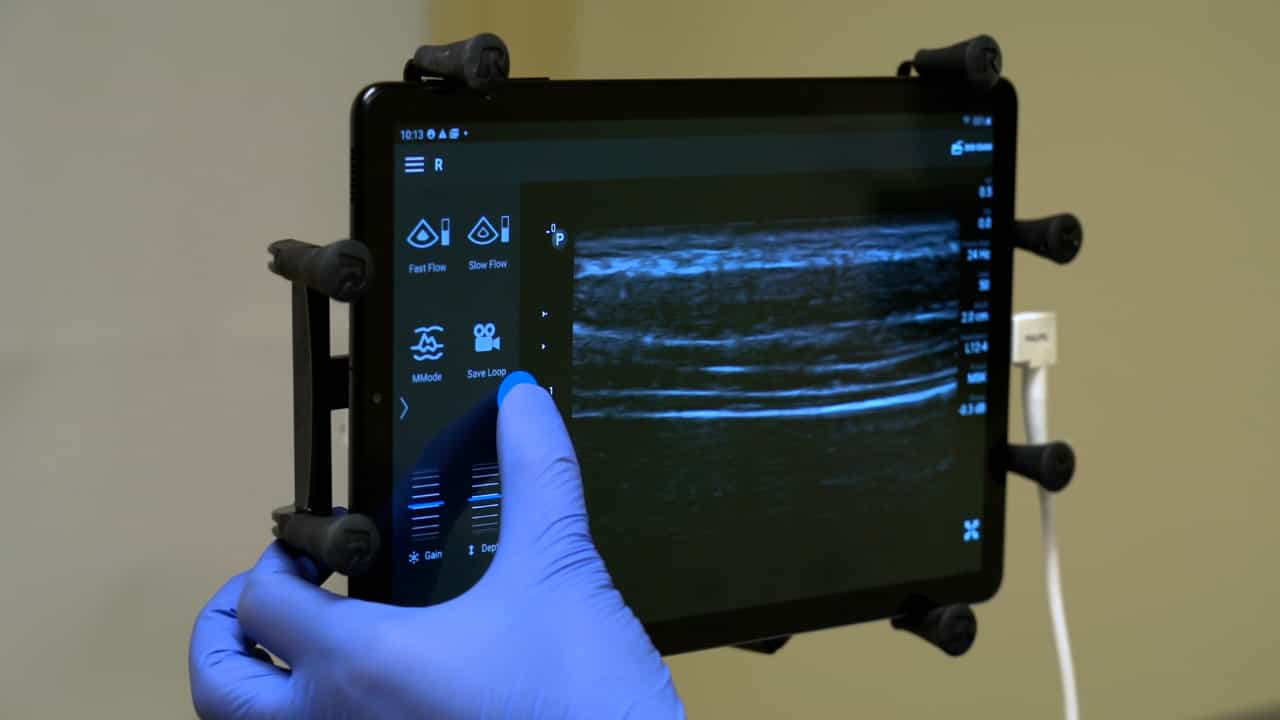

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Ultrasonographic Assessment of Diaphragm Function to Predict Need for Mechanical Ventilation and its Liberation in
Shalini Nair1, Atul More2, Reka Karupassamy3
1Neurointensive Care Unit, Christian Medical College, Vellore, Tamil Nadu, India. drshalininair@cmcvellore.ac.in.

Background:
Management of assisted ventilation and determining the optimal timing for discontinuation presents a significant clinical obstacle in patients affected by neuromuscular (NM) diseases. This study aimed to evaluate the efficacy of ultrasound in appraising diaphragmatic function for predicting the necessity of intubation and determining the opportune moment to discontinue mechanical ventilation (MV) in patients with NM disorders.
Methods:
The study was conducted in adult patients with NM diseases requiring inpatient care in the high-dependency neurology ward and the intensive care unit. Ultrasonographic assessment of diaphragmatic excursion (DE) and diaphragmatic thickness fraction (DTF) was conducted at the patient's bedside every 48 h for ventilated patients and every 72 h for nonventilated patients until they were weaned from the ventilator or discharged home. Qualitative data are expressed as percentages or numbers, and quantitative data are represented as mean ± standard deviation. Unpaired t-tests were employed to compare continuous variables, and χ2 tests were used for categorical variables. Contingency table analysis was used to compute relative risks in comparing the baseline DE and DTF with the sequential changes in these values.
Results:
In cases in which the baseline left DE measured less than 1 cm, the relative risk for the requirement of ventilation was 2.5 times higher, with a confidence interval of 0.62-0.99 (P = 0.19). Notably, a bilateral reduction in DE within the initial 48 h of admission was identified as predictive of need for intubation. When comparing ventilated and nonventilated patients, it was observed that the mean DE values for the left and right sides in ventilated patients (0.74 and 0.79) were significantly lower than those in nonventilated patients (1.3 and 1.66), with corresponding P values of 0.05 and 0.01, respectively. Furthermore, a decline in right DE by more than 50% within 72 h of admission presented a relative risk of 3.3 for the necessity of ventilation, with a confidence interval of 1.29-8.59 (P = 0.01). Duration of ventilation ranged from 2 to 45 days, with an average of 13.14 days, whereas the mean ventilator-free days recorded was 13.57. Notably, a sequential increase in bilateral DE correlated with an extended duration of ventilator-free days.
Conclusions:
The presence of a baseline left DE of less than 1 cm, a consecutive decrease in DE measurements within 48 h, and a comparative reduction in right DE of more than 50% within the initial 3 days are indicators associated with the requirement for MV in patients with NM disease. Furthermore, the upward trajectory of DE in mechanically ventilated patients is linked to an increased number of days free from ventilator support, suggesting its potential to forecast earlier weaning.


Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: