Related Experiment Video
Updated: Jul 19, 2026


A Postoperative Evaluation Guideline for Computer-Assisted Reconstruction of the Mandible
Published on: January 28, 2020
Does the Angulation of the Screws in the Zero-P Implant Affect the Clinical and Radiological Outcomes of Patients?
Cheng-Yi Huang1, Xia-Qing Sheng1, Ting-Kui Wu1
1Department of Orthopedics, Orthopedic Research Institute, West China Hospital, Sichuan University, Chengdu, China.

Objective:
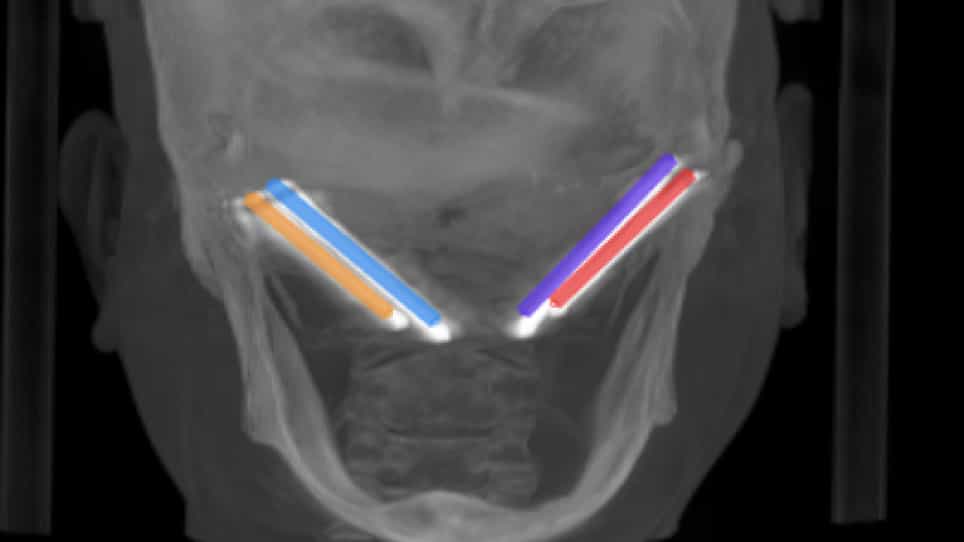
When implanting the Zero-P device, the screws of Zero-P form a bone wedge with a 40 ± 5° cranial and caudal angle (CCA). However, no study has been performed in the optimal CCA of the Zero-P implant. To investigate whether the cranial/caudal angles (CCA) of the screws affect the clinical and radiological outcomes in patients undergoing ACDF with the Zero-P implant.
Methods:
From January 2016 to December 2023, we retrospectively analyzed 186 patients who underwent 1-level ACDF with the Zero-P device. The patients were divided into four groups: group A (cranial angle ≤40°, caudal angle ≤40°); group B (cranial angle ≤40°, caudal angle >40°); group C (cranial angle >40°, caudal angle ≤40°); and group D (cranial angle >40°, caudal angle >40°). The clinical outcomes, including Japanese Orthopaedic Association (JOA), neck disability index (NDI), and visual analogue scale (VAS) scores, the radiological parameters, including cervical lordosis (CL), cervical lordosis of operated segments (OPCL), intervertebral space height (ISH) and fusion rate (FR), and the complications, were evaluated and compared. Parametric tests, non-parametric tests, and chi-square tests were conducted to analyze the data.
Results:
The OPCL of group A was significantly less than that of the other groups at the final follow-up (p < 0.05). The ISH of group D was significantly less than that of group A at the final follow-up (p < 0.05). The subsidence rate of group A was significantly less than that of group D at the final follow-up (p < 0.05). At the final follow-up, the upper adjacent-level degeneration (ASD) of group D was significantly less severe than that of groups A and B (p < 0.05). The clinical outcomes do not differ among groups (p > 0.05).
Conclusion:
A larger CCA of the screws (cranial angle >40°, caudal angle >40°) was better for maintaining OPCL and reducing the incidence of ASD. A smaller CCA of the screws (cranial angle ≤40°, caudal angle ≤40°) was better for maintaining ISH and reducing the rate of subsidence.