Related Experiment Video
Updated: Jun 17, 2025

Standardized Colon Ascendens Stent Peritonitis in Rats - a Simple, Feasible Animal Model to Induce Septic Acute Kidney Injury
Published on: February 15, 2022
High-volume hemofiltration does not protect human kidney endothelial and tubular epithelial cells from septic
Davide Medica1, Alessandro D Quercia2, Marita Marengo2
1Nephrology and Kidney Transplantation Unit, Department of Translational Medicine (DIMET), University of Piemonte Orientale (UPO), "Maggiore Della Carità" University Hospital, via Gen. P. Solaroli 17, 28100, Novara, Italy.

High volume hemofiltration (HVHF) could remove from plasma inflammatory mediators involved in sepsis-associated acute kidney injury (SA-AKI). The IVOIRE trial did not show improvements of outcome and organ dysfunction using HVHF. The aim of this study was to evaluate in vitro the biological effects of plasma of patients treated by HVHF or standard volume hemofiltration (SVHF). We evaluated leukocyte adhesion, apoptosis and functional alterations of endothelial cells (EC) and tubular epithelial cells (TEC). In vitro data were correlated with plasma levels of TNF-α, Fas-Ligand (FasL), CD40-Ligand (CD40L), von Willebrand Factor (vWF) and endothelial-derived microparticles. An experimental model of in vitro hemofiltration using LPS-activated blood was established to assess cytokine mass adsorption during HVHF or SVHF. Plasma concentrations of TNF-ɑ, FasL, CD40L and von Willebrand Factor (vWF) were elevated at the start (d1h0) of both HVHF and SVHF, significantly decreased after 6 h (d1h6), remained stable after 12 h (d1h12) and then newly increased at 48 h (d3h0). Plasma levels of all these molecules were similar between HVHF- and SVHF-treated patients at all time points considered. In addition, the levels of endothelial microparticles remained always elevated, suggesting the presence of a persistent microvascular injury. Plasma from septic patients induced leukocyte adhesion on EC and TEC through up-regulation of adhesion receptors. Moreover, on EC, septic plasma induced a cytotoxic and anti-angiogenic effect. On TEC, septic plasma exerted a direct pro-apoptotic effect via Fas up-regulation and caspase activation, loss of polarity, altered expression of megalin and tight junction molecules with an impaired ability to internalize albumin. The inhibition of plasma-induced cell injury was concomitant to the decrease of TNF-α, Fas-Ligand and CD40-Ligand levels. The protective effect of both HVHF and SVHF was time-limited, since a further increase of circulating mediators and plasma-induced cell injury was observed after 48 h (d3h0). No significant difference of EC/TEC damage were observed using HVHF- or SVHF-treated plasma. The in vitro hemofiltration model confirmed the absence of a significant modulation of cytokine adsorption between HVHF and SVHF. In comparison to SVHF, HVHF did not increase inflammatory cytokine clearance and did not reverse the detrimental effects of septic plasma-induced EC and TEC injury. Further studies using adsorptive membranes are needed to evaluate the potential role of high dose convective therapies in the limitation of the harmful activity of plasma soluble factors involved in SA-AKI.Trial registration IVOIRE randomized clinical trial; ClinicalTrials.gov (NCT00241228) (18/10/2005).
High volume hemofiltration (HVHF) could remove from plasma inflammatory mediators involved in sepsis-associated acute kidney injury (SA-AKI). The IVOIRE trial did not show improvements of outcome and organ dysfunction using HVHF. The aim of this study was to evaluate in vitro the biological effects of plasma of patients treated by HVHF or standard volume hemofiltration (SVHF). We evaluated leukocyte adhesion, apoptosis and functional alterations of endothelial cells (EC) and tubular epithelial cells (TEC). In vitro data were correlated with plasma levels of TNF-α, Fas-Ligand (FasL), CD40-Ligand (CD40L), von Willebrand Factor (vWF) and endothelial-derived microparticles. An experimental model of in vitro hemofiltration using LPS-activated blood was established to assess cytokine mass adsorption during HVHF or SVHF. Plasma concentrations of TNF-ɑ, FasL, CD40L and von Willebrand Factor (vWF) were elevated at the start (d1h0) of both HVHF and SVHF, significantly decreased after 6 h (d1h6), remained stable after 12 h (d1h12) and then newly increased at 48 h (d3h0). Plasma levels of all these molecules were similar between HVHF- and SVHF-treated patients at all time points considered. In addition, the levels of endothelial microparticles remained always elevated, suggesting the presence of a persistent microvascular injury. Plasma from septic patients induced leukocyte adhesion on EC and TEC through up-regulation of adhesion receptors. Moreover, on EC, septic plasma induced a cytotoxic and anti-angiogenic effect. On TEC, septic plasma exerted a direct pro-apoptotic effect via Fas up-regulation and caspase activation, loss of polarity, altered expression of megalin and tight junction molecules with an impaired ability to internalize albumin. The inhibition of plasma-induced cell injury was concomitant to the decrease of TNF-α, Fas-Ligand and CD40-Ligand levels. The protective effect of both HVHF and SVHF was time-limited, since a further increase of circulating mediators and plasma-induced cell injury was observed after 48 h (d3h0). No significant difference of EC/TEC damage were observed using HVHF- or SVHF-treated plasma. The in vitro hemofiltration model confirmed the absence of a significant modulation of cytokine adsorption between HVHF and SVHF. In comparison to SVHF, HVHF did not increase inflammatory cytokine clearance and did not reverse the detrimental effects of septic plasma-induced EC and TEC injury. Further studies using adsorptive membranes are needed to evaluate the potential role of high dose convective therapies in the limitation of the harmful activity of plasma soluble factors involved in SA-AKI.Trial registration IVOIRE randomized clinical trial; ClinicalTrials.gov (NCT00241228) (18/10/2005).


Related Concept Videos
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Glomerular Filtration
Components of the Filtration Membrane
The filtration process involves three key layers: the glomerular endothelial cells, the basement membrane, and the podocyte-formed filtration slits.
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...
 01:10
Nephrons
 01:02
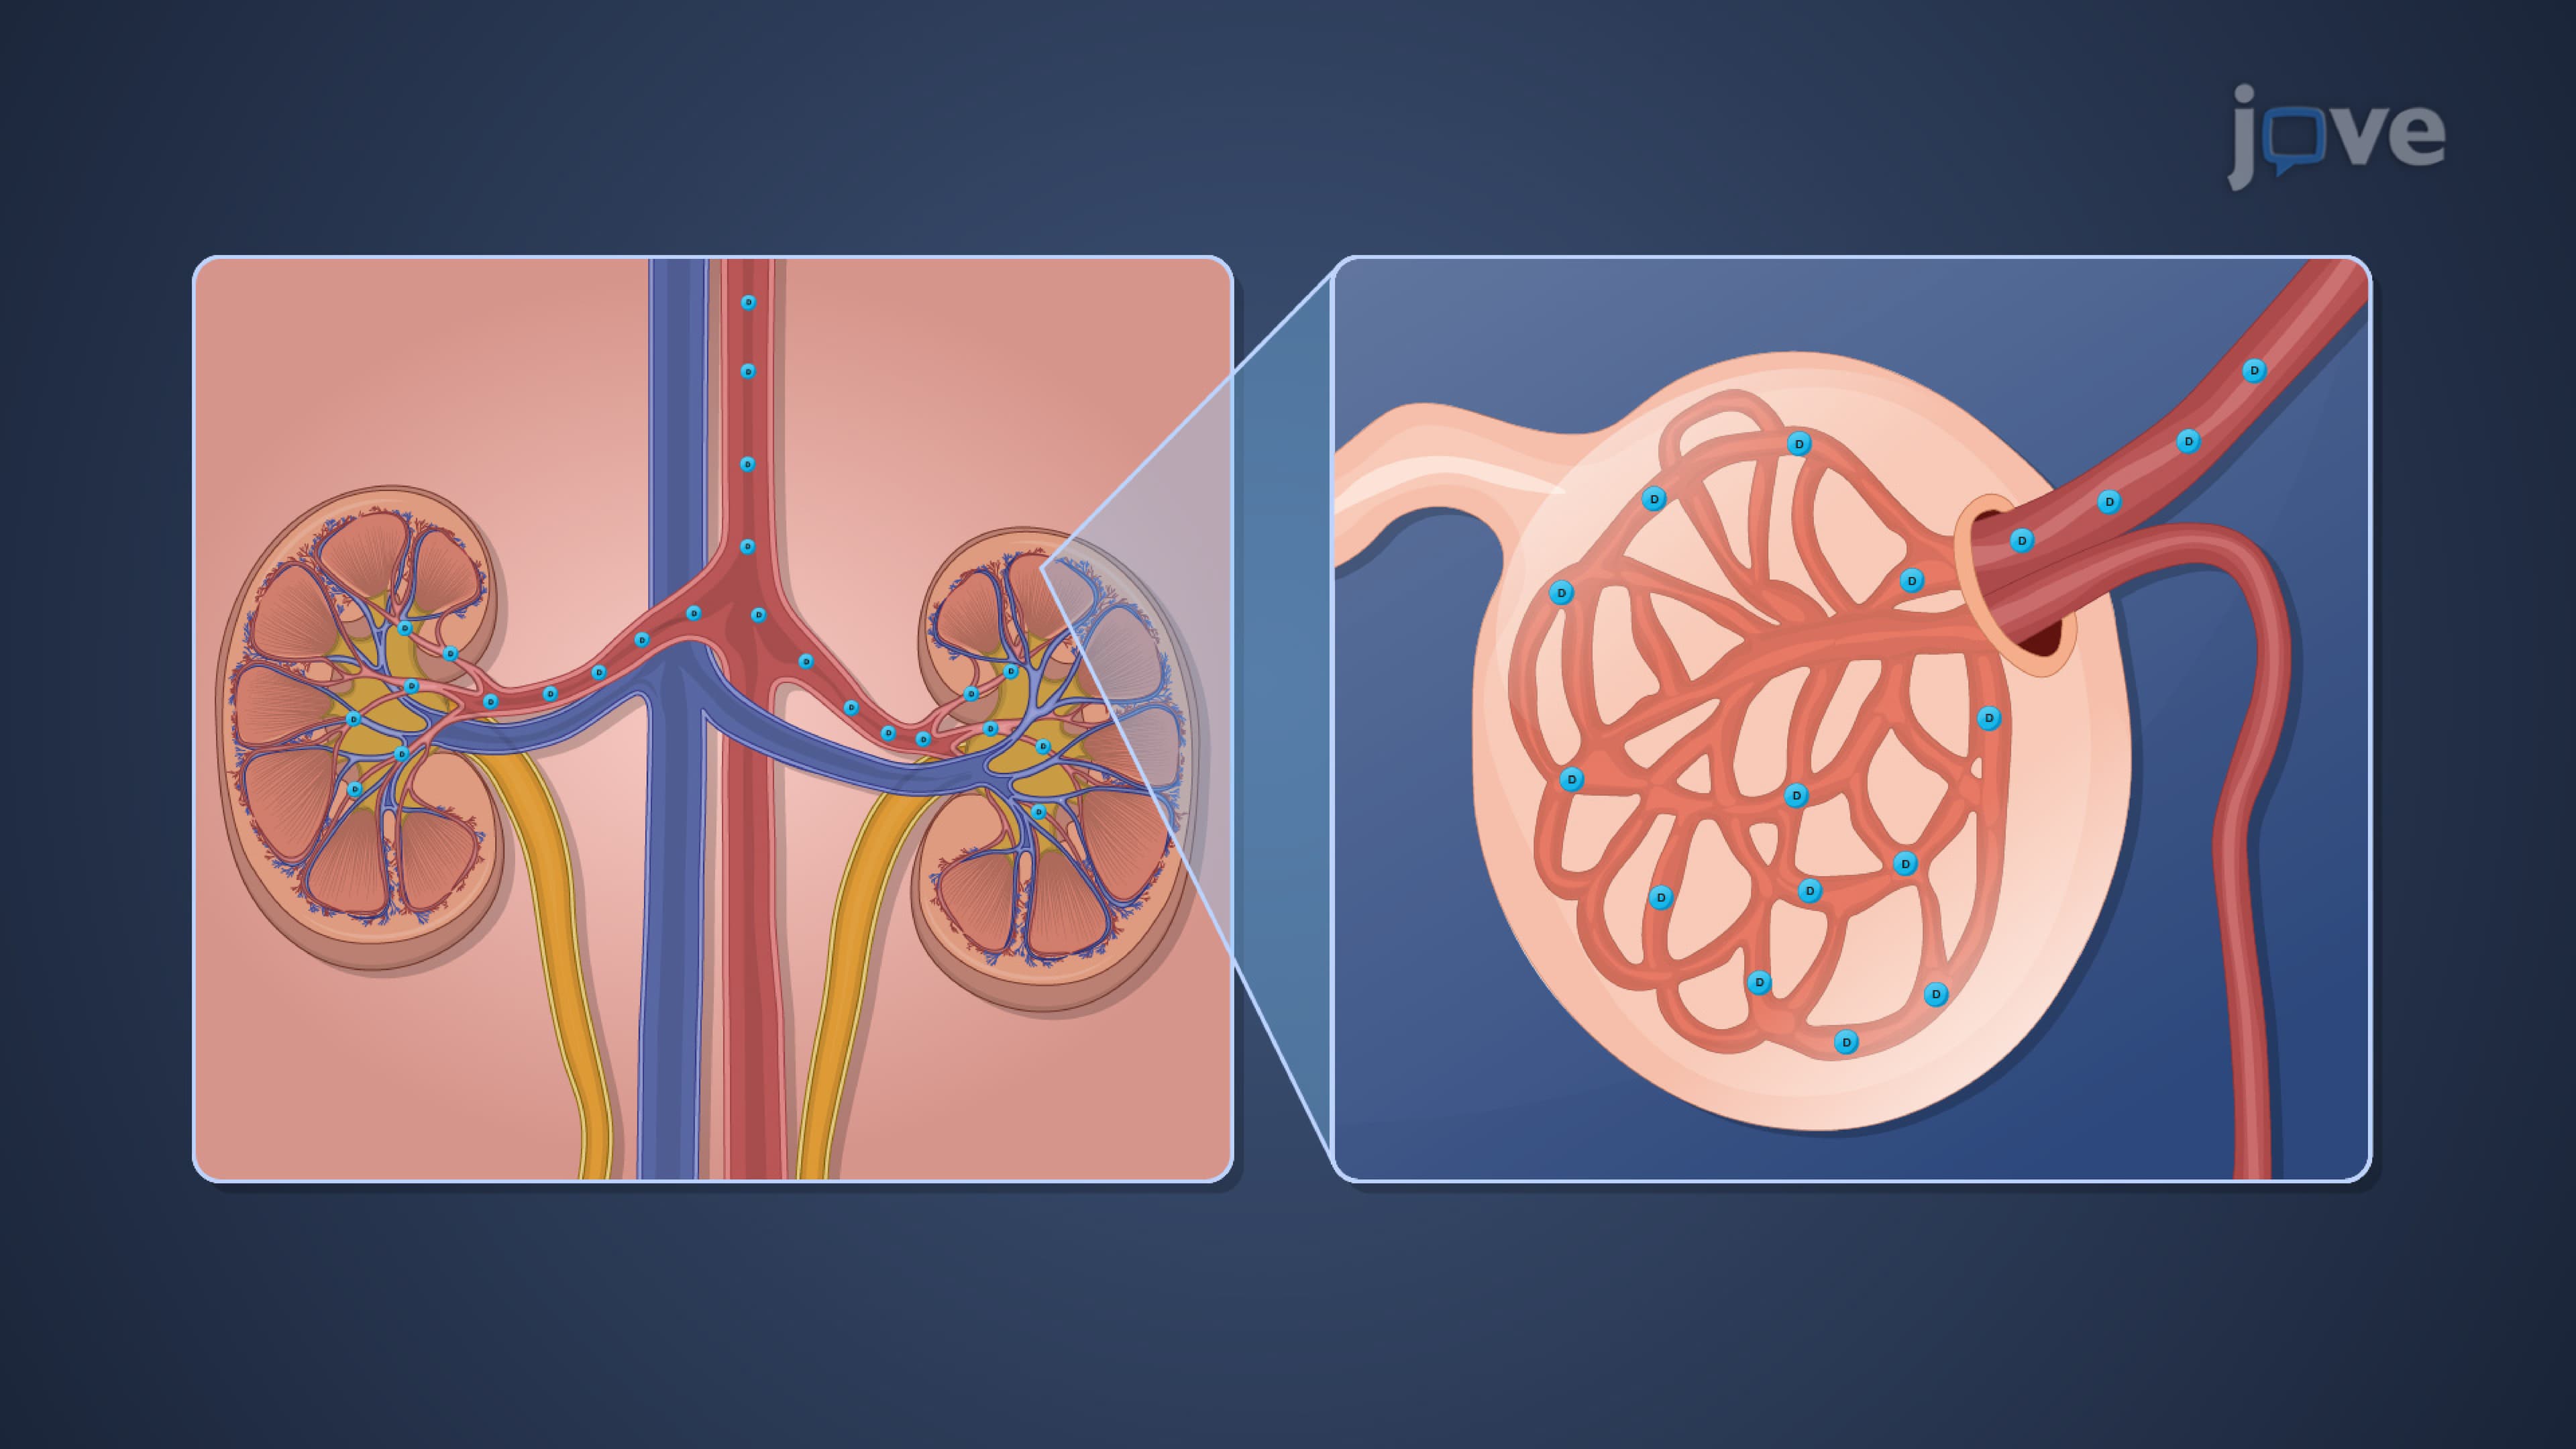
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:45
Kidney Structure