Related Experiment Video
Updated: Jun 17, 2025

TBase - an Integrated Electronic Health Record and Research Database for Kidney Transplant Recipients
Published on: April 13, 2021
The spectrum of co-existing disease in children with established kidney failure using registry and linked electronic
Lucy Plumb1,2, Retha Steenkamp3, Alexander J Hamilton4
1UK Renal Registry, UK Kidney Association, Brandon House Building 20A1, Filton 20, Filton, Bristol, BS34 7RR, UK. lucy.plumb@nhs.net.

Insights
Electronic health records often under-report co-existing diseases in children with kidney failure compared to registry data. Agreement between datasets is only moderate, highlighting the need for comprehensive data capture in pediatric kidney care.
Area of Science:
- Pediatric Nephrology
- Clinical Informatics
- Health Data Management
Background:
- Children with kidney failure often have co-existing medical conditions that impact care.
- Accurate documentation of these comorbidities is crucial for effective management and research.
- Electronic health records (EHRs) and national registries are key sources for this data.
Purpose of the Study:
- To compare the prevalence of co-existing diseases in children undergoing kidney replacement therapy (KRT) as recorded in EHRs versus the UK Renal Registry (UKRR).
- To assess the agreement between EHR and UKRR data for comorbidity coding.
- To identify factors influencing the likelihood of comorbidity coding in EHRs.
Main Methods:
- A cross-sectional study of children (<18 years) on KRT in England and Wales as of 31/12/2016.
- Comparison of comorbidity data from hospital EHRs and UKRR at the start of KRT.
- Assessment of data agreement using the kappa statistic and logistic regression for coding factors.
Main Results:
- UKRR data generally showed a higher prevalence of co-existing diseases than EHRs.
- Congenital, non-kidney diseases and malignancies had the highest sensitivity in EHRs.
- Moderate agreement (kappa ≥ 0.41) was observed between EHR and UKRR data; age increased coding odds, while kidney disease and more comorbidities decreased them.
Conclusions:
- EHRs tend to under-report comorbidities in pediatric kidney disease patients compared to registry data.
- While EHRs provide a broad overview for research, UKRR processes are essential for capturing specific pediatric kidney disease variables.
- Improving data consistency between EHRs and registries is vital for comprehensive patient care and research.
Background:
Children with established kidney failure may have additional medical conditions influencing kidney care and outcomes. This cross-sectional study aimed to examine the prevalence of co-existing diseases captured in the electronic hospital record compared to UK Renal Registry (UKRR) data and differences in coding.
Methods:
The study population comprised children aged < 18 years receiving kidney replacement therapy (KRT) in England and Wales on 31/12/2016. Comorbidity data at KRT start was examined in the hospital record and compared to UKRR data. Agreement was assessed by the kappa statistic. Associations between patient and clinical factors and likelihood of coding were examined using multivariable logistic regression.
Results:
A total of 869 children (62.5% male) had data linkage for inclusion. UKRR records generally reported a higher prevalence of co-existing disease than electronic health records; congenital, non-kidney disease was most commonly reported across both datasets. The highest sensitivity in the hospital record was seen for congenital heart disease (odds ratio (OR) 0.65, 95% confidence interval (CI) 0.51, 0.78) and malignancy (OR 0.63, 95% CI 0.41, 0.85). At best, moderate agreement (kappa ≥ 0.41) was seen between the datasets. Factors associated with higher odds of coding in hospital records included age, while kidney disease and a higher number of comorbidities were associated with lower odds of coding.
Conclusions:
Health records generally under-reported co-existing disease compared to registry data with fair-moderate agreement between datasets. Electronic health records offer a non-selective overview of co-existing disease facilitating audit and research, but registry processes are still required to capture paediatric-specific variables pertinent to kidney disease.


Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:29
Renal Regulation of Acid-Base Balance
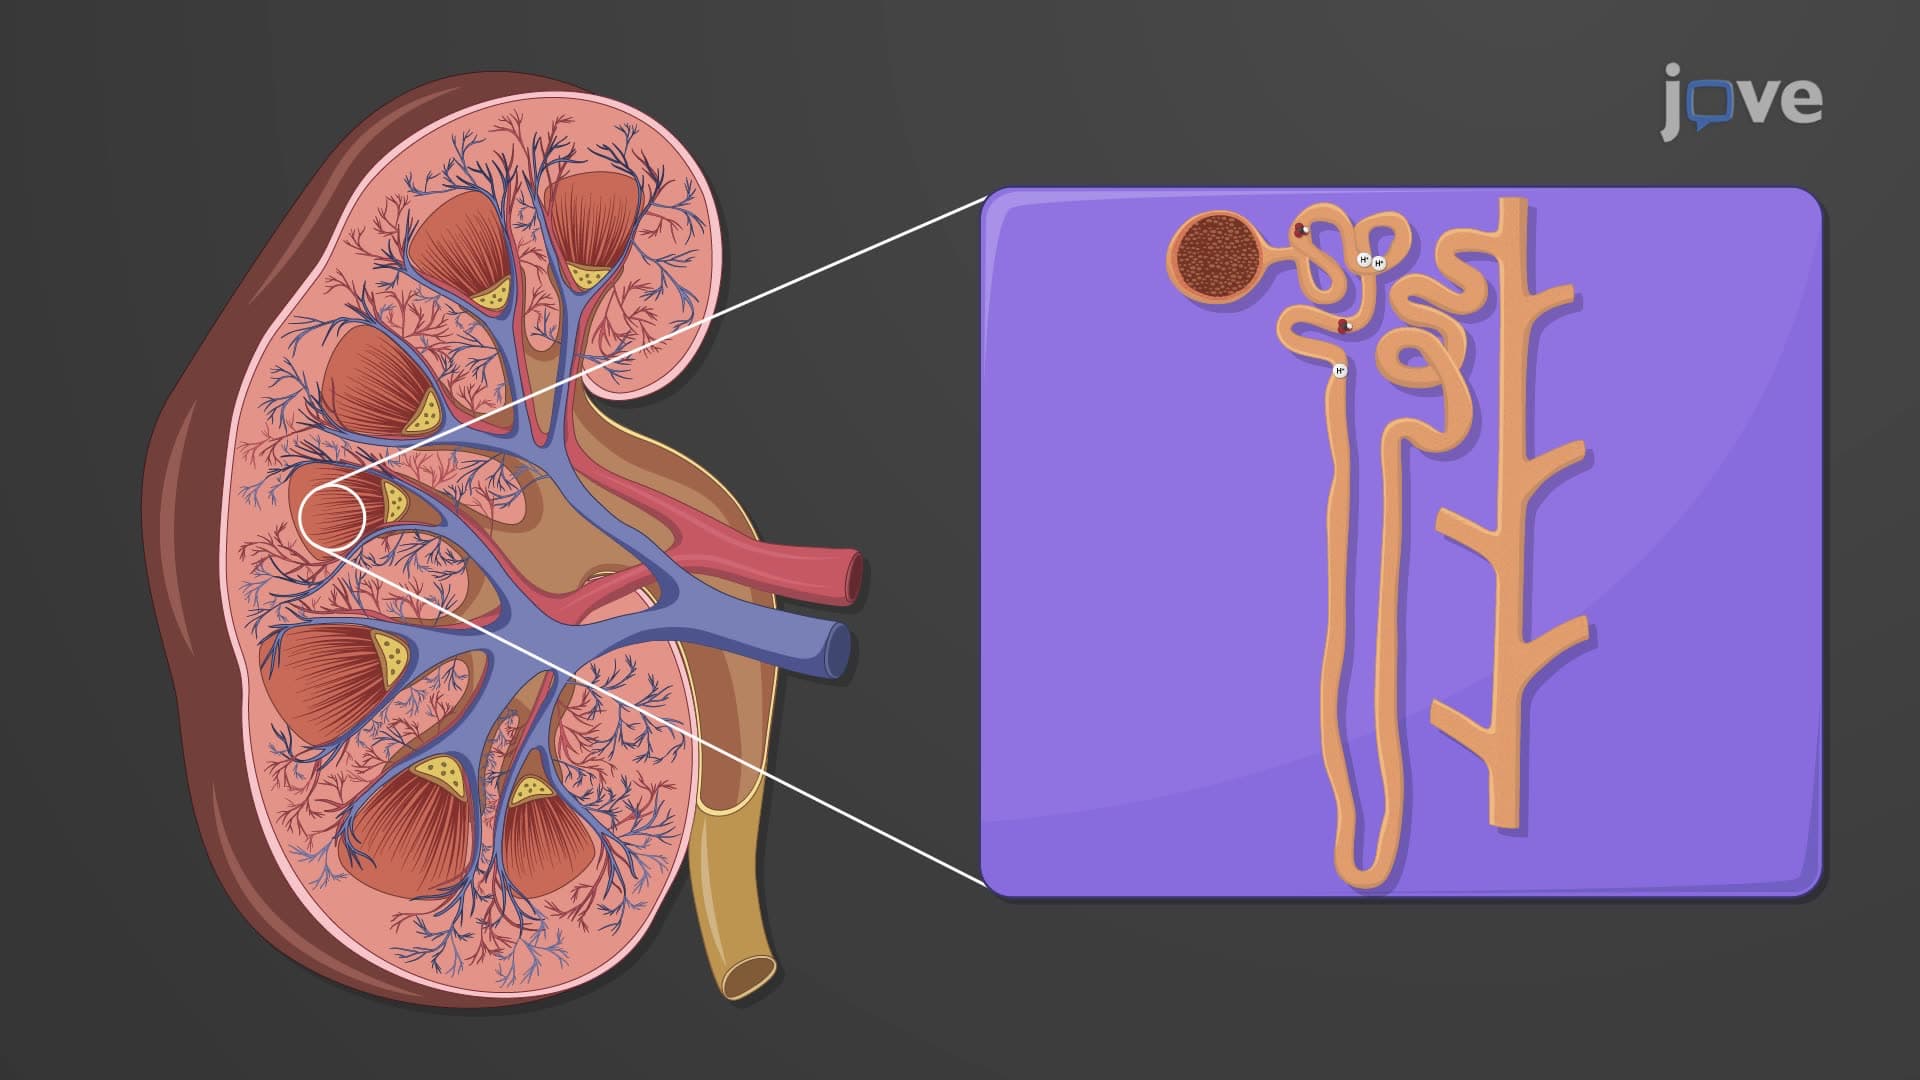
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:15
Renal Drug Excretion: Overview
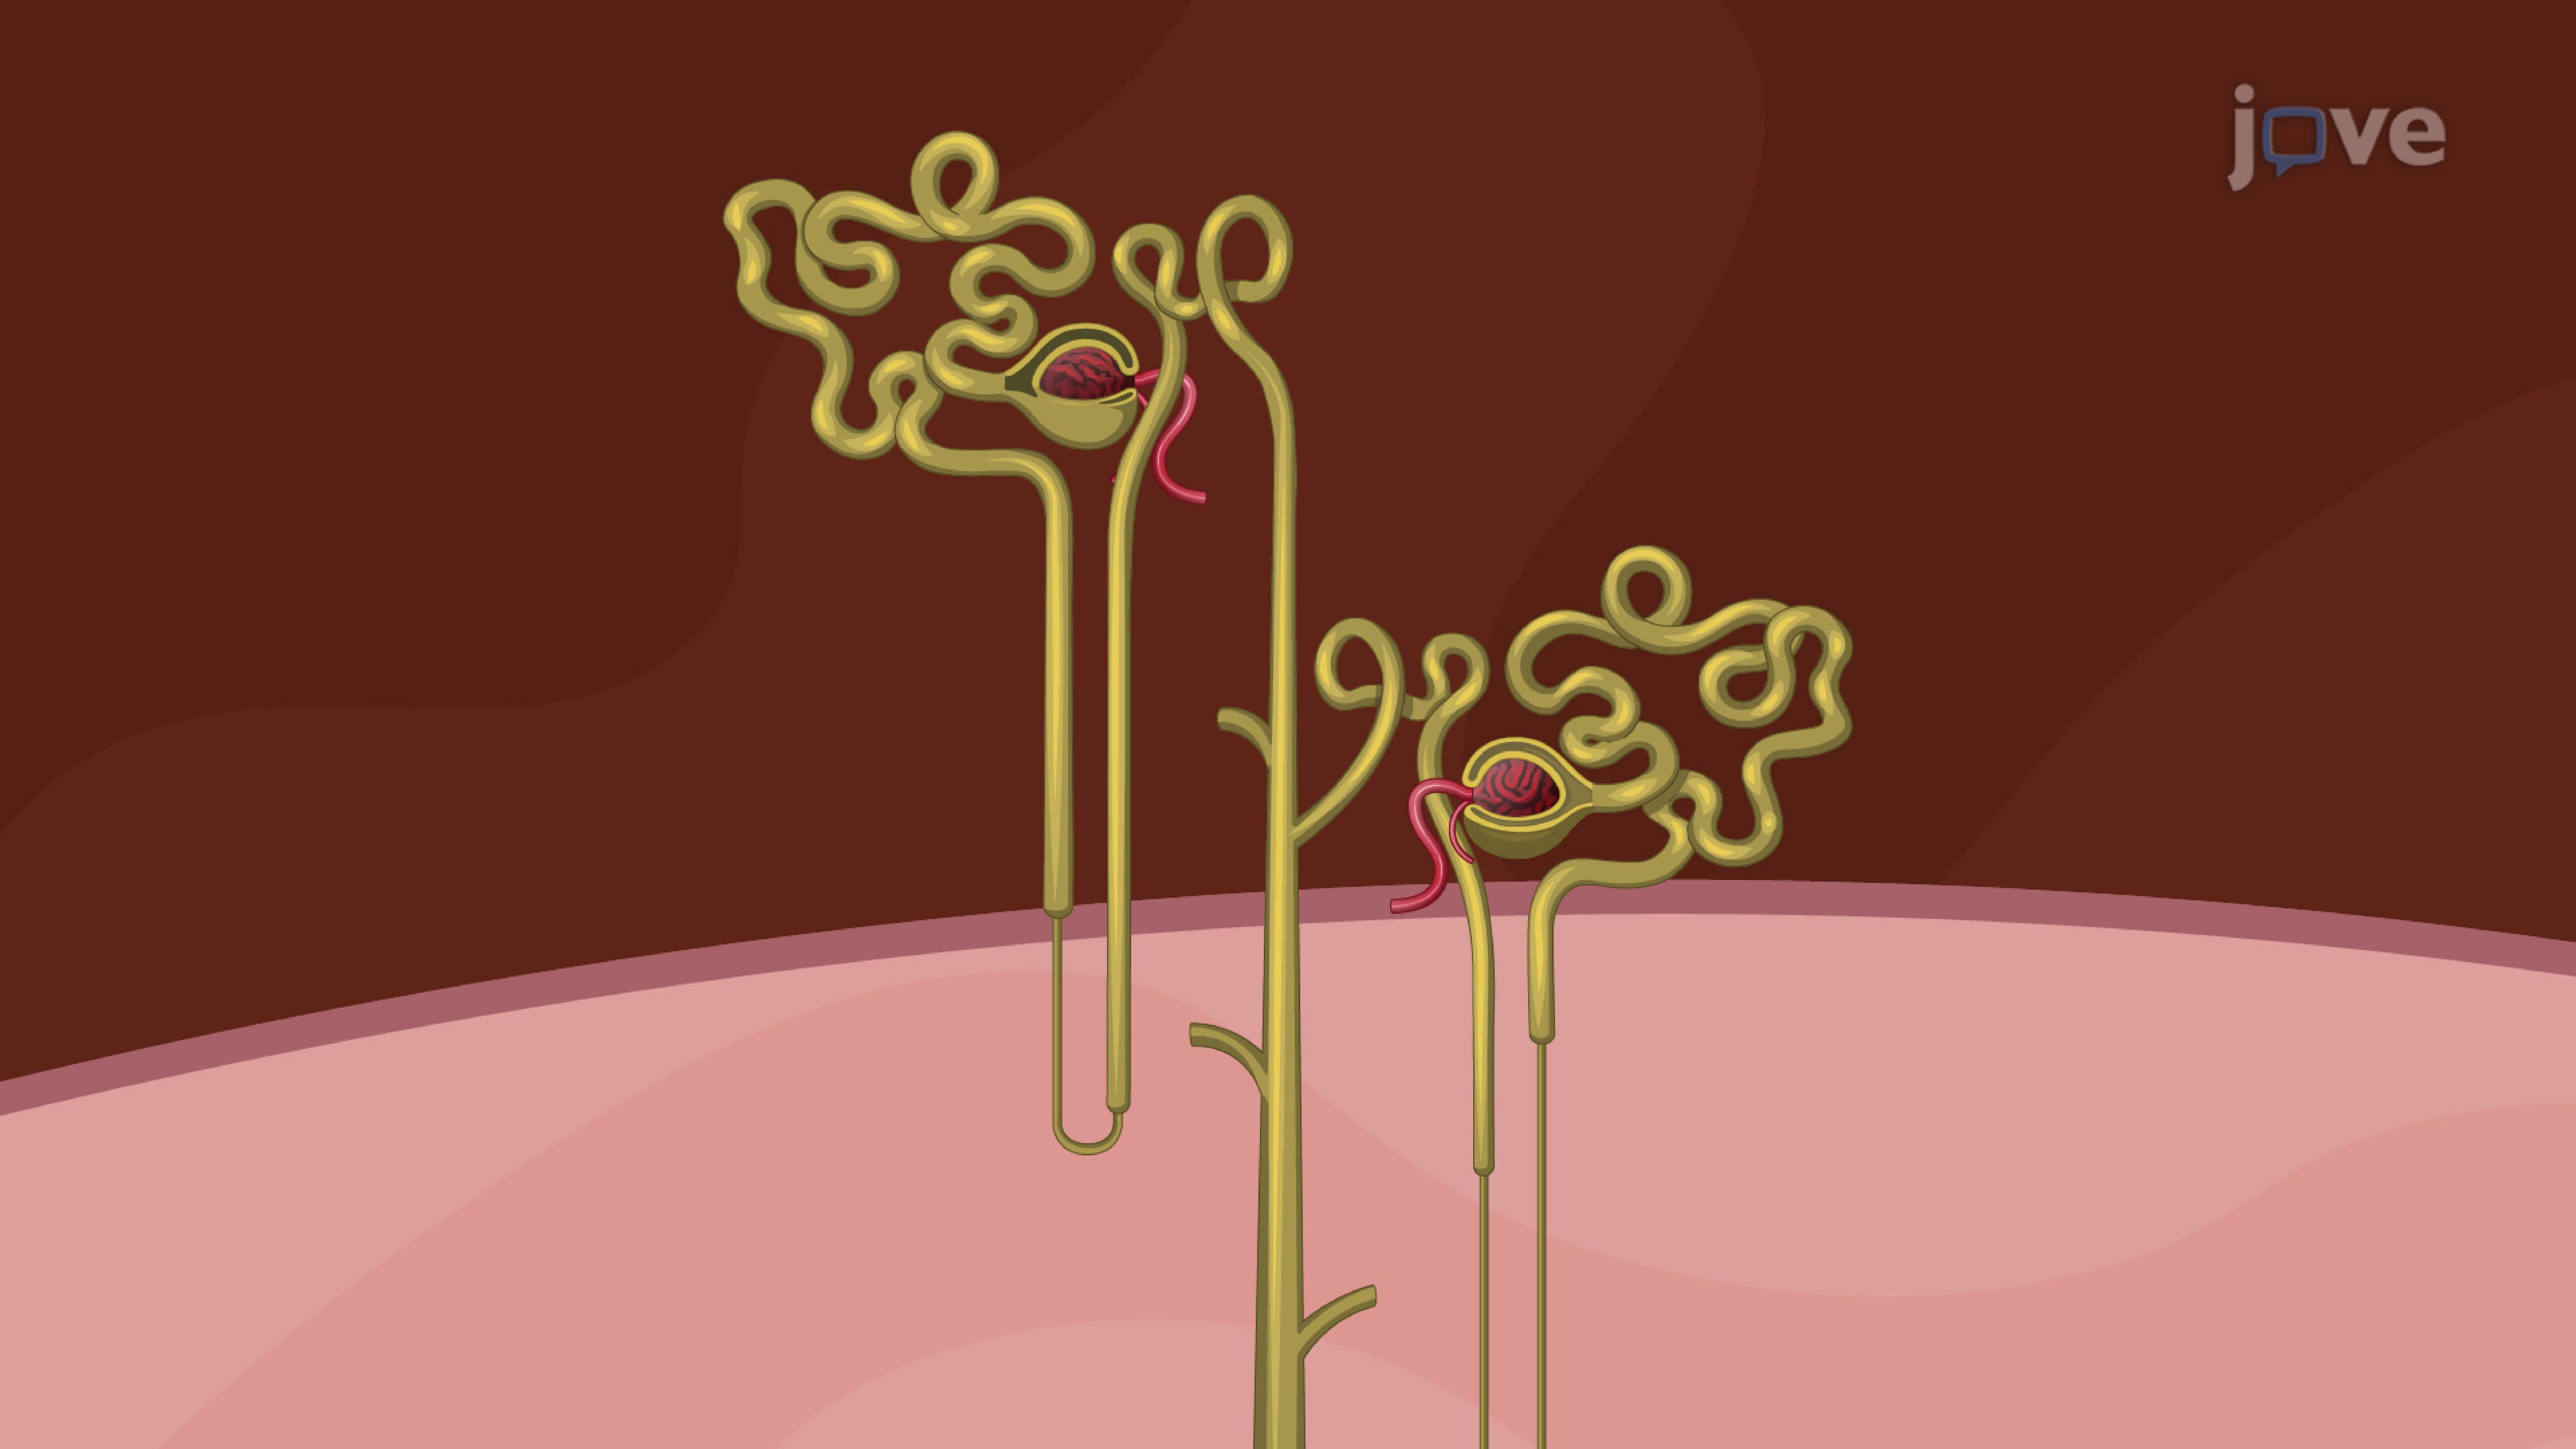
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:10
Nephrons
 01:06
Renal Drug Clearance: Overview
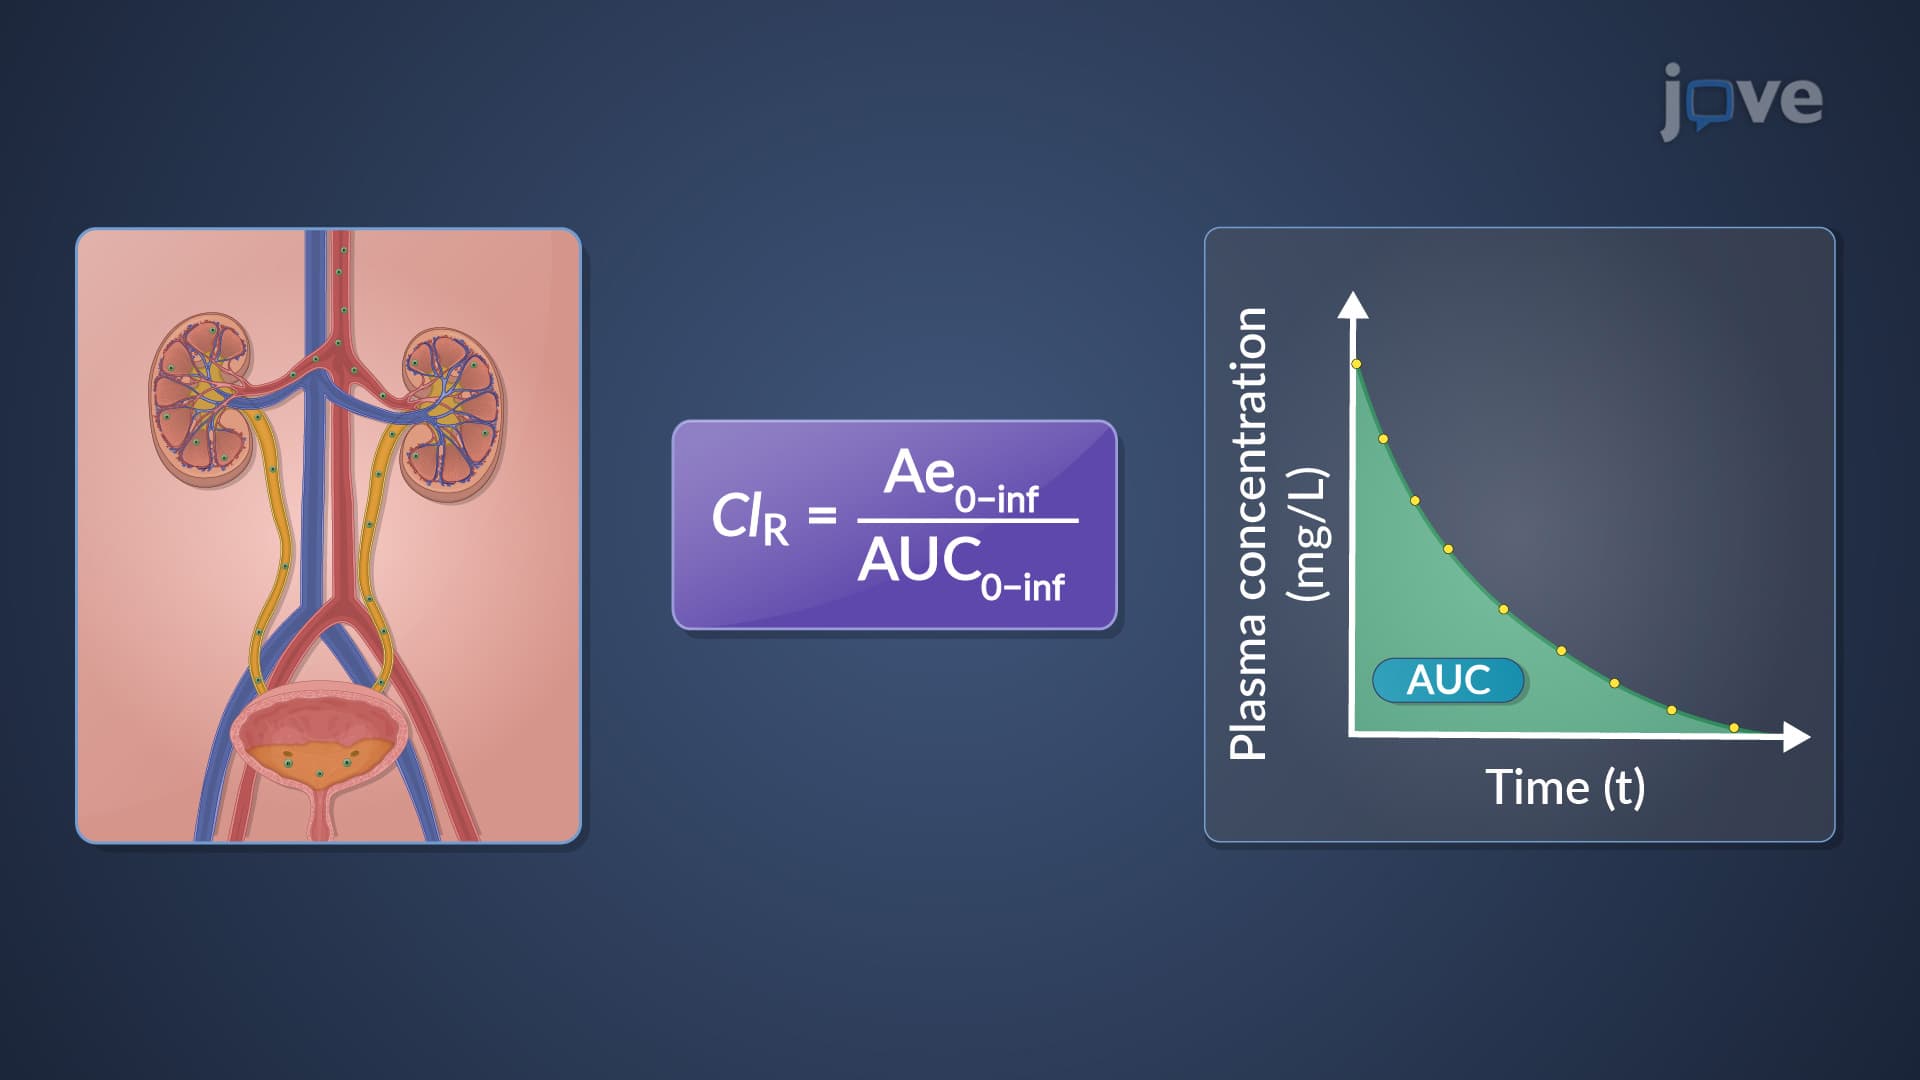
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...