Related Experiment Video
Updated: Jun 17, 2025
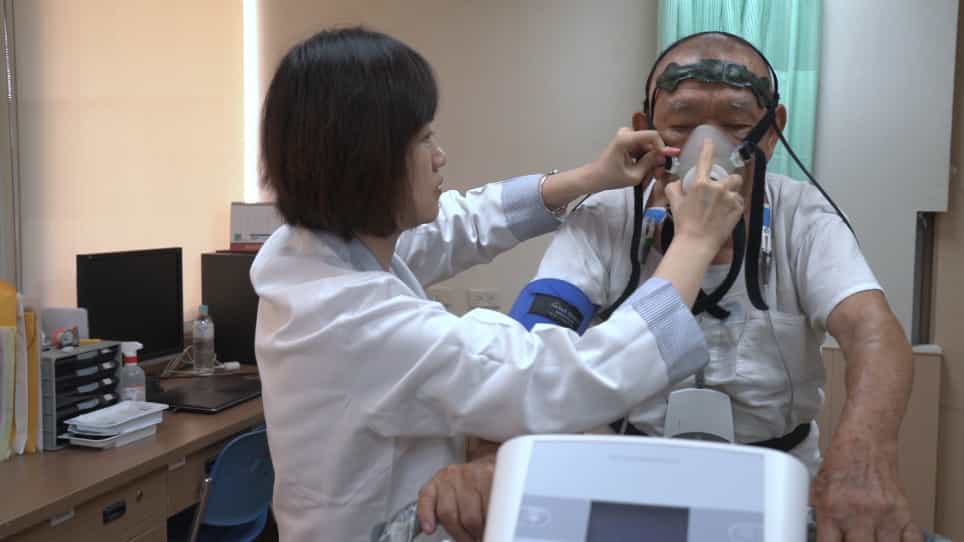
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Impact of sodium-glucose cotransporter-2 inhibitor use on peak VO2 in advanced heart failure patients
1Division of Advanced Heart Failure and Transplant Cardiology, Mayo Clinic, Jacksonville, FL, United States.

Insights
Sodium-glucose co-transporter inhibitors (SGLT2i) did not improve functional capacity in advanced heart failure patients treated with optimal medical therapy (OMT). Peak oxygen consumption (peak VO2) remained unchanged after SGLT2i addition, suggesting other benefits may drive improved outcomes.
Area of Science:
- Cardiology
- Endocrinology
- Exercise Physiology
Background:
- Advanced heart failure (HF) significantly impacts multiple organ systems, leading to high morbidity and mortality.
- Optimal medical therapy (OMT) is standard for HF, but outcomes remain suboptimal, especially in type 2 diabetes patients.
- Sodium-glucose co-transporter inhibitors (SGLT2i) have shown promise in reducing mortality and hospital admissions in HF.
Purpose of the Study:
- To investigate if SGLT2 inhibitors improve functional capacity in advanced heart failure patients.
- To compare changes in maximum oxygen consumption (peak VO2) using cardiopulmonary exercise testing (CPET) between OMT and OMT plus SGLT2i groups.
- To evaluate the effect of SGLT2i on functional capacity relative to baseline values.
Main Methods:
- A single-center study involving 94 advanced heart failure patients from August 2020 to August 2021.
- Patients underwent CPET before and after treatment.
- Comparison of peak VO2 values between patients receiving OMT (n=50) and OMT plus SGLT2i (n=44).
Main Results:
- Baseline characteristics, including ejection fraction and peak VO2, were similar between the OMT and OMT+SGLT2i groups.
- Hemoglobin A1c was significantly lower in the OMT group compared to the SGLT2i group.
- At one-year follow-up, no significant improvement in peak VO2 was observed in the OMT+SGLT2i group compared to their own baseline or the OMT group.
Conclusions:
- The addition of SGLT2i therapy to OMT did not significantly improve functional capacity, as measured by peak VO2, in patients with advanced heart failure.
- Observed improvements in hospitalization and symptoms with SGLT2i may be due to other mechanisms, such as volume management.
- Further research is needed to elucidate the multifaceted benefits of SGLT2i in heart failure management.
Introduction:
Advanced heart failure (HF) is an epidemic that affects multiple organ systems with high morbidity and mortality rates despite optimal medical therapy (OMT) and remains the leading cause of hospitalizations in type 2 diabetes-related cardiovascular disease. The addition of sodium-glucose co-transporter inhibitors (SGLT2i) in treating these patients has seen improved mortality and hospital admission rates. As such, we felt it was important to investigate whether the use of SGLT2i improved functional capacity in patients with HF when compared to OMT by evaluating maximum oxygen consumption (peak VO2) using cardiopulmonary exercise testing (CPET).
Methods:
We found 94 heart failure patients between August 2020 and August 2021 who underwent CPET before and after treatment at Mayo Clinic in Florida. 50 patients received OMT and 44 received OMT and SGLT2i therapy. CPET results before and after were compared for each group.
Results:
The baseline ejection fraction was not significantly different between groups, with the OMT group at 38% and the SGLT2i group at 33%, p = 0.10. OMT patients were found to have a significantly lower hemoglobin A1c of 5.7 (5.4-6.1) compared to those with SGLT2i therapy of 6.4 (5.8-7.1), p = 0.01. The baseline peak VO2 was 17.3 ml/kg/min (13.3-21.6) in the OMT group and 17.3 ml/kg/min (14.4-18.9) in the SGLT2i group, p = 0.18, not significantly different. The interesting finding is that the follow-up peak VO2 at one year for the OMT group was 17 ml/kg/min (13.3-21.6), which was not significantly different from the SGLT2i group peak VO2 of 17 ml/kg/min (14.6-19.6), p = 0.19. Our study is the first to compare before and after peak VO2 values of the OMT+SGLT2i group to the patient's own baseline and we found no significant improvement.
Conclusion:
Our single-center data shows no improvement in functional capacity after the addition of SGLT2i therapy to OMT in patients with advanced heart failure. Improved hospitalization and symptoms may be attributed to other numerous effects of SGLT2i such as volume management.


Related Concept Videos
 01:26
Heart Failure Drugs: Inotropic Agents
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Heart Failure Drugs: Diuretics
 01:22
Heart Failure Drugs: β-Blockers
 01:55
Secondary Active Transport
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...