Related Experiment Video
Updated: Jun 17, 2025
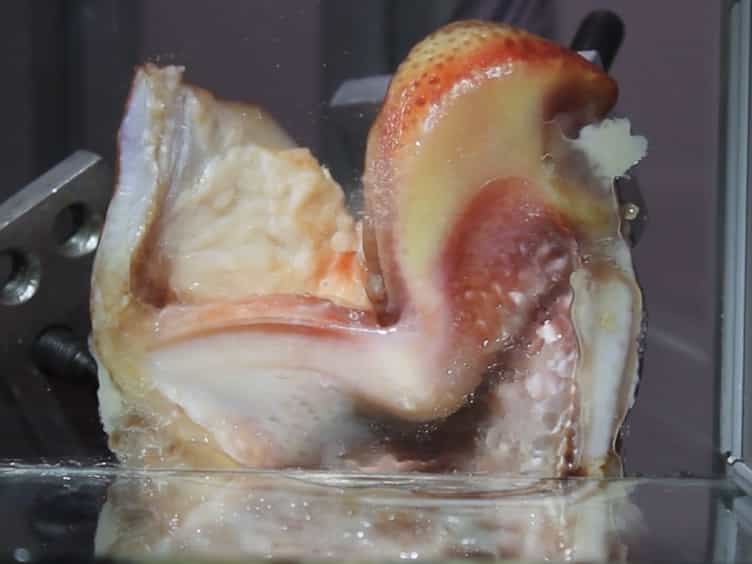

Hemi-laryngeal Setup for Studying Vocal Fold Vibration in Three Dimensions
Published on: November 25, 2017
Evaluation of Pediatric Posterior Glottic Diastasis Using Dynamic Voice Computed Tomography
Anisha R Noble1, Robert J Fleck2, Matthew T Maksimoski1
1Division of Pediatric Otolaryngology, Cincinnati Children's Hospital Medical Center, Cincinnati, Ohio, U.S.A.

Objectives:
Posterior glottic diastasis (PGD) is an underappreciated etiology of dysphonia in patients with prior airway reconstruction or prolonged intubation. In endoscopic posterior cricoid reduction (ePCR), cricoid is removed to minimize the posterior glottic gap. Dynamic voice computed tomography (DVCT) permits visualization of the posterior glottis, estimating the amount of cricoid to be removed. Posterior glottic gaps in patients undergoing ePCR were compared to non-dysphonic patients to describe pediatric PGD and establish surgical parameters for ePCR.
Methods:
DVCTs performed in non-dysphonic patients and dysphonic patients undergoing ePCR from 2014 to 2023 were reviewed. EPCR operative reports were queried. Pre- and postoperative Pediatric Voice Handicap Index (pVHI) and Consensus Auditory-Perceptual Evaluation of Voice (CAPE-V) scores and aerodynamic measures were reviewed.
Results:
Seventeen pediatric patients who underwent ePCR and 19 non-dysphonic patients were included. Posterior glottic gaps were significantly larger in the dysphonic group (median 2.4 mm [IQR: 2.0, 2.8] vs. 1.3 mm [IQR: 1.1, 1.7], p < 0.001). Mean width of the cricoid removed was 1.6 mm (SD 0.4 mm). Mean (SD) pre- and postoperative pVHI scores were 55.5 (19.9) and 34.6 (16.0; p < 0.001). Mean (SD) pre- and postoperative CAPE-V scores were 52.7 (15.4) and 36.5 (20.4; p < 0.001), respectively.
Conclusions:
Children in this cohort tolerated an average 1.3 mm posterior glottic gap without dysphonia. Dysphonic patients with PGD had a median 2.4 mm gap and underwent cricoid reduction by 1.6 mm. All ePCR patients demonstrated improvement in dysphonia. Results seek to optimize the management of pediatric PGD and present a safe and effective amount of cricoid to remove during ePCR.
Level Of Evidence:
4 Laryngoscope, 134:5139-5144, 2024.


Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...