Related Experiment Video
Updated: May 10, 2026
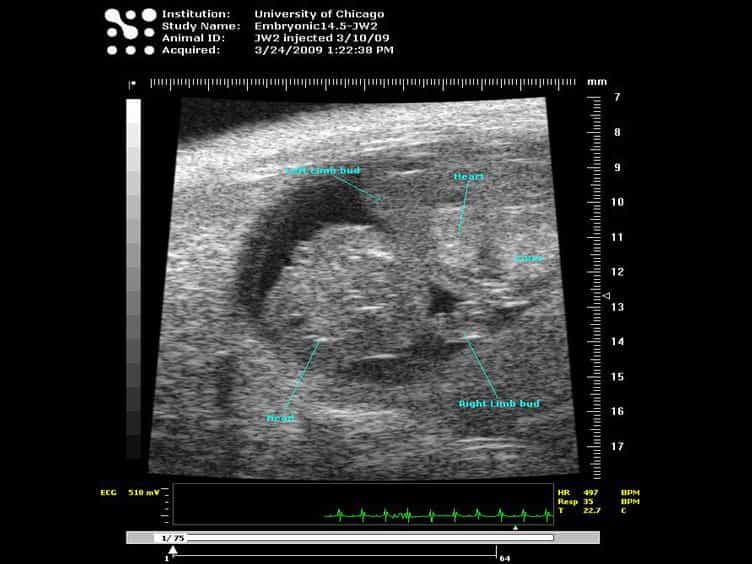

Murine Fetal Echocardiography
Published on: February 15, 2013
[Fetal death: Expert consensus from the College of French Gynecologists and Obstetricians]
Charles Garabedian1, Jeanne Sibiude2, Olivia Anselem3
1Clinique d'obstétrique, CHU de Lille, 59000 Lille, France.

Abstract:
Fetal death is defined as the spontaneous cessation of cardiac activity after fourteen weeks of amenorrhea. In France, the prevalence of fetal death after 22 weeks is between 3.2 and 4.4/1000 births. Regarding the prevention of fetal death in the general population, it is not recommended to counsel for rest and not to prescribe vitamin A, vitamin D nor micronutrient supplementation for the sole purpose of reducing the risk of fetal death (Weak recommendations; Low quality of evidence). It is not recommended to prescribe aspirin (Weak recommendation; Very low quality of evidence). It is recommended to offer vaccination against influenza in epidemic periods and against SARS-CoV-2 (Strong recommendations; Low quality of evidence). It is not recommended to systematically look for nuchal cord encirclements during prenatal screening ultrasounds (Strong Recommendation; Low Quality of Evidence) and not to perform systematic antepartum monitoring by cardiotocography (Weak Recommendation; Very Low Quality of Evidence). It is not recommended to ask women to perform an active fetal movement count to reduce the risk of fetal death (Strong Recommendation; High Quality of Evidence). Regarding evaluation in the event of fetal death, it is suggested that an external fetal examination be systematically offered (Expert opinion). It is recommended that a fetopathological and anatomopathological examination of the placenta be carried out to participate in cause identification (Strong Recommendation. Moderate quality of evidence). It is recommended that chromosomal analysis by microarray testing be performed rather than conventional karyotype, in order to be able to identify a potentially causal anomaly more frequently (Strong Recommendation, moderate quality of evidence); to this end, it is suggested that postnatal sampling of the placental fetal surface for genetic purposes be preferred (Expert Opinion). It is suggested to test for antiphospholipid antibodies and systematically perform a Kleihauer test and a test for irregular agglutinins (Expert opinion). It is suggested to offer a summary consultation, with the aim of assessing the physical and psychological status of the parents, reporting the results, discussing the cause and providing information on monitoring for a subsequent pregnancy (Expert opinion). Regarding announcement and support, it is suggested to announce fetal death without ambiguity, using simple words and adapting to each situation, and then to support couples with empathy in the various stages of their care (Expert opinion). Regarding management, it is suggested that, in the absence of a situation at risk of disseminated intravascular coagulation or maternal vitality, the patient's wishes should be taken into account when determining the time between the diagnosis of fetal death and induction of birth. Returning home is possible if it's the patient wish (Expert opinion). In all situations excluding maternal life-threatening emergencies, the preferred mode of delivery is vaginal delivery, regardless the history of cesarean section(s) history (Expert opinion). In the event of fetal death, it is recommended that mifepristone 200mg be prescribed at least 24hours before induction, to reduce the delay between induction and delivery (Low recommendation. Low quality of evidence). There are insufficient data in the literature to make a recommendation regarding the route of administration (vaginal or oral) of misoprostol, neither the type of prostaglandin to reduce induction-delivery time or maternal morbidity. It is suggested that perimedullary analgesia be introduced at the start of induction if the patient asks, regardless of gestational age. It is suggested to prescribe cabergoline immediately in the postpartum period in order to avoid lactation, whatever the gestational age, after discussing the side effects of the treatment with the patient (Expert opinion). The risk of recurrence of fetal death after unexplained fetal death does not appear to be increased in subsequent pregnancies, and data from the literature are insufficient to make a recommendation on the prescription of aspirin. In the event of a history of fetal death due to vascular issues, low-dose aspirin is recommended to reduce perinatal morbidity, and should not be combined with heparin therapy (Low recommendation, very low quality of evidence). It is suggested not to recommend an optimal delay before initiating another pregnancy just because of the history of fetal death. It is suggested that the woman and co-parent be informed of the possibility of psychological support. Fetal heart rate monitoring is not indicated solely because of a history of fetal death. It is suggested that delivery not be systematically induced. However, induction can be considered depending on the context and parental request. The gestational age will be discussed, taking into account the benefits and risks, especially before 39 weeks. If a cause of fetal death is identified, management will be adapted on a case-by-case basis (expert opinion). In the event of fetal death occurring in a twin pregnancy, it is suggested that the surviving twin be evaluated as soon as the diagnosis of fetal death is made. In the case of dichorionic pregnancy, it is suggested to offer ultrasound monitoring on a monthly basis. It is suggested not to deliver prematurely following fetal death of a twin. If fetal death occurs in a monochorionic twin pregnancy, it is suggested to contact the referral competence center, in order to urgently look for signs of acute fetal anemia on ultrasound in the surviving twin, and to carry out weekly ultrasound monitoring for the first month. It is suggested not to induce birth immediately.
More Related Videos
 07:34
Fetal Mouse Cardiovascular Imaging Using a High-frequency Ultrasound 30/45MHZ System
Published on: May 5, 2018
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Related Concept Videos
 01:38
Fertilization
 01:30
Overview of Cell Death
Cell death was observed in the early 19th century, but there was no experimental evidence to prove it. In 1842, Carl Vogt first discovered cell death in a metamorphic toad; however, it was not termed ‘cell death.’ Scientists discovered different cell death pathways only in the 20th century...
 01:07
Teratogenicity
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...