Endoscopic assessment of failed fundoplications differs between endoscopists
Related Experiment Video
Updated: Jun 15, 2025

Author Spotlight: Recent Advancements in Reoperative Foregut Surgery
Published on: September 22, 2023
Andrés R Latorre-Rodríguez1,2, Peter Kim3, Sumeet K Mittal4,5
1Norton Thoracic Institute, St. Joseph's Hospital and Medical Center, 500 W Thomas Road, Phoenix, AZ, 85013, USA.

Background:
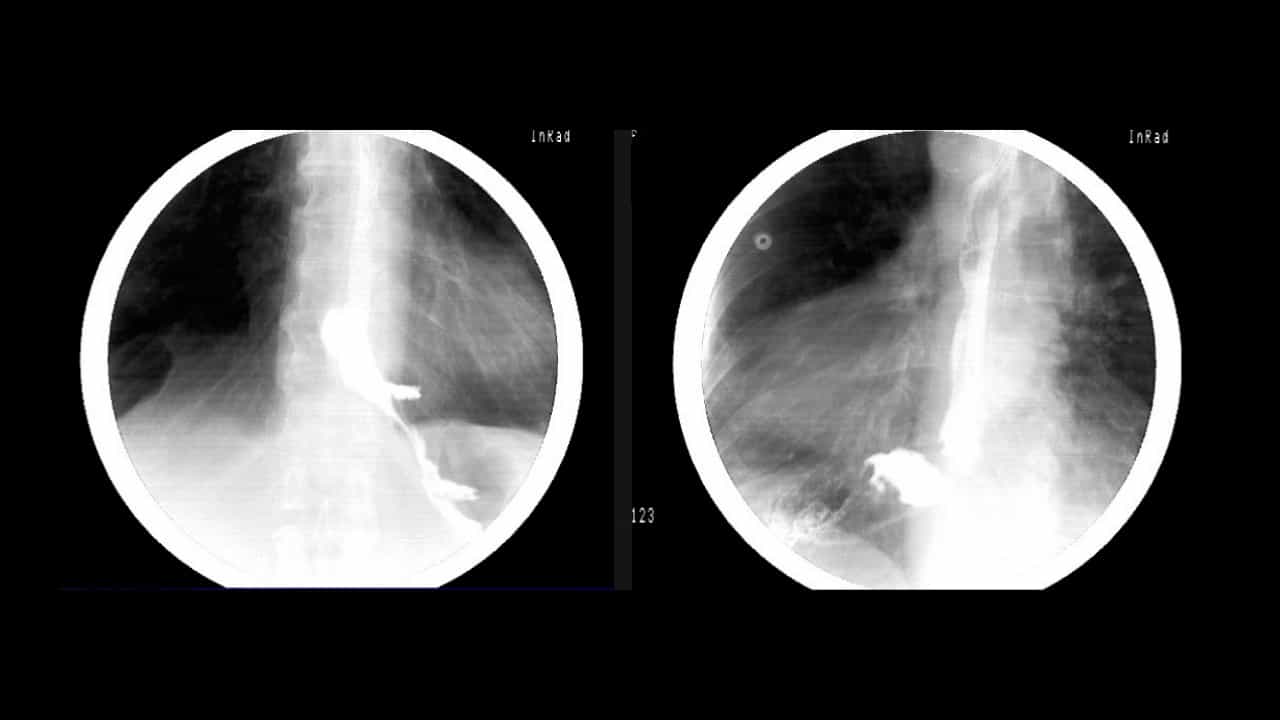
Despite excellent long-term outcomes, a small proportion of patients who undergo fundoplication with hiatal hernia repair (laparoscopic antireflux surgery [ARS]) for treatment of gastroesophageal reflux disease (GERD) may require reoperation. Esophagogastroduodenoscopy (EGD) assessment in patients presenting with symptom recurrence plays a critical role in surgical planning of redo-ARS by confirming failure of the fundoplication and revealing the pattern of failure. We aimed to compare the findings documented by external endoscopists (i.e., outside physicians) to those documented by internal endoscopists (i.e., operating foregut or thoracic surgeons) before redo-ARS.
Methods:
After IRB approval, we conducted a retrospective chart review of patients who underwent redo-ARS at a tertiary surgical center between November 2016 and March 2023. Patients with both external and internal EGD reports were included, and findings from the two reports were compared.
Results:
Of 197 patients who underwent redo-ARS, both preoperative EGD reports were available for 181 (136 [75.1%] women; median age, 61 years [IQR 53-69]; median BMI, 27.9 kg/m2 [IQR 24.9-31.3]). The median time between primary and redo-ARS was 89 months (IQR 38-153), and the median time between external and internal endoscopic evaluation was 5 months (IQR 2-12). Only 38.9% of external reports mentioned a prior fundoplication. Compared to the operating surgeons, external physicians reported a significantly lower proportion of Barrett's esophagus (52.4%, p < .001), slipped fundoplications (28.8%, p < .001), paraesophageal hernias (20.5%, p < .001), disrupted fundoplications (20%, p < .001), intrathoracic fundoplications (0%, p < .001), and twisted fundoplications (0%, p < .001).
Conclusions:
External endoscopists' reports of failed fundoplications are often incomplete and lack relevant details. Discrepancies between nonsurgical endoscopists and experienced surgeons are likely explained by a lack of training and experience to discern and document fundoplication changes accurately. To reduce this gap, we strongly recommend the adoption of standard definitions describing post-fundoplication endoscopic changes and the inclusion of relevant training within educational programs.
Related Concept Videos
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:28
Endoscopic Procedures III: Video Capsule Endoscopy
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:25
Endoscopic Procedures II: Colonoscopy