Related Experiment Video
Updated: Jun 15, 2025


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Primary unilateral macronodular adrenal hyperplasia with concomitant glucocorticoid and androgen excess and KDM1A
Yasir S Elhassan1,2, Silke Appenzeller3, Laura-Sophie Landwehr4
1Institute of Metabolism and Systems Research, University of Birmingham, Birmingham, United Kingdom.

Background:
Primary bilateral macronodular adrenal hyperplasia (PBMAH) is a rare cause of Cushing's syndrome. Individuals with PBMAH and glucose-dependent insulinotropic polypeptide (GIP)-dependent Cushing's syndrome due to ectopic expression of the GIP receptor (GIPR) typically harbor inactivating KDM1A sequence variants. Primary unilateral macronodular adrenal hyperplasia (PUMAH) with concomitant glucocorticoid and androgen excess has never been encountered or studied.
Methods:
We investigated a woman with a large, heterogeneous adrenal mass and severe adrenocorticotropic hormone-independent glucocorticoid and androgen excess, a biochemical presentation typically suggestive of adrenocortical carcinoma. The patient presented during pregnancy (22nd week of gestation) and reported an 18-month history of oligomenorrhea, hirsutism, and weight gain. We undertook an exploratory study with detailed histopathological and genetic analysis of the resected adrenal mass and leukocyte DNA collected from the patient and her parents.
Results:
Histopathology revealed benign macronodular adrenal hyperplasia. Imaging showed a persistently normal contralateral adrenal gland. Whole-exome sequencing of 4 representative nodules detected KDM1A germline variants, benign NM_001009999.3:c.136G > A:p.G46S, and likely pathogenic NM_001009999.3:exon6:c.865_866del:p.R289Dfs*7. Copy number variation analysis demonstrated an additional somatic loss of the KDM1A wild-type allele on chromosome 1p36.12 in all nodules. RNA sequencing of a representative nodule showed low/absent KDM1A expression and increased GIPR expression compared with 52 unilateral sporadic adenomas and 4 normal adrenal glands. Luteinizing hormone/chorionic gonadotropin receptor expression was normal. Sanger sequencing confirmed heterozygous KDM1A variants in both parents (father: p.R289Dfs*7 and mother: p.G46S) who showed no clinical features suggestive of glucocorticoid or androgen excess.
Conclusions:
We investigated the first PUMAH associated with severe Cushing's syndrome and concomitant androgen excess, suggesting pathogenic mechanisms involving KDM1A.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 02:23
Abnormal Proliferation
 01:31
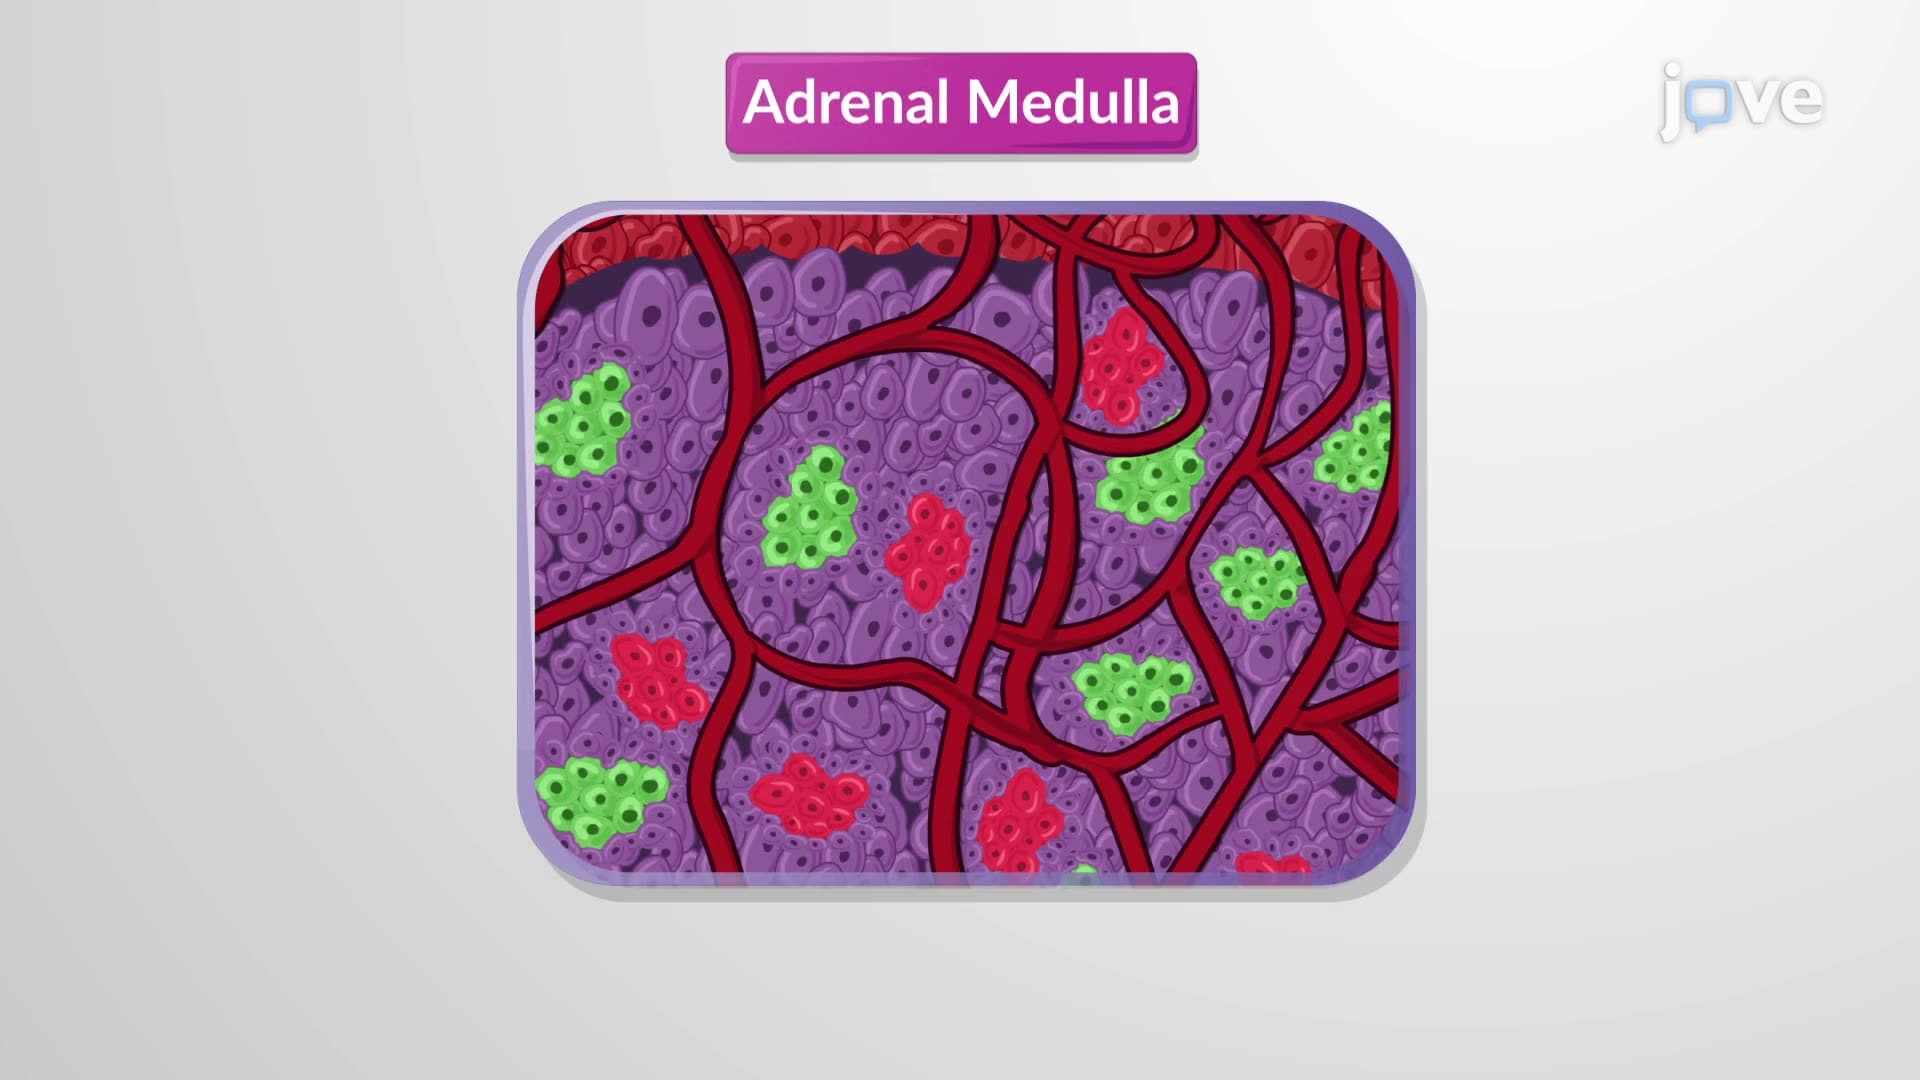
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...
 01:21
Smooth Endoplasmic Reticulum
The ER provides optimal conditions for synthesizing steroid hormones and lipids, such as phospholipids and triglycerides. Traditionally, lipid metabolism was considered to be a smooth ER function. However, there is no direct evidence to prove that rough ER is completely excluded from lipid...
 03:03
mTOR Signaling and Cancer Progression
The mTOR pathway or the...
 01:17
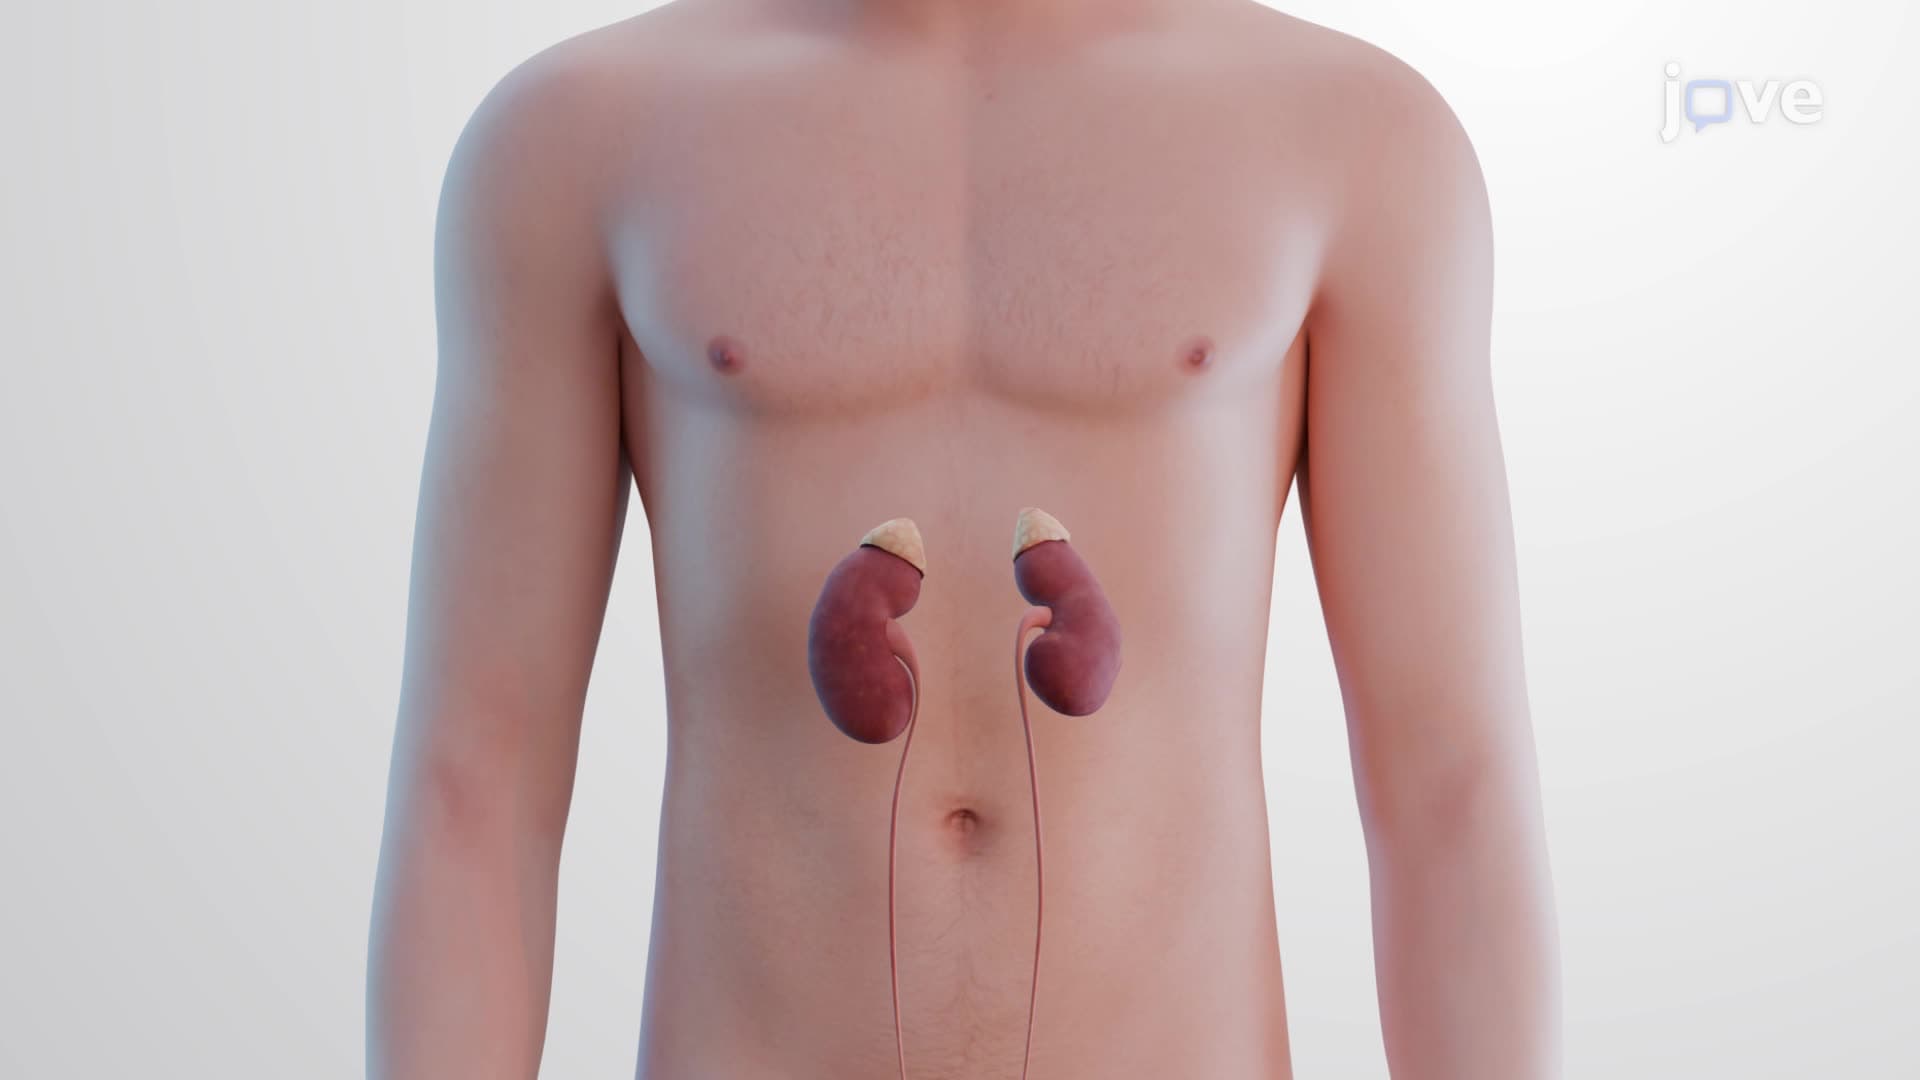
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct...