Related Experiment Video
Updated: May 10, 2026

Adapted Resistance Training Improves Strength in Eight Weeks in Individuals with Multiple Sclerosis
Published on: January 29, 2016
[Modified gluteus maximus transfer for hip abductor deficiency]
Alexander Zimmerer1,2, Lars Nonnemacher3, Maximilian Fischer3
1Klinik und Poliklinik für Orthopädie und Orthopädische Chirurgie, Universitätsmedizin Greifswald, Ferdinand-Sauerbruch-Str., 17475, Greifswald, Deutschland. alexander.zimmerer@gmail.com.

Objective:
Transfer of the gluteus maximus with refixation at the greater trochanter for treatment of abductor deficiency.
Indications:
Symptomatic abductor deficiency with atrophy and fatty degeneration of the gluteal muscles > 50% (grade 3 by quartile) with good strength of the gluteus maximus.
Contraindications:
Low atrophy or fatty degeneration of less than 50% of the gluteal muscles, limited strength of the gluteus maximus, infection.
Surgical Technique:
First, the fascia lata is incised dorsally to the tensor fascia latae muscle, with the incision extending approximately 1.5 cm proximal to the iliac crest. A second incision divides the gluteus maximus muscle longitudinally along the muscle fibers and continues towards the fascia lata distal to the greater trochanter. These incisions result in a triangular muscle flap, which is elevated and divided into anterior and posterior portions. The posterior flap is positioned ventrally over the femoral neck and fixed to the anterior capsule and the anterior edge of the greater trochanter. The anterior flap is placed directly on the proximal femur. For this purpose, a groove is prepared in the area of the proximal femur using a spherical burr to freshen up the future footprint. The anterior flap is positioned from the tip of the greater trochanter towards the insertion of the vastus lateralis muscle. Subsequently, the anterior flap is fixed to the created groove with transosseous sutures and positioned under the elevated vastus lateralis muscle in 15° abduction of the leg. To provide additional stabilization to the tendinous part of the anterior flap, a screw is inserted distally to the greater trochanter. The vastus lateralis muscle is attached to the distal tip of the anterior flap, and the remaining gluteus maximus muscle is sutured to the fascia lata to cover the anterior flap. Additionally, a flap of the tensor fascia latae muscle can be mobilized and adapted to the reconstruction. Layered wound closure is performed.
Results:
The technique of a gluteus maximus transfer represents a method for the treatment of chronic abductor deficiencies and improves abduction function as well as the gait pattern in short-term follow-ups. Fifteen patients (mean age at time of surgery 62 years) had after a mean follow-up of 2.5 years. The modified Harris Hip Score (mHHS) improved from 48 points preoperatively to 60 points at follow-up. Preoperatively, 100% had a positive Trendelenburg sign; at follow-up, this was about 50%.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 08:40
Author Spotlight: A Novel 3D-Printed Titanium Implant for Minimally Invasive Treatment of Hip Dysplasia in Young Dogs
Published on: April 19, 2024
Related Concept Videos
 01:20
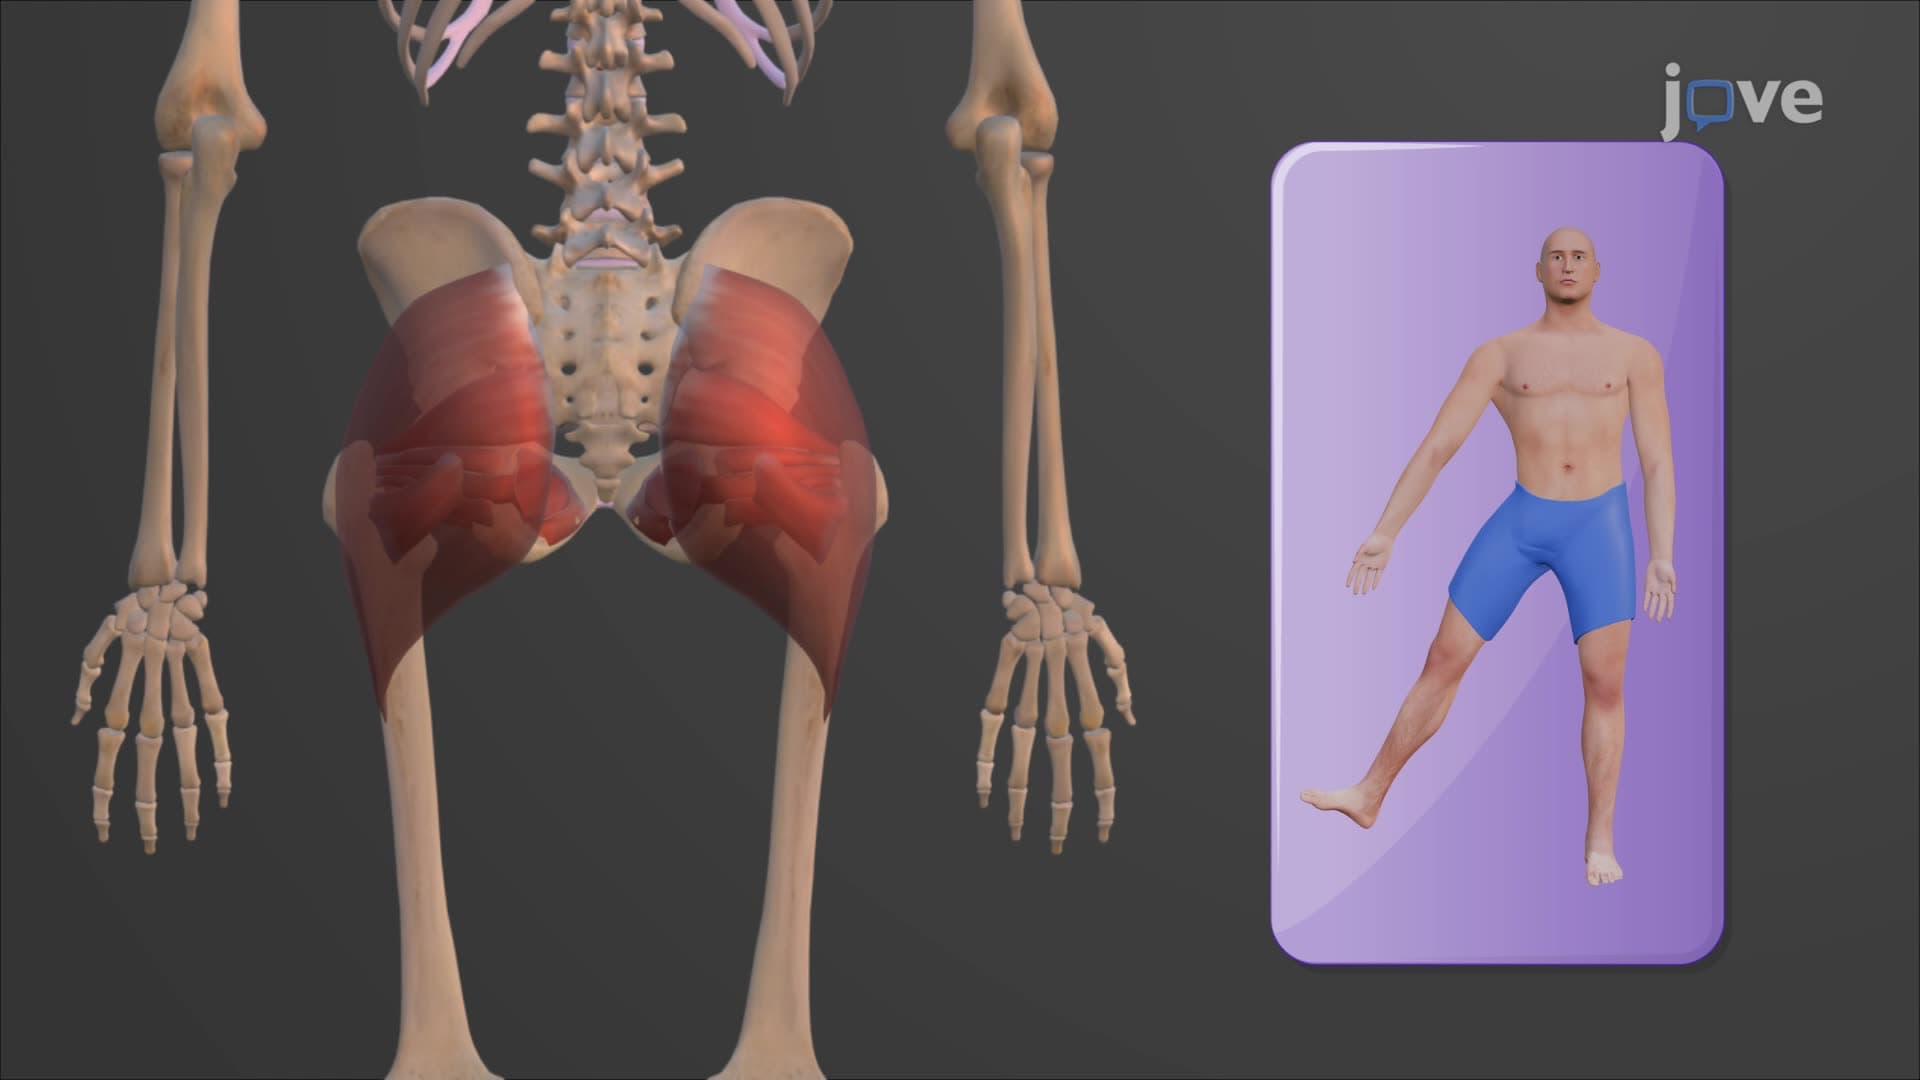
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar fascia...
 01:23
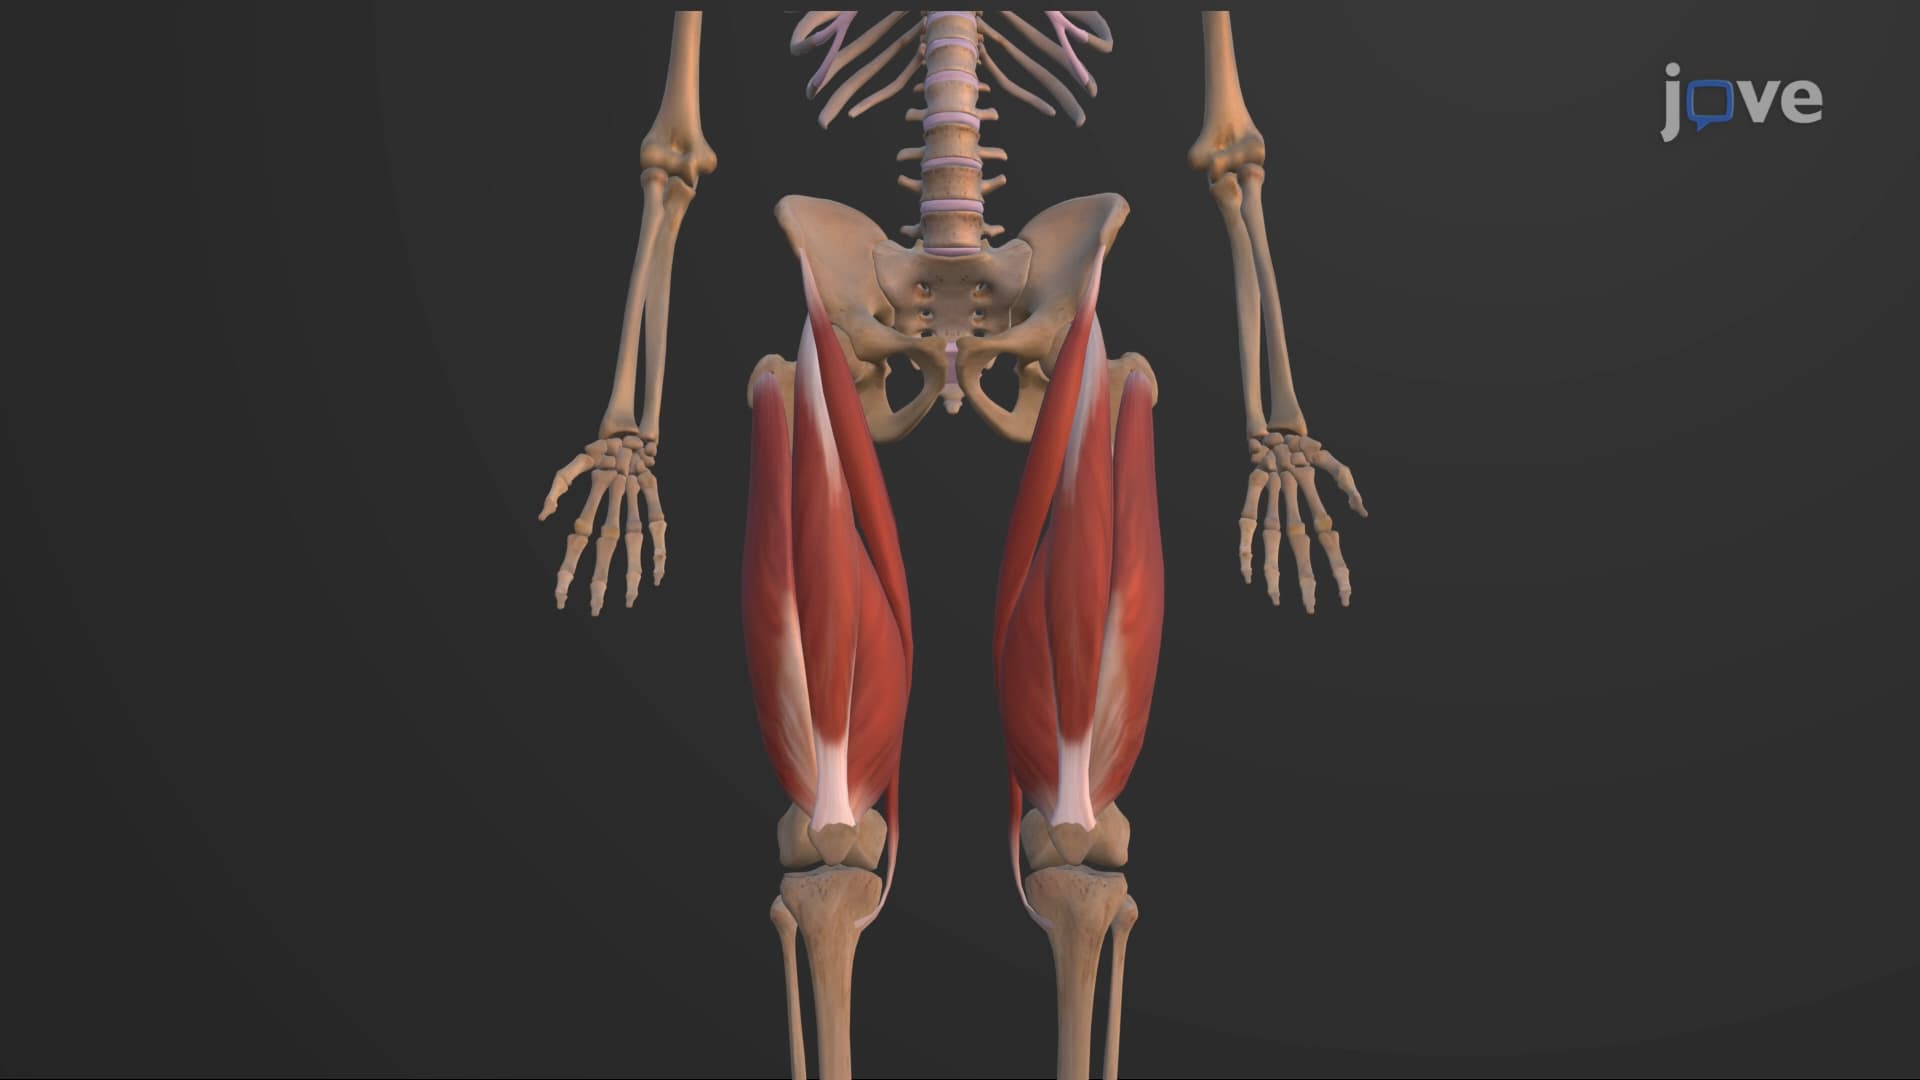
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...