Related Experiment Video
Updated: Jun 15, 2025


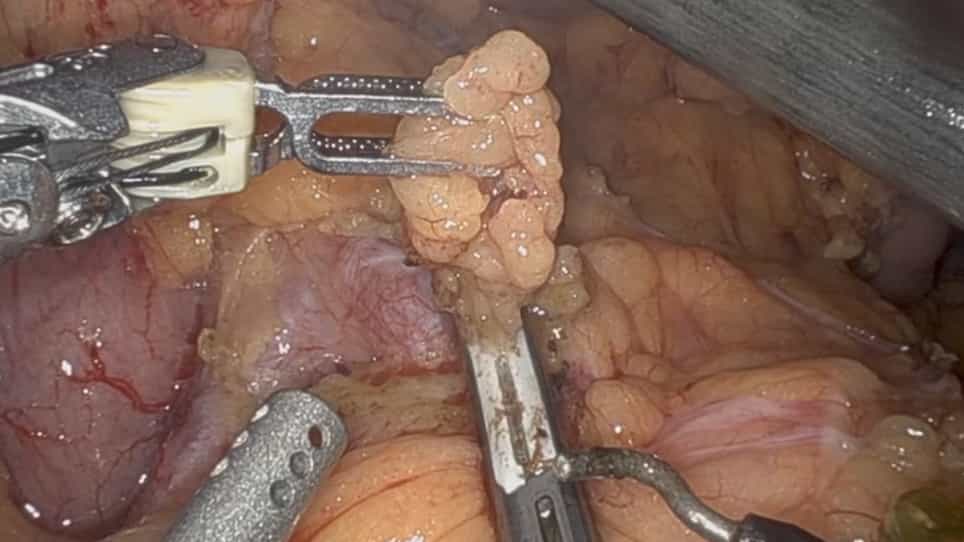
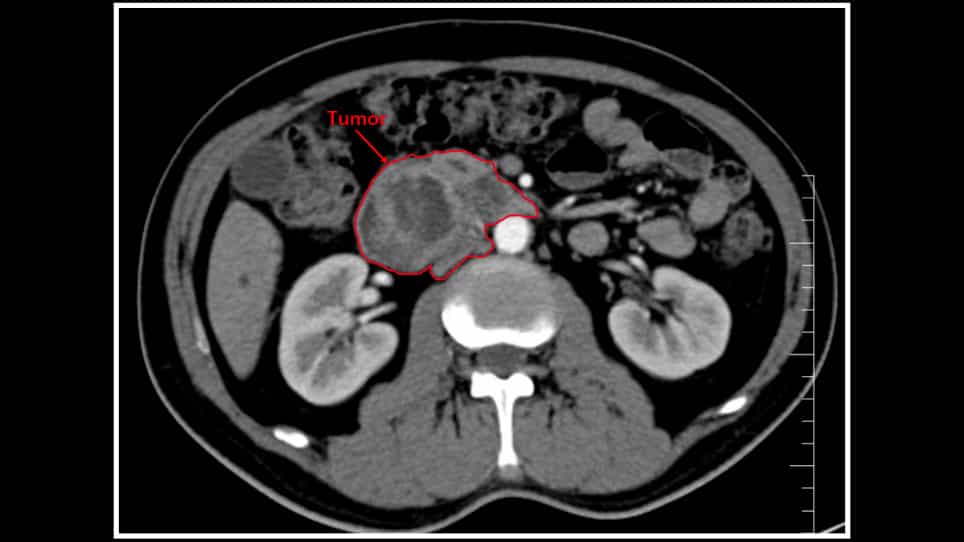
Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
Clinical Practice Guideline: Recommendations for the Perioperative Management of Pancreatic and Colorectal Cancer
Tim O Vilz1, Stefan Post, Thomas Langer
1Department of Surgery, University Hospital Bonn; Surgical Clinic, University Hospital Mannheim; German Guideline Program in Oncology/German Cancer Society, Berlin; Institute for Medical Knowledge Management, Association of the Scientific Medical Societies in Germany, Berlin, Philipps University Marburg, Marburg, Germany.

Background:
Colorectal and pancreatic carcinoma are the most common cancers of the gastrointestinal tract. Their surgical treatment carries a high morbidity: complications arise in 25% to 30% of cases, often prolonging recovery times and delaying the initiation of adjuvant therapy, leading, in turn, to worse oncological outcomes. The goal of multimodal perioperative management (mPOM) is to lower the postoperative complication rate through a combination of perioperative measures.
Methods:
This guideline on the perioperative management of gastrointestinal tumors (POMGAT) meets all requirements for an S3 guideline as specified by the Association of the Scientific Medical Societies in Germany (Arbeitsgemeinschaft der Wissenschaftlichen Medizinischen Fachgesellschaften, AWMF). These include a systematic literature search, quality assessment of the included publications, an evaluation of the reliability of the evidence according to the GRADE approach, and a structured consensus process.
Results:
Meta-analyses have shown that mPOM lowers the complication rates of both pancreatic and colorectal resections (RD 0.96 with 95% confidence interval [0.92; 0.99] and RR 0.66 [0.54; 0.80], respectively). This shortens the hospital stay after pancreatic resections by a median of 2.33 days [-2.98; -1.69] and after colorectal resections by a median of 2.59 days [-3.22; -1.97].
Conclusion:
Adherence to the POMGAT-S3 guideline for pancreatic and colorectal cancer surgery is associated with improved recovery, which can lead to a faster return to intended oncological treatment (RIOT) and thus to better long-term outcomes. These recommendations are not restricted to gastrointestinal cancer surgery; they can also be applied to visceral surgery for benign conditions, as well as to gynecological and urological operations.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...