

Cardiac sarcoidosis in patients with recurrent ventricular arrhythmias refractory to endocardial ablation
Karin Nentwich1, Karin Klingel2, Elena Ene3
1Department of Cardiology and Invasive Electrophysiology, Campus Bad Neustadt, Salzburger Leite 1, 97616, Bad Neustadt, Germany. Karin.nentwich@campus-nes.de.

Introduction:
The clinical presentation of cardiac sarcoidosis is diverse. Detection of granuloma in histopathological evaluation proves the diagnosis, but endomyocardial biopsy (EMB) is associated with a high sampling error. However, prompt immunosuppressive therapy may significantly affect patient's prognosis. By analyzing our single center cohort of patients with recurrent ventricular arrhythmias (VA) and nonischemic cardiomyopathy after failure of endocardial ablation, we looked for additional markers supporting the diagnosis of cardiac sarcoidosis.
Method:
In the last 4 years, 135 patients (mean age 49 y, 63% male) were hospitalized for epicardial ventricular arrhythmia (VA) ablation after failure of endocardial ablation. Nineteen patients had either previously received a diagnosis of cardiac sarcoidosis or were newly diagnosed. The mean follow-up time was 4.3 years. The ECG criteria, primary manifestation, histological findings in EMB, history of VT ablation, distribution of scars on MRI, electroanatomical mapping (EAM), PET CT findings, presence of atrial tachycardias, valve disease and comorbidities were analyzed.
Results:
Six of 19 (32%) patients showed right bundle block; 6 of 19 (32%) had AV nodal disease, including 4 patients with AV-block III; and 14 patients (73%) primarily presented with ventricular arrhythmias (including 3 with cardiac arrest). In all 19 patients cardiac EMB revealed elevated CD68 macrophages and CD3 T lymphocytes, and 7 of 19 were positive for granuloma (36,8%). Six of 6 patients (100%) undergoing PET CT showed acute inflammation. By analyzing the scar distribution, the most common locations were basal anteroseptal, basal inferoseptal, mid inferoseptal, mid inferior and the septal RV/RVOT. (septal substrate in 100%). There was a high correlation between the findings on the MRIs and low voltage in the electroanatomical mapping EAM). All patients received an immunosuppressive therapy. No patient died during follow-up, 1 patient had a high urgent heart transplant after withdrawal of steroid therapy.
Conclusion:
Chronic untreated inflammation may be the underlying pathophysiology for patients with unspecific cardiomyopathy and recurrent VA refractory to endocardial and epicardial ablation. Septal substrate in the EAM/MRI, elevated CD3 lymphocytes in the EBM and inflammation in the PET CT may indicate the possible diagnosis of cardiac sarcoidosis. Initializing immunosuppressive therapy in patients with this dedicated constellation with should be taken into consideration.
More Related Videos
 12:15
Tissue Preparation Techniques for Contrast-Enhanced Micro Computed Tomography Imaging of Large Mammalian Cardiac Models with Chronic Disease
Published on: February 8, 2022
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:28
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:30
Cardiac Action Potential
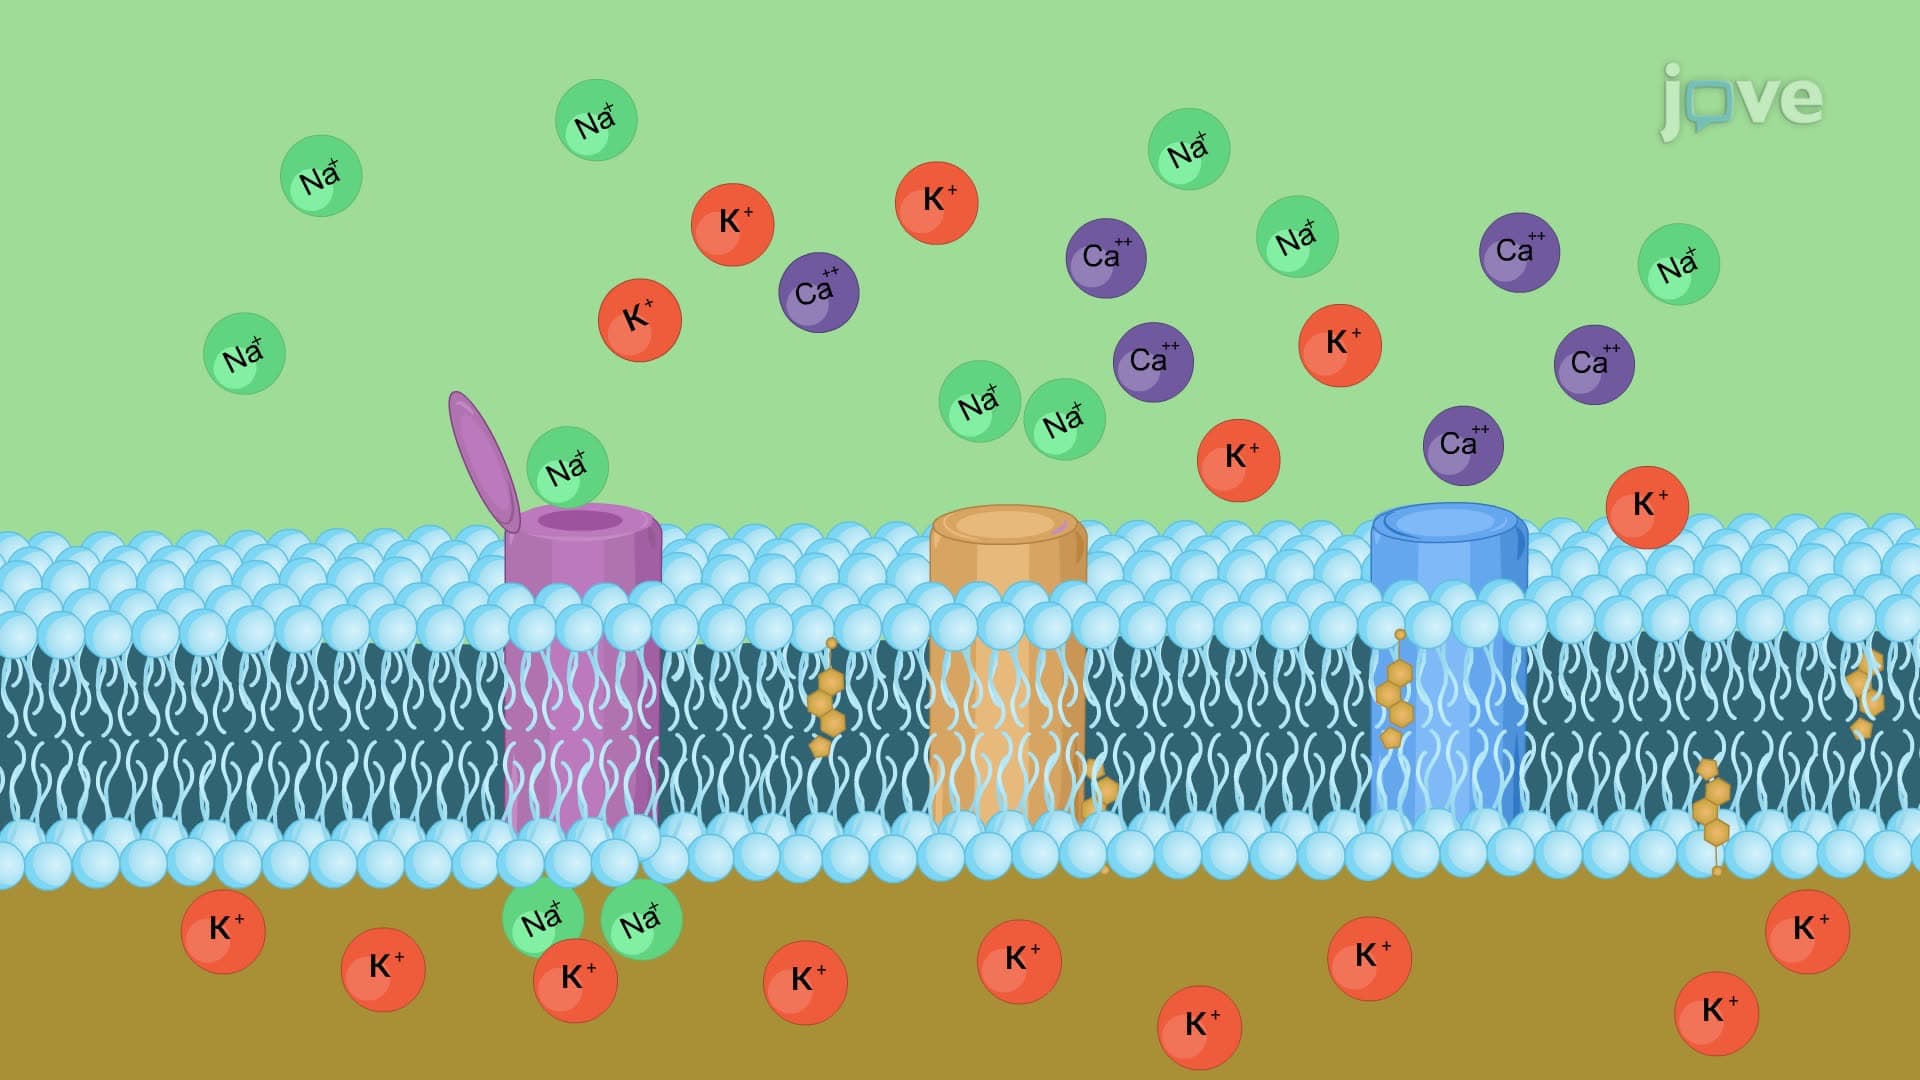
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials