Related Experiment Video
Updated: Jul 11, 2026

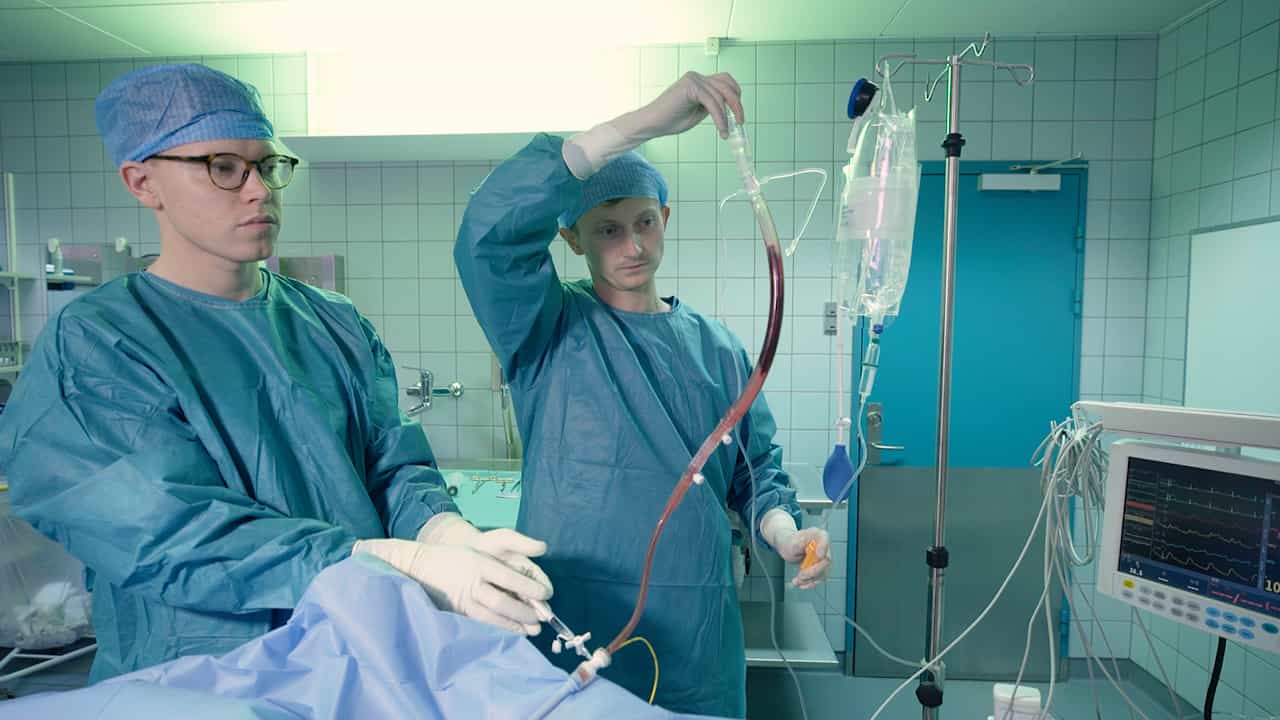
Prehospital Thrombolysis: A Manual from Berlin
Published on: November 26, 2013
Tenecteplase Catheter-Directed Thrombolytic Therapy in Submassive Pulmonary Embolism: A Case Report
Dania Ghaziri1, Hisham Bou Fakhreddine2, Fadi Sawaya2
1Department of Pharmacy American University of Beirut Medical Center, Beirut, Lebanon.

Introduction: In pulmonary embolism (PE), when used for catheter-directed thrombolysis (CDT), low-dose alteplase is associated with good outcomes. Tenecteplase has been only used as intravenous for this indication. In the context of our national economic crisis where alteplase was unavailable, we describe our experience with tenecteplase CDT. Case: A 73-year-old male, hypertensive and smoker with COPD, presented to the ED with intermediate high-risk PE.(ED) with intermediate high-risk PE. Heparin infusion was initiated. A few hours later, the patient developed atrial fibrillation (AF) for which amiodarone infusion was started. Also, a left femoral and popliteal vein thrombosis was also confirmed by the lower extremity duplex. As the patient remained dyspneic with unstable vital signs, the decision was to perform a CDT. In the absence of alteplase, tenecteplase was used at 0.5 mg/h over 30 h, for a total of 15 mg. Result: Twenty-four hours after tenecteplase initiation, dyspnea and vital signs had significantly improved. Oxygen support was gradually dropping to finally stop. Being on concomitant heparin infusion, the patient had a mild blood oozing at the femoral vein site of entry; however, this did not require any transfusion or discontinuation of heparin. The patient regained his baseline physical and mental functions and was discharged on enoxaparin and amiodarone tablet. Discussion: This is the first experience describing the use of tenecteplase as part of CDT in a patient with acute intermediate high-risk PE. The combination to therapeutic heparin infusion, already described in different clinical scenarios with intravenous tenecteplase, was safe and well tolerated Conclusion: CDT with tenecteplase was, for the first time, safely and effectively used in an intermediate high-risk PE patient. However, more studies are needed to confirm and establish these findings.
Introduction: In pulmonary embolism (PE), when used for catheter-directed thrombolysis (CDT), low-dose alteplase is associated with good outcomes. Tenecteplase has been only used as intravenous for this indication. In the context of our national economic crisis where alteplase was unavailable, we describe our experience with tenecteplase CDT. Case: A 73-year-old male, hypertensive and smoker with COPD, presented to the ED with intermediate high-risk PE.(ED) with intermediate high-risk PE. Heparin infusion was initiated. A few hours later, the patient developed atrial fibrillation (AF) for which amiodarone infusion was started. Also, a left femoral and popliteal vein thrombosis was also confirmed by the lower extremity duplex. As the patient remained dyspneic with unstable vital signs, the decision was to perform a CDT. In the absence of alteplase, tenecteplase was used at 0.5 mg/h over 30 h, for a total of 15 mg. Result: Twenty-four hours after tenecteplase initiation, dyspnea and vital signs had significantly improved. Oxygen support was gradually dropping to finally stop. Being on concomitant heparin infusion, the patient had a mild blood oozing at the femoral vein site of entry; however, this did not require any transfusion or discontinuation of heparin. The patient regained his baseline physical and mental functions and was discharged on enoxaparin and amiodarone tablet. Discussion: This is the first experience describing the use of tenecteplase as part of CDT in a patient with acute intermediate high-risk PE. The combination to therapeutic heparin infusion, already described in different clinical scenarios with intravenous tenecteplase, was safe and well tolerated Conclusion: CDT with tenecteplase was, for the first time, safely and effectively used in an intermediate high-risk PE patient. However, more studies are needed to confirm and establish these findings.

Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:19
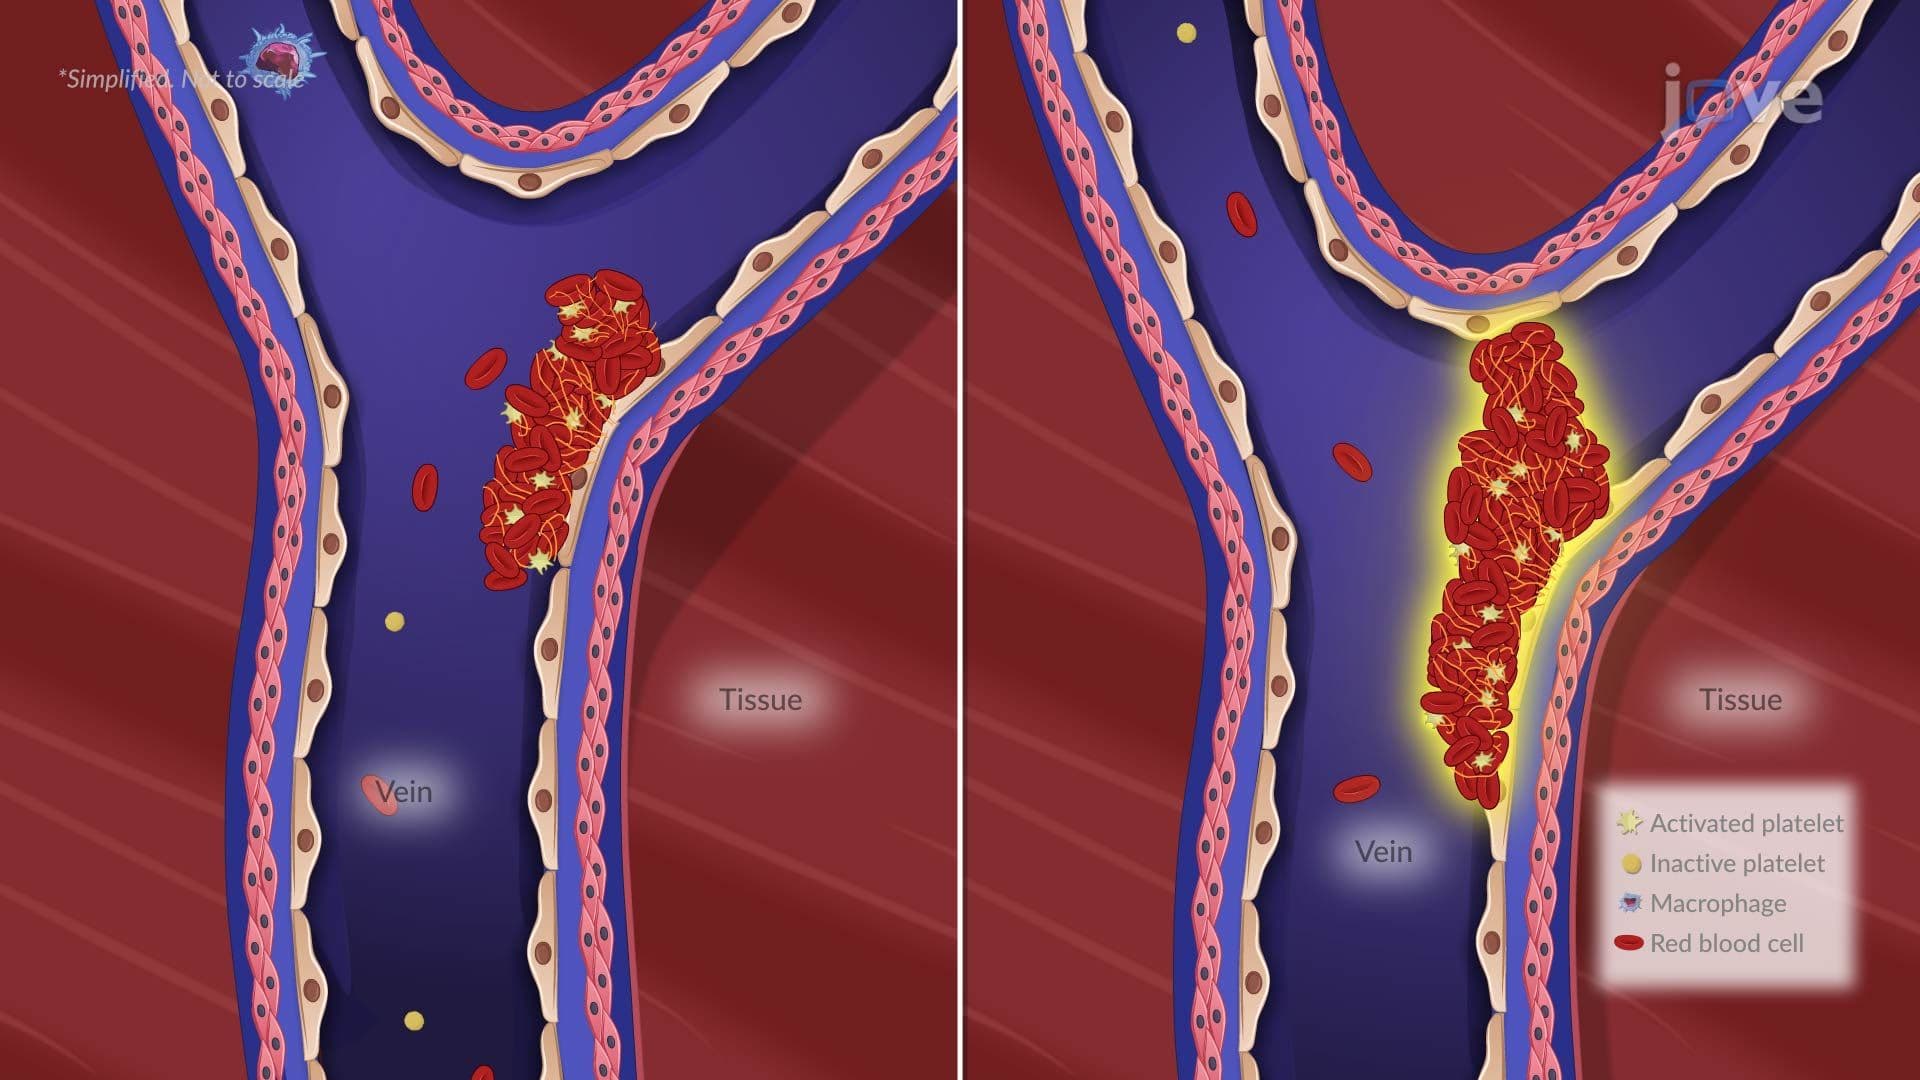
Pulmonary Embolism I: Introduction