Related Experiment Video
Updated: Aug 14, 2026
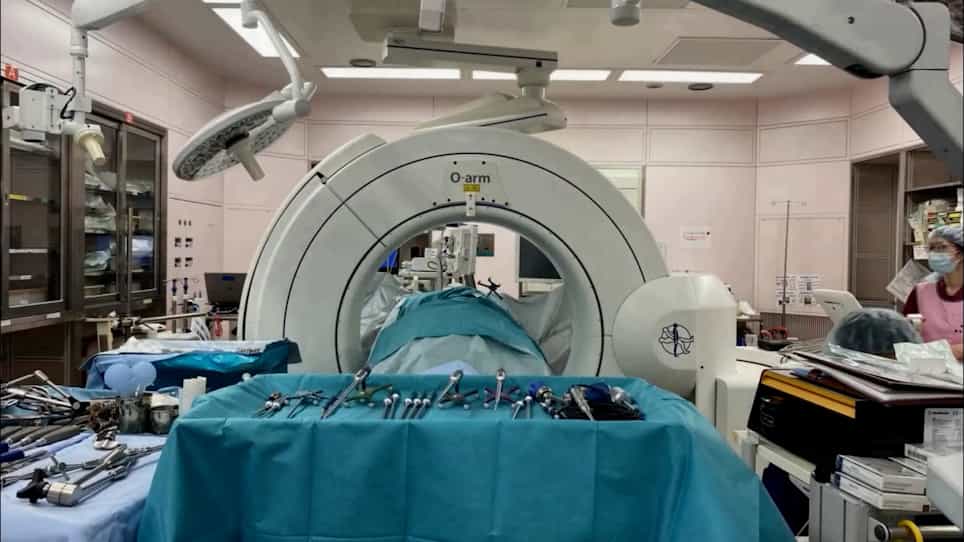
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Percutaneous lumbopelvic fixation is effective in the management of unstable transverse sacral fractures
James D Brodell1, Mark C Lawlor1, Gabrielle Santangelo2
1Department of Orthopaedics & Physical Performance, University of Rochester School of Medicine and Dentistry, Rochester, NY, USA.

Objectives:
Historically, fractures causing lumbopelvic dissociation have been managed with open lumbosacral fusion and instrumentation. Our aim was to evaluate outcomes and complications following surgical management of unstable transverse sacral fractures with percutaneous lumbopelvic fixation.
Methods:
Design: Retrospective case series.
Setting:
Academic Single Center, Level I Trauma Center. Patient Selection Criteria: Patients with lumbopelvic dissociation undergoing surgery. Outcome Measures and Comparisons: Patient demographics, mechanism of injury, ISS, associated injuries, radiographic classification (Roy-Camille), patient-reported outcomes (PROMIS PI, PF, D, and ODI), and complications were collected.
Results:
27 patients were enrolled with an average follow-up of 18.7 ± 17.6 months and age of 54.4 ± 25.1 years. All patients underwent lumbar pedicle screw and iliac screw placement. Sacral laminectomy was performed if the patient had a preoperative neurological deficit. Patients were counseled on instrumentation removal at 6-12 months. 67 % of patients sustained a fall, and 33 % were involved in an MVA. 52 % were Roy-Camille Type 2, and 32 % and 20 % were Types 1 and 3, respectively. The mean EBL was 261 ± 400 ml. 37 % required concurrent sacral laminectomy. There were no intraoperative complications and four postoperative complications, including surgical site infection, rod dislodgment, and deep venous thrombosis. 63 % underwent removal of instrumentation after fracture healing. ODI scores significantly improved from 6 weeks post-op (35.5 ± 4.5) to one-year follow-up (18.3 ± 9.6, p = 0.005), two-year follow-up (20.3 ± 10.0, p = 0.03), and final follow-up (16.4 ± 8.8, p = 0.002). Statistically significant improvements were observed in the PROMIS PI, PF, and D domains (p < 0.05).
Conclusion:
Our study demonstrates that lumbopelvic instrumentation leads to successful management of unstable transverse sacral fractures, with improvement in PRO. The combination of percutaneous instrumentation without arthrodesis did not result in any fracture non-union.
Level Of Evidence:
Level IV.
More Related Videos

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...