Related Experiment Video
Updated: May 6, 2026
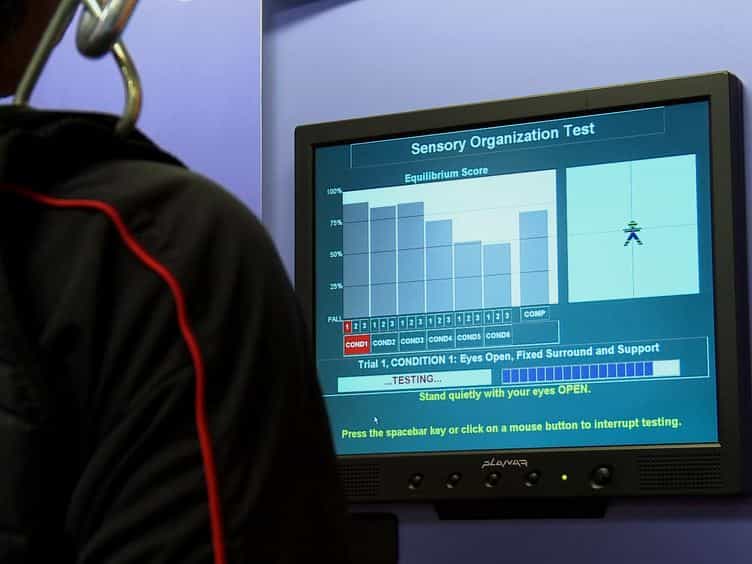

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Markers of optimal medical therapy are associated with improved limb outcomes after elective revascularization for
Marissa C Jarosinski1, Muhammed S Hafeez1, Natalie D Sridharan1
1Division of Vascular Surgery, University of Pittsburgh Medical Center, Pittsburgh, PA.

Background:
Optimal medical therapy (OMT) is a modifiable factor that decreases mortality and cardiovascular events in patients with severe peripheral arterial disease. We hypothesized that preintervention OMT would be associated with improved 1-year reintervention and major adverse limb event (MALE) rates after elective endovascular revascularization for intermittent claudication (IC).
Methods:
Using the Vascular Quality Initiative (2010-2020), we identified patients with IC undergoing elective endovascular, hybrid, and open surgical interventions. Preoperative antiplatelet, statin, and nonsmoking status defined OMT components and created three groups: complete (all components), partial (1-2 components), and no OMT. The primary outcome was 1-year reintervention. Secondary outcomes included MALE and factors associated with OMT usage. Multivariable logistic regression generated adjusted odds ratios (aOR).
Results:
There were 39,088 patients (14,907 [38.1%] complete, 22,054 [56.4%)] partial, 2127 [5.4%] no OMT) who met our criteria. Patients with any OMT were more frequently older with more cardiovascular diseases and diabetes (P < .0001). Patients without OMT were more likely to be Black or with Medicare or Medicaid (P < .05). Observed 1-year reintervention (5.3% complete OMT, 6.1% partial OMT, 8.3% no OMT; P < .001) and MALE (5.6% complete OMT, 6.3% partial OMT, 8.8% no OMT; P < .001) were decreased by partial or complete OMT compared with no OMT. Complete OMT significantly decreased the adjusted odds of reintervention and MALE by 28% (aOR, 0.72, 95% confidence interval [95% CI], 0.59-0.88) and 30% (aOR, 0.70; 95% CI, 0.58-0.85), respectively, compared with no OMT. Partial OMT decrease the adjusted odds of reintervention and MALE by 24% (aOR, 0.76; 95% CI, 0.63-0.92) and 26% (aOR, 0.74; 95% CI, 0.62-0.89), respectively.
Conclusions:
Preintervention OMT is an underused, modifiable risk factor associated with improved 1-year reintervention and MALE. Vascular surgeons are uniquely positioned to initiate and maintain OMT in patients with IC before revascularization to optimize patient outcomes.
More Related Videos


Related Concept Videos
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:26
Atherosclerosis III: Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management