Related Experiment Video
Updated: Jun 14, 2025
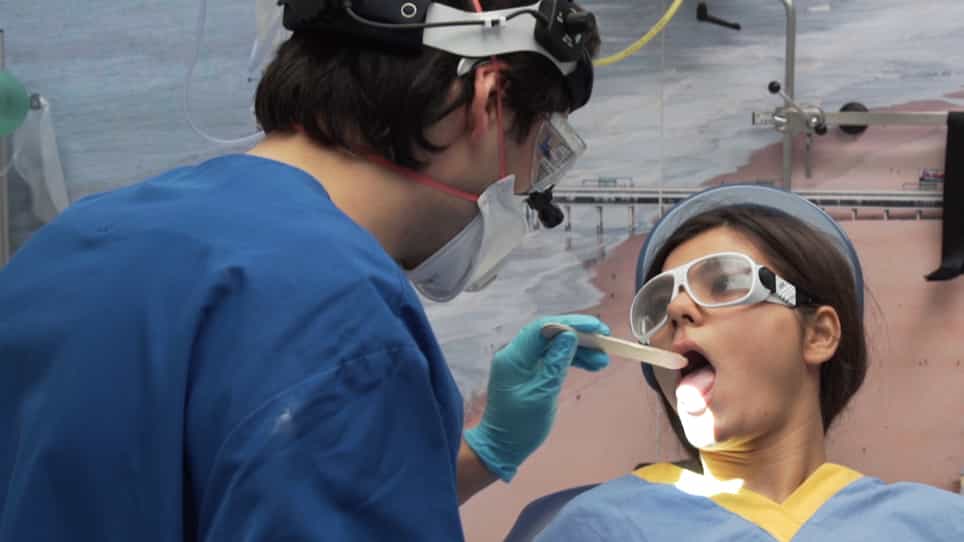

CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
Optimizing pediatric tonsillectomy outcomes with an opioid sparing anesthesia protocol: Learning and continuously
Jennifer L Chiem1,2, Amber M Franz1,2, Elizabeth E Hansen1,2
1Department of Anesthesiology and Pain Medicine, Seattle Children's Hospital, Seattle, Washington, USA.

Introduction:
This quality improvement initiative is a continued pursuit to optimize outcomes by iteratively improving our opioid sparing anesthesia protocol for tonsillectomy with or without adenoidectomy at our pediatric ambulatory surgical center through data driven Plan-Do-Study-Act cycles.
Methods:
From 1/2015 through 12/2023, our standardized tonsillectomy protocol underwent nine procedure-specific perioperative Plan-Do-Study-Act cycles, three procedure-specific postoperative prescription Plan-Do-Study-Act cycles, and four general ambulatory surgical center enhanced recovery Plan-Do-Study-Act cycles. We analyzed data from the medical record using statistical process control charts. The primary outcome measure was the percent of patients requiring intravenous opioid in the post anesthesia care unit. Secondary outcomes included maximum post anesthesia care unit pain score, the percent of patients requiring treatment for nausea and/or vomiting in the post anesthesia care unit, and the number of postoperative opioid prescription dosages. Balancing measures were average post anesthesia care unit length of stay, percent of patients with prolonged Post Anesthesia Care Unit length of stay (>120 min), and 30-day reoperation rate.
Results:
A total of 5654 tonsillectomy with or without adenoidectomy cases were performed at our ambulatory surgical center from 2015 to 2023. The incidence of intravenous opioid administered in the post anesthesia care unit initially rose with opioid free anesthesia launch, but subsequently decreased below the target of 10%. Maximum post anesthesia care unit pain scores rose from mean 3.6 to 4.5, but subsequently returned to the baseline of 3.5, while the incidence of postoperative nausea and/or vomiting improved. The average post anesthesia care unit length of stay increased by 10 min with opioid free anesthesia; however, prolonged post anesthesia care unit stay and 30-day reoperation rates were unchanged.
Conclusions:
The continued refinement of our opioid sparing anesthesia protocol has led to reduced perioperative and home opioid use, stable maximum post anesthesia care unit pain scores, and improved postoperative nausea and vomiting rates, with only a slight increase in mean post anesthesia care unit length of stay.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 05:43
Topical Airway Anesthesia for Awake-endoscopic Intubation Using the Spray-as-you-go Technique with High Oxygen Flow
Published on: January 13, 2017
Related Concept Videos
 01:26
Tonsillitis II: Management
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...