Related Experiment Video
Updated: Jun 14, 2025


Measuring Local Anaphylaxis in Mice
Published on: October 14, 2014
To the ER? Can Patients Treat Their Anaphylaxis at Home?
Marcus S Shaker1, Aikaterini Anagnostou1,2, Matthew Greenhawt3,4
1Dartmouth Hitchcock Medical Center, Section of Allergy and Clinical Immunology, Lebanon, NH, USA.

Purpose Of Review:
To discuss if all patients who use self-injectable epinephrine outside the hospital setting require immediate emergency care.
Recent Findings:
Prior to 2023, anaphylaxis management guidance universally recommended that patients who use self-injectable epinephrine outside of the hospital or clinic setting immediately activate emergency medical services and seek further care. Additional food-induced anaphylaxis management recommendations specified that all patients always carry 2 auto-injector devices and give a second dose of epinephrine if there was not immediate response within 5 min of injection. Patients presenting for emergency care after epinephrine are often observed for up to 4-6 h afterwards, even when completely asymptomatic. These management steps have lacked evidence for improving outcomes, and universal implementation of these approaches is not cost-effective as guidance for food allergic patients. Epinephrine pharmacokinetics and pharmacodynamics suggest that peak physiologic response is more likely to occur closer to 15 min than before 5 min, that few patients require a second dose of epinephrine as most stabilize within 15 min of use, that 60 min of observation after a patient stabilizes after epinephrine use may be adequate as patients infrequently have further sequelae, and that not everyone needs to carry 2 epinephrine auto-injectors on their person at all times. The most recent anaphylaxis practice parameter promotes a contextualized approach to these management questions, outlining the option for watchful waiting to gauge response to epinephrine before seeking emergency care, which has been proven as a more cost-effective management strategy. The recent updated anaphylaxis care guidelines support the evolution of anaphylaxis care, in that universal, immediate activation of emergency services is not required for using self-injectable epinephrine outside the hospital setting.


Related Concept Videos
 02:06
Allergic Reactions
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:30
Hypersensitivities
Types of Hypersensitivities
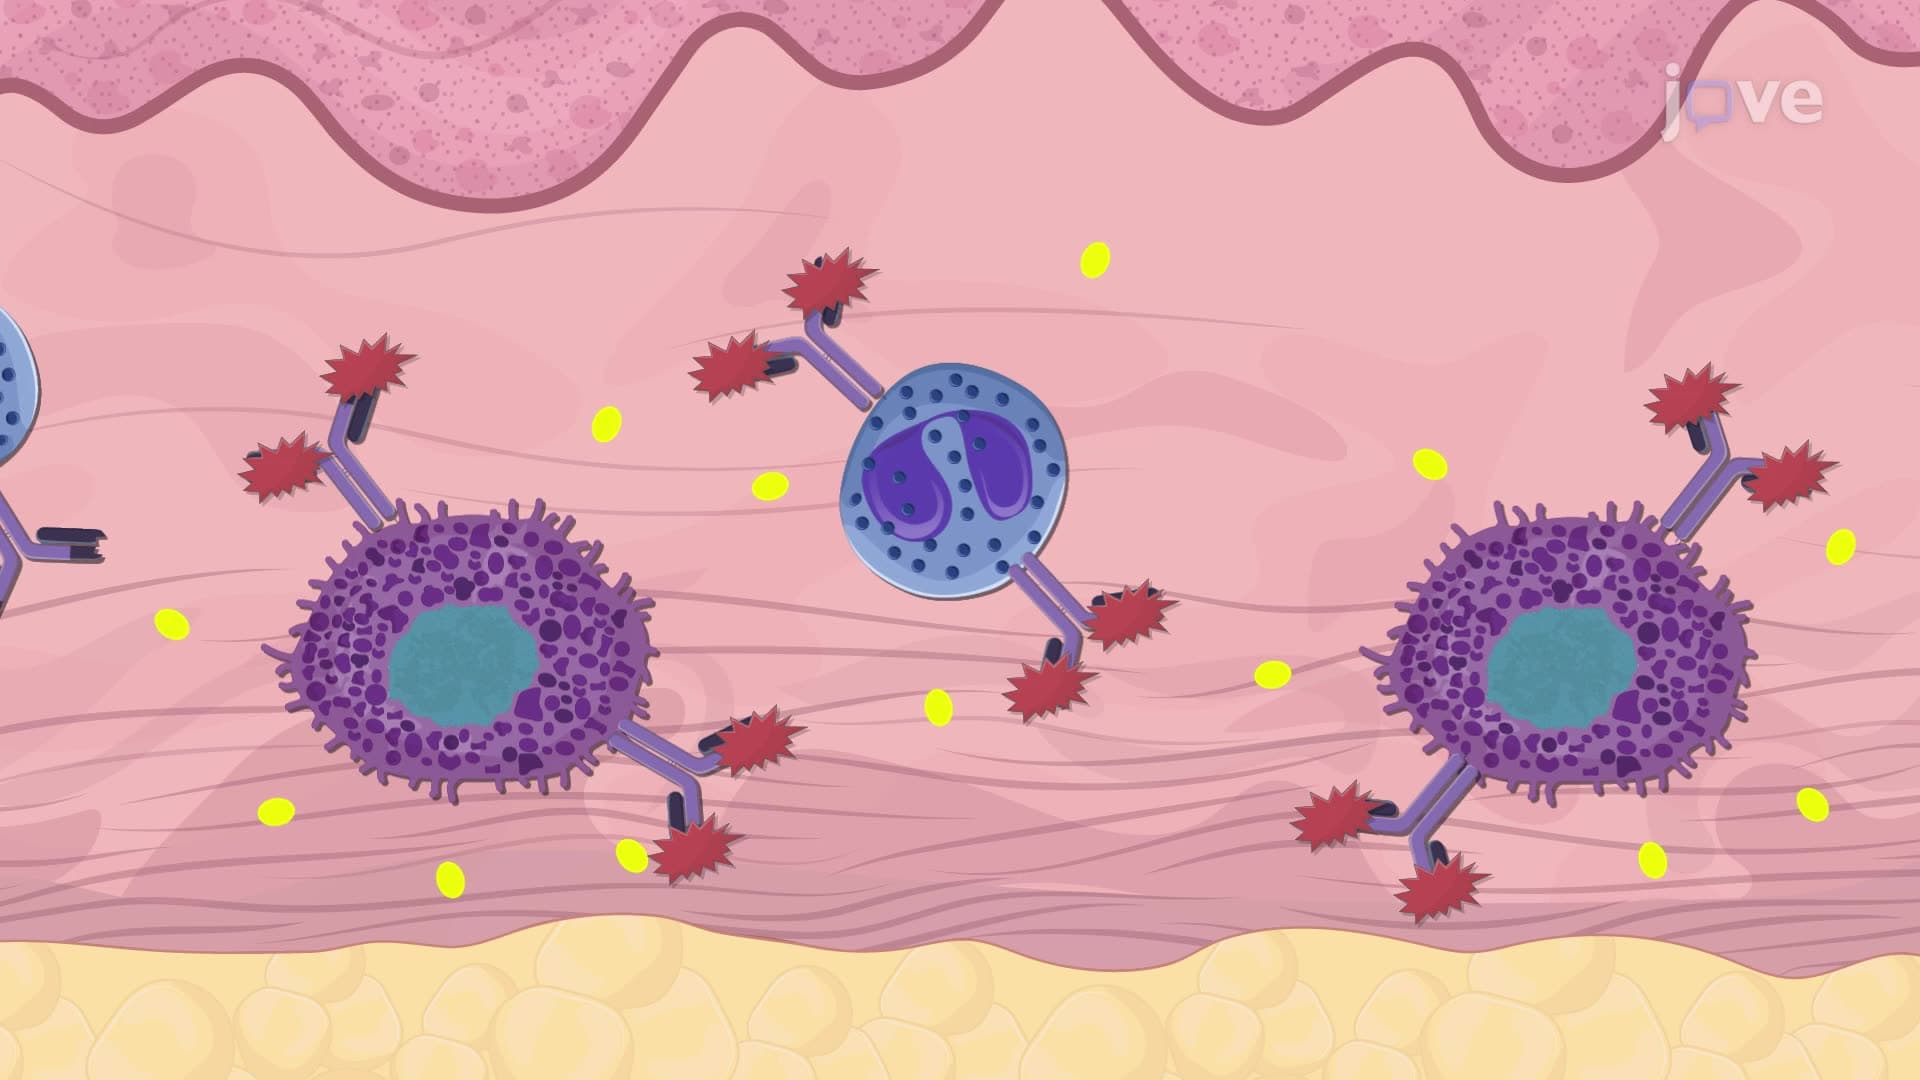
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever: