Related Experiment Video
Updated: Jun 14, 2025
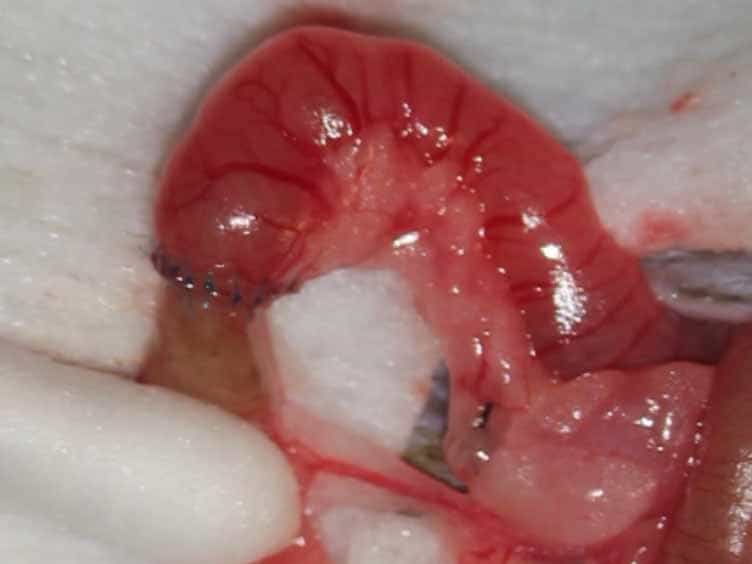

Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Association of Time Since Diagnosis of Pediatric Ileocolic Intussusception With Success of Attempted Reduction:
Livja Mertiri1, Andrew C Sher1, Marla B Sammer1
1Edward B. Singleton Department of Radiology, Texas Children's Hospital and Baylor College of Medicine, 6701 Fannin St, Ste 470, Houston, TX 77030.

Insights
Pediatric intussusception reduction can be safely performed on an urgent basis within 8 hours of diagnosis, not necessarily emergently. Key success factors include proximal location and absence of high-risk ultrasound findings, not just time to intervention.
Area of Science:
- Pediatric Radiology
- Gastroenterology
- Emergency Medicine
Background:
- Pediatric ileocolic intussusception is often treated emergently due to concerns about delayed reduction outcomes.
- Existing literature presents conflicting evidence regarding the urgency of intervention for intussusception reduction.
Purpose of the Study:
- To identify factors influencing successful image-guided reduction of pediatric ileocolic intussusception.
- To evaluate the impact of time since diagnosis on reduction success rates.
Main Methods:
- Retrospective analysis of 1065 children under 6 years undergoing image-guided enema reduction (May 2009-July 2023).
- Patients categorized as direct presenters (reduction < 8 hours post-diagnosis) or transferred from outside facilities.
- Univariable and multivariable analyses to determine factors associated with successful reduction.
Main Results:
- Successful reduction rates were high in both nontransferred (84.6%) and transferred (81.6%) patients, with no significant difference (p = .25).
- Time to reduction (within 2 hours vs. 2-8 hours) did not significantly impact success rates in nontransferred patients (p = .54).
- Proximal intussusception location (OR=3.63) and absence of high-risk ultrasound findings (OR=2.57) were independently associated with success.
Conclusions:
- Urgent, rather than emergent, reduction of pediatric intussusception (within 8 hours) appears safe and effective.
- Time since diagnosis is not a primary determinant of successful reduction; location and ultrasound findings are more critical.
- Findings inform clinical practice regarding the urgency and resource allocation for pediatric intussusception management.
Abstract:
BACKGROUND. Radiologists generally treat pediatric ileocolic intussusceptions emergently given the potential for worse outcomes resulting from delayed reduction attempts. However, the relevant literature is conflicting. OBJECTIVE. The purpose of this study was to identify factors associated with successful image-guided ileocolic intussusception reduction in children, with attention given to the time since diagnosis. METHODS. This retrospective study included patients younger than 6 years old who underwent attempted image-guided enema reduction of ileocolic intussusception between May 2009 and July 2023. Patients were separated into two groups: those who presented directly to the institution (i.e., nontransferred patients, who all underwent attempted reduction < 8 hours after ultrasound diagnosis) and those who transferred to the study institution from outside facilities. EHR data were extracted. Each patient's first image-guided reduction attempt was classified as successful or unsuccessful. Univariable and multivariable analyses were performed. RESULTS. The study included 1065 patients (649 male and 416 female patients; mean age, 18.1 months; age range, 2.2-71.0 months; 793 nontransferred and 272 transferred patients). For nontransferred patients, the mean interval between ultrasound diagnosis and the initial reduction attempt was 150.8 minutes; among transferred patients, the mean interval between advanced imaging at an outside facility (when documented) and the reduction attempt was 460.2 minutes (p < .001). Successful reduction occurred in 84.6% and 81.6% of nontransferred and transferred patients, respectively (p = .25). For nontransferred patients, success occurred in 85.6% of attempts performed less than 2 hours after diagnosis versus 84.0% of attempts performed 2 to less than 8 hours after diagnosis (p = .54); the mean interval from diagnosis to attempted reduction was 149.7 and 156.8 minutes for successful and unsuccessful attempts, respectively (p = .53). In multivariable analysis, factors showing independent associations with success were proximal intussusception location (OR = 3.63, p < .001) and absence of high-risk ultrasound findings (OR = 2.57, p < .001); success was not independently associated with age, sex, bloody stools, reduction method used, or time since diagnosis of less than 2 hours (p > .05). For transferred patients, the mean interval from advanced imaging performed at an outside facility to attempted reduction was 463.1 and 440.2 minutes for successful and unsuccessful attempts, respectively (p = .74). CONCLUSION. Intussusception reduction may not require completion emergently (within 2 hours after diagnosis) but potentially may be safely performed on an urgent basis (within 8 hours). CLINICAL IMPACT. The findings have implications for determining the standard of care, including criteria for on-call activation of radiologic resources, in the management of pediatric intussusception.
More Related Videos


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...