Related Experiment Video
Updated: Jun 14, 2025
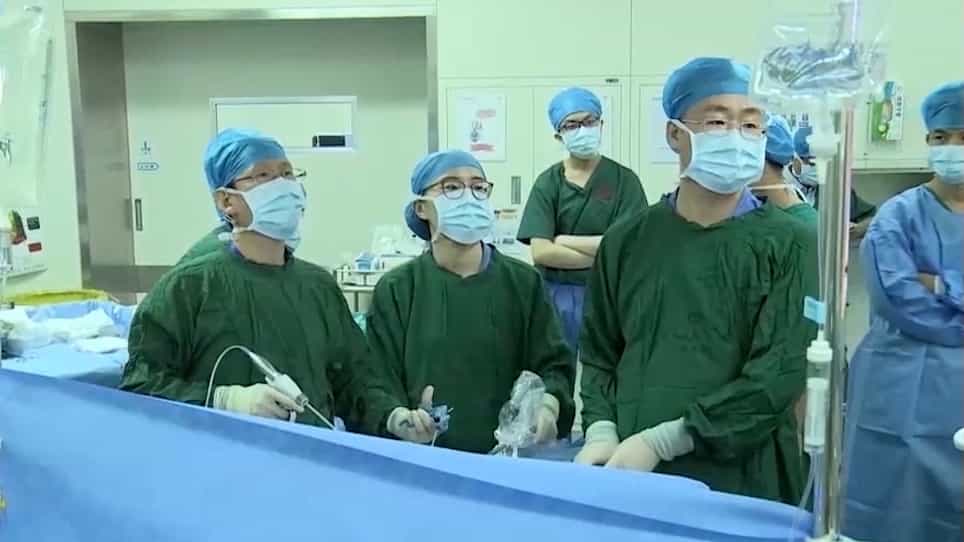
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
The spatiotemporal associations between esophageal and gastric cancers provide evidence for its joint endoscopic
Peng Li1,2, Xin Qi2, Ruhai Bai3
1Department of Thoracic Surgery, The First Affiliated Hospital of Xian Jiaotong University, Xi'an, Shaanxi, China.

Background:
The spatiotemporal epidemiological evidence supporting joint endoscopic screening for esophageal cancer (EC) and gastric cancer (GC) remains limited. This study aims to identify combined high-risk regions for EC and GC and determine optimal areas for joint and separate endoscopic screening.
Methods:
We analyzed the association of incidence trends between EC and GC in cancer registry areas across China from 2006 to 2016 using spatiotemporal statistical methods. Based on these analyses, we divided different combined risk regions for EC and GC to implement joint endoscopic screening.
Results:
From 2006 to 2016, national incidence trends for both EC and GC showed a decline, with an average annual percentage change of -3.15 (95% confidence interval [CI]: -5.33 to -0.92) for EC and -3.78 (95% CI: -4.98 to -2.56) for GC. A grey comprehensive correlation analysis revealed a strong temporal association between the incidence trends of EC and GC, with correlations of 79.00% (95% CI: 77.85 to 80.14) in males and 77.62% (95% CI: 76.50 to 78.73) in females. Geographic patterns of EC and GC varied, demonstrating both homogeneity and heterogeneity across different regions. The cancer registry areas were classified into seven distinct combined risk regions, with 33 areas identified as high-risk for both EC and GC, highlighting these regions as priorities for joint endoscopic screening.
Conclusion:
This study demonstrates a significant spatiotemporal association between EC and GC. The identified combined risk regions provide a valuable basis for optimizing joint endoscopic screening strategies for these cancers.


Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...