Related Experiment Video
Updated: Jun 14, 2025
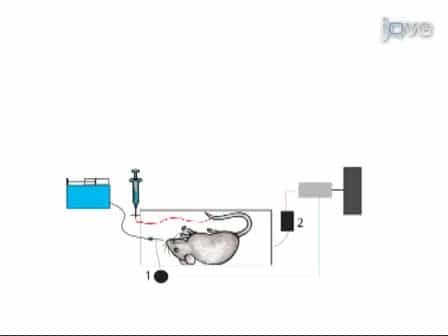
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Small airways response to bronchodilators as the marker of the uncontrolled asthma in children
Olena Rechkina1, Svitlana Opimakh1, Oksana Kravtsova1
1STATE ORGANIZATION "NATIONAL INSTITUTE OF PHTHISIOLOGY AND PULMONOLOGY NAMED AFTER F.G. YANOVSKY NATIONAL ACADEMY OF MEDICAL SCIENCES OF UKRAINE", KYIV, UKRAINE.

Insights
Maximal expiratory flow (MEF50 and MEF25) indices can identify small airway obstruction in children with uncontrolled asthma. An increase of 22% (MEF50) or 25% (MEF25) after bronchodilator use indicates uncontrolled asthma.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Asthma Research
Background:
- Asthma control in children is often assessed using standard spirometry, which may not fully capture small airway dysfunction.
- Small airways play a crucial role in asthma pathophysiology, and their obstruction can lead to poor disease control.
Purpose of the Study:
- To establish criteria for small airways response to bronchodilators using spirometry indices (MEF50 and MEF25).
- To identify these indices as markers for assessing uncontrolled asthma in pediatric populations.
Main Methods:
- The study included 92 children (aged 6-17 years) diagnosed with asthma.
- Asthma control was evaluated using the Asthma Control Test and Asthma Control Questionnaire.
- Spirometry and bronchodilator responsiveness testing were conducted for all participants.
Main Results:
- Children with uncontrolled asthma often exhibit normal FEV1 but significantly impaired small airway patency.
- Small airway obstruction is present in up to 80% of children with uncontrolled asthma.
- MEF50 and MEF25 demonstrated high sensitivity and specificity in identifying bronchial obstruction reversibility and uncontrolled asthma.
Conclusions:
- MEF50 and MEF25 indices effectively detect small airway obstruction and its reversibility, serving as indicators of uncontrolled asthma.
- MEF25 shows a higher diagnostic value compared to MEF50.
- A bronchodilator response of ≥22% for MEF50 or ≥25% for MEF25 suggests uncontrolled asthma in children.
Objective:
Aim: To develop the criteria of small airways response to bronchodilators (by spirometry indices maximal expiratory flow (MEF50 and MEF25) as the markers of uncontrolled asthma course.
Patients And Methods:
Materials and Methods: The study involved 92 participants (64 boys and 28 girls) aged 6 to 17 years (60 were less than 12 years old) with diagnosed asthma. Asthma control was assessed with the use of Asthma Control Test and Asthma Control Questionnaire. Spirometry and bronchodilator responsiveness testing were performed for all participants.
Results:
Results: Mostly, the studied children had a normal level of forced expiratory volume in the first second (FEV1), even at unsatisfactory symptoms control. The indicators of the medium and small airways patency were significantly worse in uncontrolled asthma children even in normal FEV1. Among children, the lack of asthma control can be caused by small airways obstruction in up to 80% cases. Among children who need the high dose inhaled corticosteroids treatment 93.3% have uncontrolled asthma with small airways obstruction. We found out that MEF50 and MEF25 could be the signs of the reversibility of bronchial obstruction and uncontrolled asthma with high sensitivity and specificity.
Conclusion:
Conclusions: Indices MEF50 and MEF25 allow detecting the small airways obstruction and their reversibility as a mark of uncontrolled asthma (MEF25 has a higher diagnostic value). In case of MEF50 and/or MEF25 increasing for 22% or 25% accordingly in bronchodilator test in children, the asthma should be considered uncontrolled.


Related Concept Videos
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:29
Asthma-I: Introduction