Related Experiment Video
Updated: Jun 14, 2025
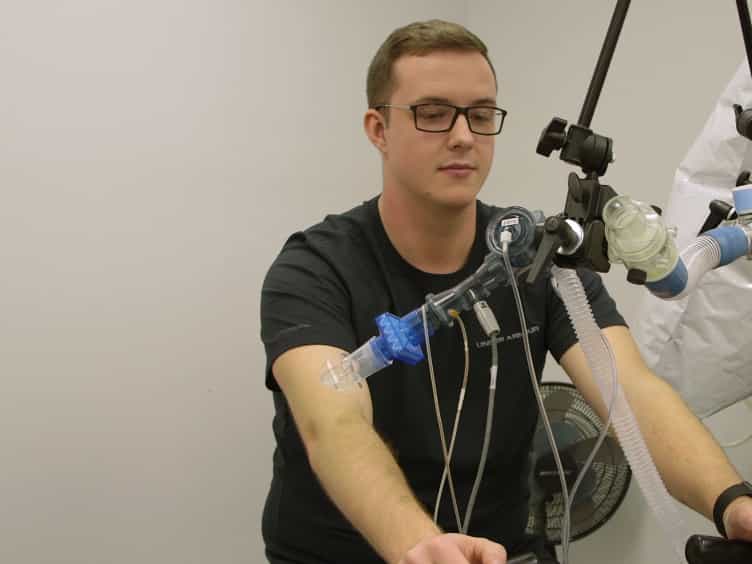

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Effect of interface dead space on the time taken to achieve changes in set FiO2 during T-piece ventilation: is face
Kolbrun Gunnarsdottir1,2, Ben J Stenson3, Elizabeth E Foglia4
1Department of Women's and Children's Health, Karolinska Institutet, Stockholm, Stockholm, Sweden kolbrun.gunnarsdottir@ki.se.

Background:
T-piece is recommended for respiratory support during neonatal stabilisation. Bench studies have shown a delay >30 s in achieving changes in fraction of inspired oxygen (FiO2) at the airway when using the T-piece. Using a face mask adds dead space (DS) to the patient airway. We hypothesised that adding face mask to T-piece systems adversely affects the time required for a change in FiO2 to reach the patient.
Methods:
Neopuff (Fisher and Paykel, Auckland, New Zealand) and rPAP (Inspiration Healthcare, Croydon, UK) were used to ventilate a test lung. DS equivalent to neonatal face masks was added between the T-piece and test lung. Additionally, rPAP was tested with nasal prongs. Time course for change in FiO2 to be achieved at the airway was measured for increase (0.3-0.6) and decrease (1.0-0.5) in FiO2. Primary outcome was time to reach FiO2+/-0.05 of the set target. One-way analysis of variance was used to compare mean time to reach the primary outcome between different DS volumes.
Results:
In all experiments, the mean time to reach the primary outcome was significantly shorter for rPAP with prongs compared with Neopuff and rPAP with face mask DS (p<0.001). The largest observed difference occurred when testing a decrease in FiO2 with 10 mL tidal volume (TV) without leakage (18.3 s for rPAP with prongs vs 153.4 s for Neopuff with face mask DS). The shortest observed time was 13.3 s when increasing FiO2 with 10 mL TV with prongs with leakage and the longest time was 172.7 s when decreasing FiO2 with 4 mL TV and added face mask DS without leak.
Conclusion:
There was a delay in achieving changes in oxygen delivery at the airway during simulated ventilation attributable to the mask volume. This delay was greatly reduced when using nasal prongs as an interface. This should be examined in clinical trials.

Related Concept Videos
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:24
External and Internal Respiration
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: