Related Experiment Video
Updated: Aug 7, 2026


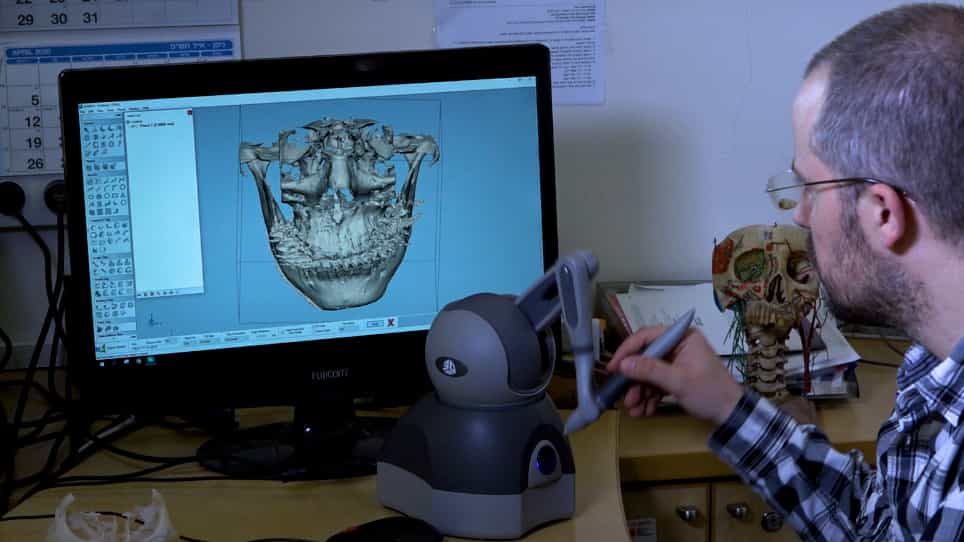
Designing CAD/CAM Surgical Guides for Maxillary Reconstruction Using an In-house Approach
Published on: August 24, 2018
Osteosynthesis for mandibular reconstruction with fibula free flap: Which type and why? A French national survey
Hugo Poncet1, Frédéric Lauwers1, Franck Delanoë1
1Plastic and Maxillofacial Surgery Department, Pierre-Paul Riquet Hospital, University Hospital Center of Toulouse, Place Du Docteur Baylac, 31059, Toulouse, France.

Abstract:
We explored the most suitable osteosynthesis type for mandibular reconstruction using fibula free flap (FFF) given the lack of robust data available. For this, an anonymous survey was e-mailed to 853 head-and-neck surgeons (France) asking about their practices and criteria guiding their osteosynthesis material and method choices. Questions assessed: (1) the most frequently used osteosynthesis type, (2) the explanatory variables related to surgeon career status/surgical specialty, and (3) justifications for osteosynthesis type (scientific, technical, "misuse"). Multivariate logistic regression was performed to test for associations of explanatory variables with plate type or misuse. Overall, 118 (13.8%) surgeons responded, among which flexible non-locking osteosynthesis was preferred (59%). Career status and surgical specialty were significantly associated with material choice. University professors/senior lecturers (OR 5.96 vs academic clinical associates; p = 0.02), but not ear-nose-throat/reconstructive plastic surgeons (OR 0.22 vs maxillofacial surgeons; p = 0.04), were more likely to opt for rigid locking osteosynthesis. Private practitioners preferred flexible non-locking osteosynthesis (OR = 5.03; p = 0.04). Only 18% of surgeons scientifically justified their choices. We considered misuse among 65% of surgeons and this was significantly associated with irregular practice of FFF surgery (OR 2.28 vs > 10 surgeries/year; p = 0.04). Overall, >50% of surgeons mainly rely on habits without scientific arguments assisting in decision-making.

Related Concept Videos
 01:40
Bone Remodeling
 01:27
Growth of Cartilage and Bone Tissue
 01:18
The Bone Matrix
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Bone Remodeling and Repair